Related Experiment Video
Updated: Feb 8, 2026
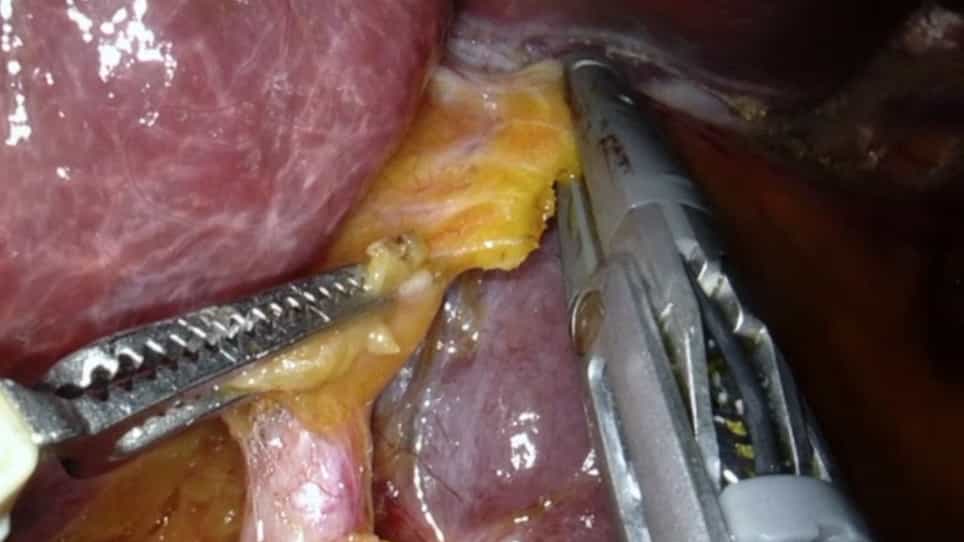
Robotic Left Hepatectomy using Indocyanine Green Fluorescence Imaging for an Intrahepatic Complex Biliary Cyst
Published on: June 24, 2022
Biliary transporter gene mutations in severe intrahepatic cholestasis of pregnancy: Diagnostic and management
Sze Pheh Yeap1, Hugh Harley1,2, Richard Thompson3
1Liver Unit, Royal Adelaide Hospital, Adelaide, South Australia, Australia.

Insights
Genetic mutations in bile acid transporters can cause severe intrahepatic cholestasis of pregnancy (ICP). Early diagnosis and tailored therapies, like naso-biliary drainage, improve outcomes for affected mothers and infants.
Area of Science:
- Hepatology and genetic medicine
- Maternal-fetal medicine
- Gastroenterology
Background:
- Bile acid (BA) transporter mutations typically manifest in childhood but can cause intrahepatic cholestasis of pregnancy (ICP) and oral contraceptive steroid (OCS)-induced cholestasis.
- Investigated five women with identified genetic transporter mutations experiencing eight pregnancies complicated by ICP.
Observation:
- ICP cases presented early (9-32 weeks gestation) and were severe (peak BA 74-370 μmol/L).
- Seven of eight pregnancies resulted in premature delivery (28-37 weeks gestation), with four cases of in utero meconium passage.
- Three women had prior histories of spontaneous or OCS-induced cholestasis.
Findings:
- Genetic analysis revealed biallelic heterozygosity for ABCB11 mutations in two cases and ABCB4 mutations in two others.
- Standard ICP treatments (ursodeoxycholic acid, rifampicin, chelation) showed limited efficacy.
- Naso-biliary drainage was effective in two persistent post-partum cholestasis cases.
Implications:
- Early-onset or recurrent ICP, particularly with a history of cholestasis, suggests underlying transporter mutations.
- Standard ICP therapies may be insufficient; BA sequestering agents or naso-biliary drainage may be beneficial.
- Optimized management strategies can lead to favorable perinatal outcomes despite preterm birth and fetal distress indicators.
Background And Aims:
Clinical syndromes associated with biallelic mutations of bile acid (BA) transporters usually present in childhood. Subtle mutations may underlie intrahepatic cholestasis of pregnancy (ICP) and oral contraceptive steroid (OCS) induced cholestasis. In five women with identified genetic mutations of such transporters, with eight observed pregnancies complicated by ICP, we examined relationships between transporter mutations, clinical phenotypes, and treatment outcomes.
Methods:
Gene mutation analysis for BA transporter deficiencies was performed using Next Generation/Sanger sequencing, with analysis for gene deletions/duplications.
Results:
Intrahepatic cholestasis of pregnancy was early-onset (9-32 weeks gestation) and severe (peak BA 74-370 μmol/L), with premature delivery (28+1 -370 weeks gestation) in 7/8 pregnancies, in utero passage of meconium in 4/8, but overall good perinatal outcomes, with no stillbirths. There was generally no response to ursodeoxycholic acid and variable responses to rifampicin and chelation therapies; naso-biliary drainage appeared effective in 2/2 episodes persisting post-partum in each of the two sisters. Episodic jaundice occurring spontaneously or provoked by non-specific infections, and OCS-induced cholestasis, had previously occurred in 3/5 women. Two cases showed biallelic heterozygosity for several ABCB11 mutations, one was homozygous for an ABCB4 mutation and a fourth case was heterozygous for another ABCB4 mutation.
Conclusions:
Early-onset or recurrent ICP, especially with previous spontaneous or OCS-induced episodes of cholestasis and/or familial cholestasis, may be attributable to transporter mutations, including biallelic mutations of one or more transporters. Response to standard therapies for ICP is often incomplete; BA sequestering therapy or naso-biliary drainage may be effective. Optimized management can produce good outcomes despite premature birth and evidence of fetal compromise.
More Related Videos


Related Concept Videos
 01:09
Mutation, Gene Flow, and Genetic Drift
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:39
Mutations
 01:35
Mutations
Chromosomal Alterations Are Large-Scale Mutations
While point mutations are changes in a single nucleotide in...