Related Experiment Video
Updated: Feb 7, 2026


A Thrombotic Stroke Model Based On Transient Cerebral Hypoxia-ischemia
Published on: August 18, 2015
Diagnosing cerebral ischemia with door-to-thrombolysis times below 20 minutes
Saana Pihlasviita1, Olli S Mattila2, Juhani Ritvonen2
1From the Research Programs Unit (S.P., O.S.M., J.R., P.J.L.), Molecular Neurology, University of Helsinki; Clinical Neurosciences, Neurology (O.S.M., G.S., S.C., D.S., T.T., P.J.L.), and Department of Emergency Medicine and Services, Section of Emergency Medical Services (H.H., M.P., M.K.), University of Helsinki and Helsinki University Hospital, Finland; Department of Clinical Neuroscience/Neurology (T.T.), Institute of Neuroscience and Physiology, Sahlgrenska Academy at University of Gothenburg; and Department of Neurology (T.T.), Sahlgrenska University Hospital, Gothenburg, Sweden. saana.pihlasviita@helsinki.fi.

Objectives:
To clarify diagnostic accuracy and consequences of misdiagnosis in the admission evaluation of stroke-code patients in a neurologic emergency department with less than 20-minute door-to-thrombolysis times.
Methods:
Accuracy of admission diagnostics was studied in an observational cohort of 1,015 stroke-code patients arriving by ambulance as candidates for recanalization therapy between May 2013 and November 2015. Immediate admission evaluation was performed by a stroke neurologist or a neurology resident with dedicated stroke training, primarily utilizing CT-based imaging.
Results:
The rate of correct admission diagnosis was 91.1% (604/663) for acute cerebral ischemia (ischemic stroke/TIA), 99.2% (117/118) for hemorrhagic stroke, and 61.5% (144/234) for stroke mimics. Of the 150 (14.8%) misdiagnosed patients, 135 (90.0%) had no acute findings on initial imaging and 100 (67.6%) presented with NIH Stroke Scale score 0 to 2. Misdiagnosis altered medical management in 70 cases, including administration of unnecessary treatments (thrombolysis n = 13, other n = 24), omission of thrombolysis (n = 5), delays to specific treatments of stroke mimics (n = 13, median 56 [31-93] hours), and delays to antiplatelet medication (n = 14, median 1 [1-2] day). Misdiagnosis extended emergency department stay (median 6.6 [4.7-10.4] vs 5.8 [3.7-9.2] hours; p = 0.001) and led to unnecessary stroke unit stay (n = 10). Detailed review revealed 8 cases (0.8%) in which misdiagnosis was possible or likely to have worsened outcomes, but no death occurred as a result of misdiagnosis.
Conclusions:
Our findings support the safety of highly optimized door-to-needle times, built on thorough training in a large-volume, centralized stroke service with long-standing experience. Augmented imaging and front-loaded specialist engagement are warranted to further improve rapid stroke diagnostics.


Related Concept Videos
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:05
Cerebral Hemispheres
 01:22
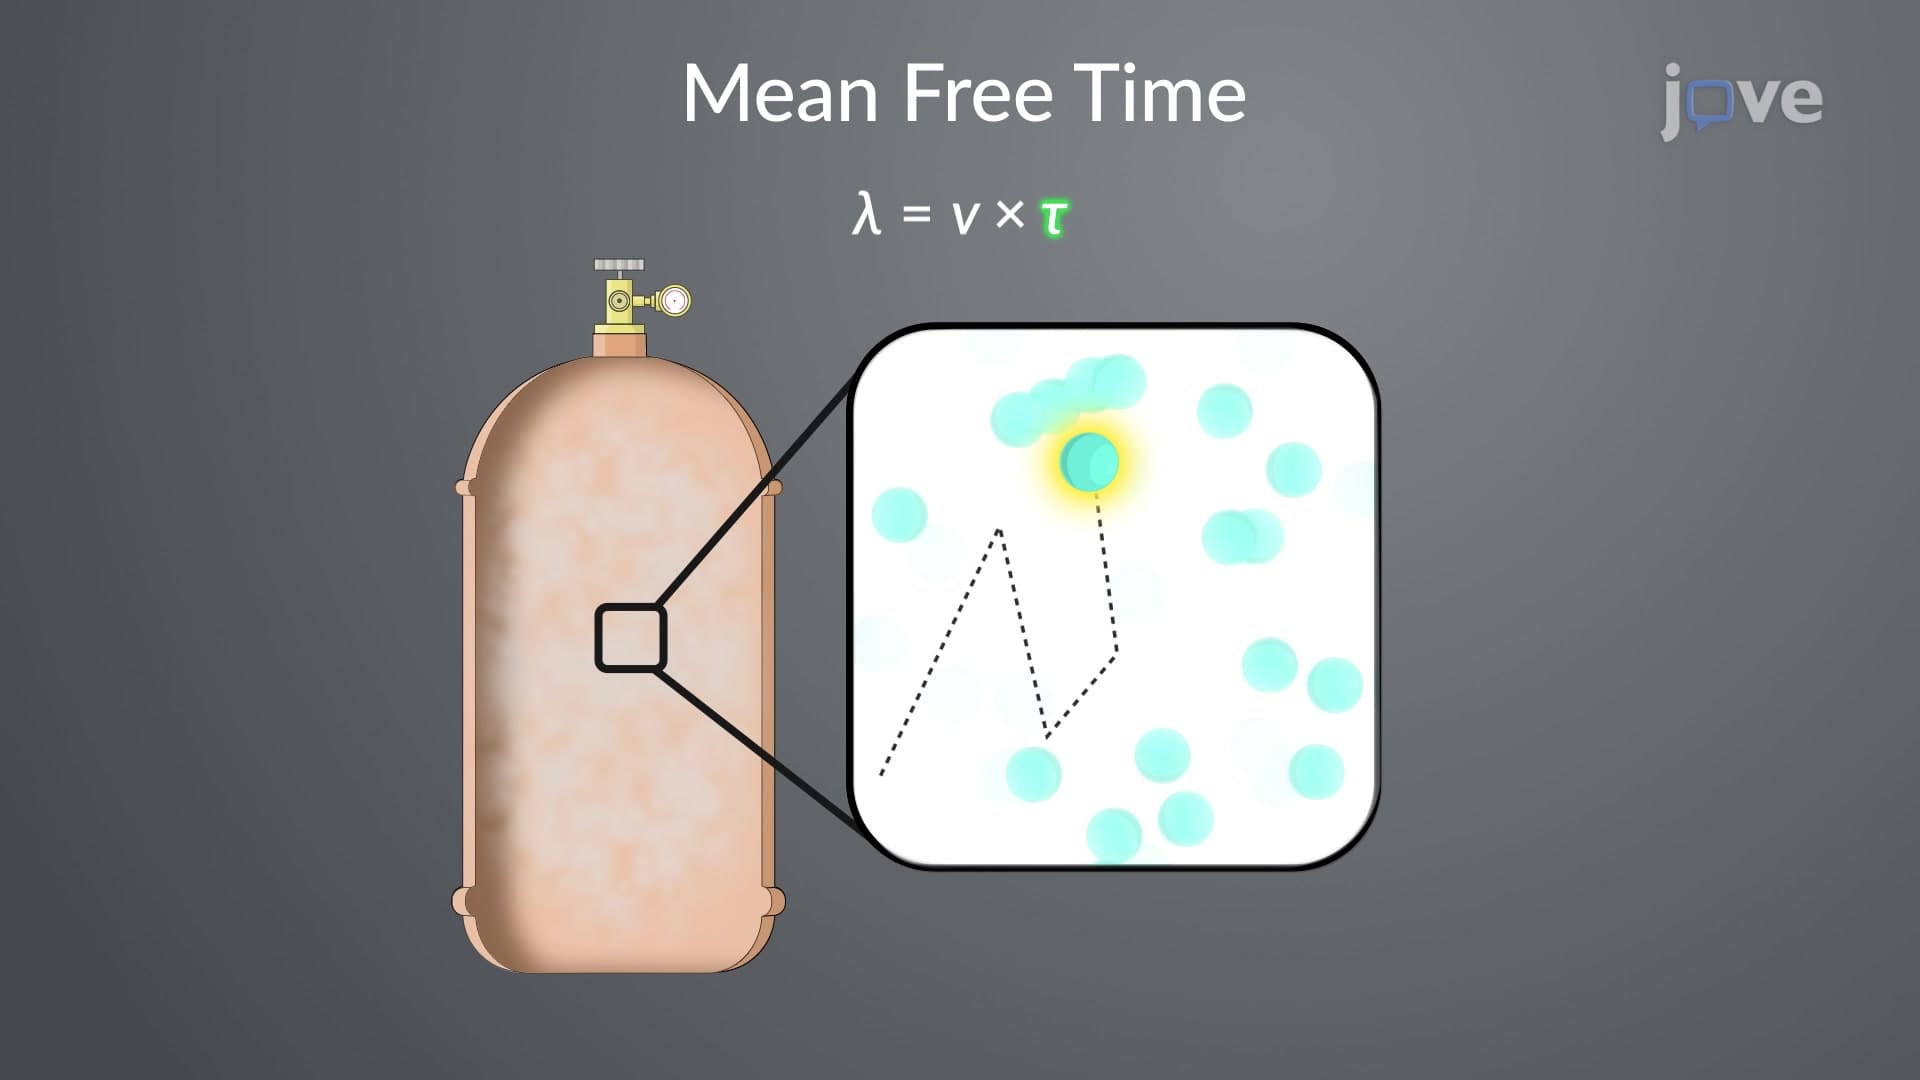
Mean free path and Mean free time
 01:19
Mixing Time
 01:22
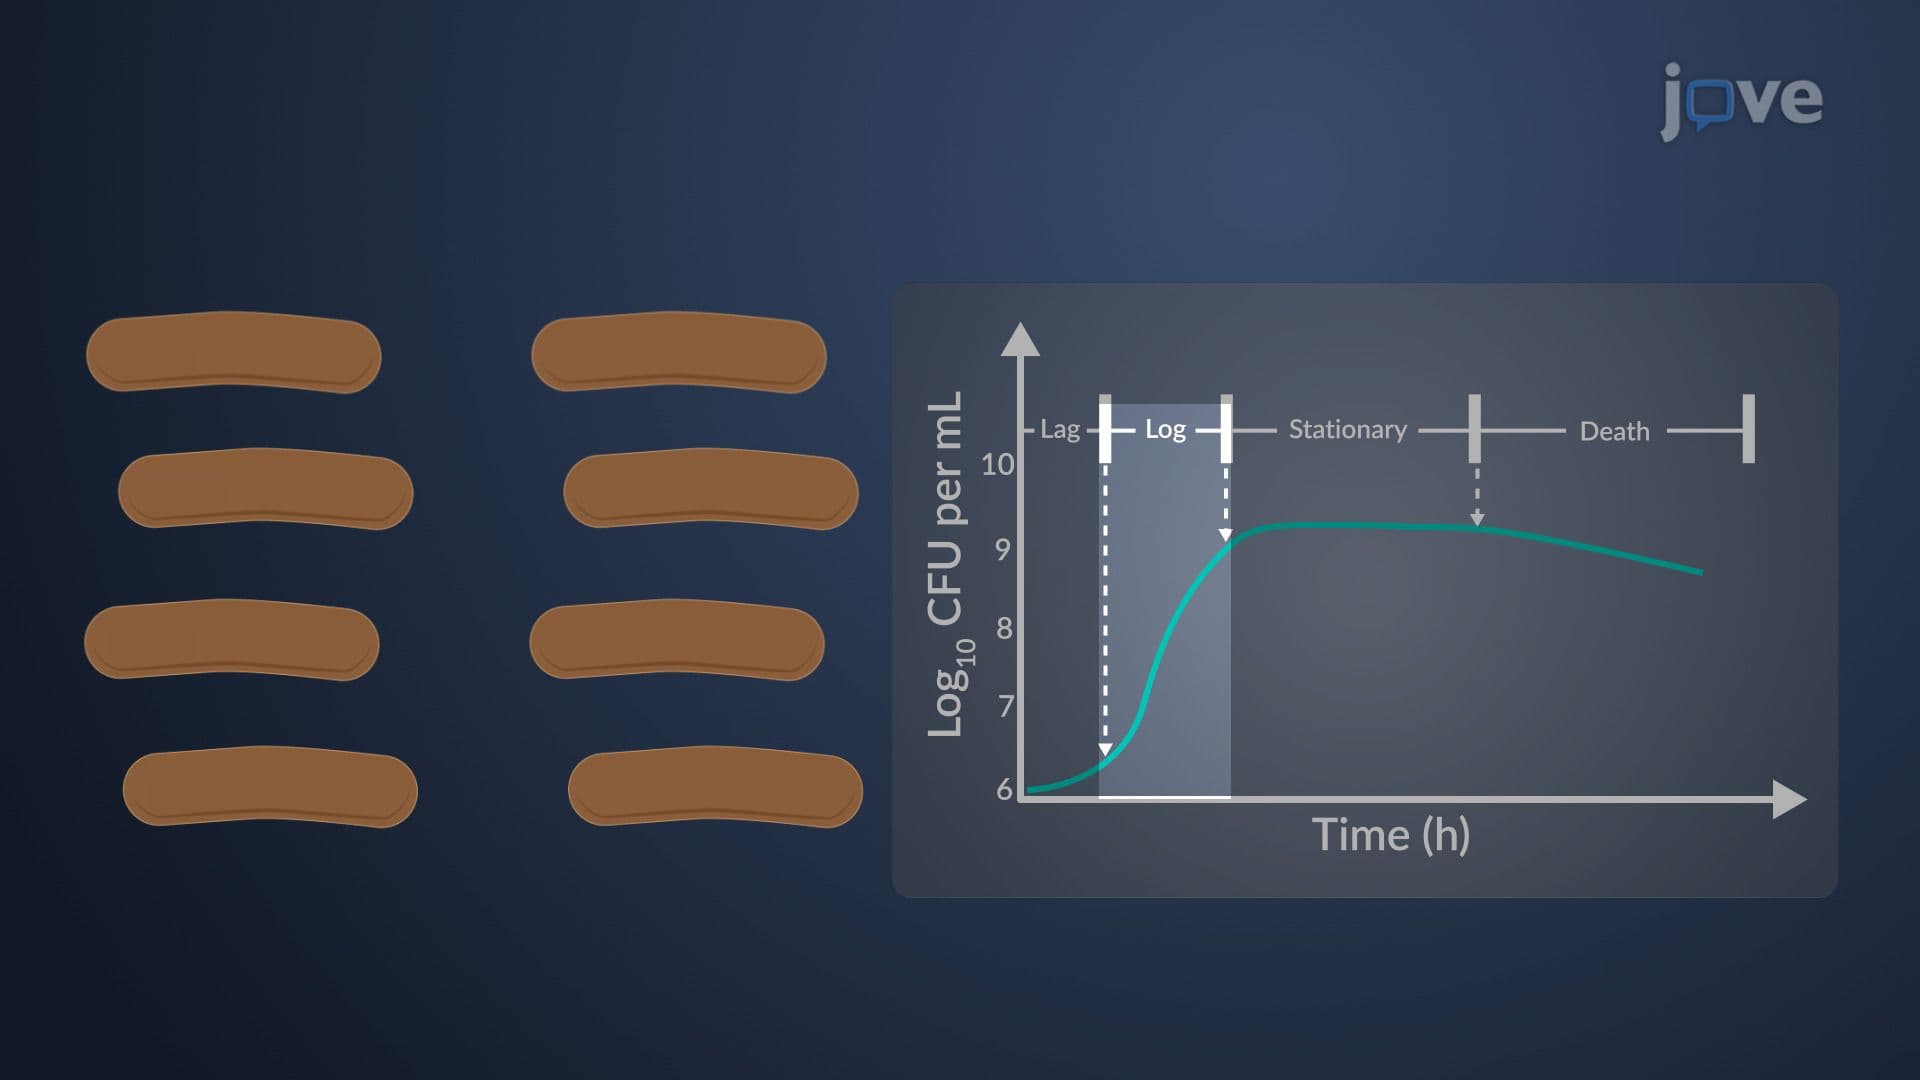
Generation Time
 01:14
Time Course of Drug Effect