Related Experiment Video
Updated: Feb 7, 2026
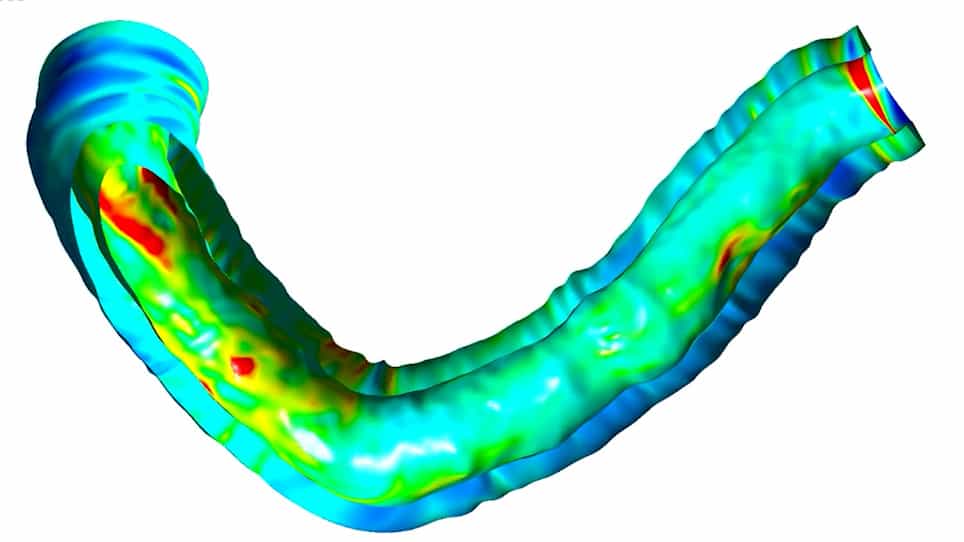

Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Saphenous graft atherosclerosis as assessed by optical coherence tomography data for stenotic and non-stenotic
Grzegorz M Kubiak1, Elżbieta Pociask2, Wojciech Wańha3
1Department of Cardiac Surgery and Transplantology, SMDZ in Zabrze, Medical University of Silesia in Katowice, Silesian Centre for Heart Disease, Zabrze, Poland.

Insights
Saphenous vein graft (SVG) plaque morphology, assessed by optical coherence tomography (OCT), reveals distinct characteristics in stenotic versus non-stenotic lesions. Intimal tearing or rupture (ITR) in SVGs is linked to poorer clinical outcomes and lower HDL cholesterol levels.
Area of Science:
- Cardiovascular Medicine
- Interventional Cardiology
- Biomedical Imaging
Background:
- Coronary artery bypass grafting (CABG) using saphenous vein grafts (SVGs) is a common treatment for diffuse coronary artery disease (CAD).
- SVG degeneration over time presents significant limitations, impacting long-term graft patency and patient outcomes.
- Understanding SVG plaque morphology is crucial for improving clinical management and therapeutic strategies.
Purpose of the Study:
- To investigate the relationship between saphenous vein graft (SVG) plaque morphology, as visualized by optical coherence tomography (OCT).
- To correlate specific OCT-assessed plaque characteristics with clinical findings in patients with SVG lesions.
- To elucidate the clinical implications of different SVG plaque morphologies.
Main Methods:
- Optical coherence tomography (OCT) imaging was employed to assess SVG plaque morphology in 29 patients.
- A comparative analysis was conducted between stenotic and non-stenotic SVG lesions within the OCTOPUS registry.
- Clinical data, including patient demographics, left ventricular ejection fraction (LVEF), and glomerular filtration rate (GFR), were correlated with OCT findings.
Main Results:
- Stenotic lesions exhibited a higher prevalence of thin-cap fibroatheroma (TCFA), thrombus, lipid-rich plaque (LRP), and plaque within the SVG valve compared to non-stenotic lesions.
- Patients with intimal tearing or rupture (ITR) were older, with reduced LVEF and GFR.
- Lower high-density lipoprotein (HDL) cholesterol levels were associated with calcified and ruptured plaques in SVGs.
Conclusions:
- The presence of intimal tearing or rupture (ITR) in SVGs is significantly associated with advanced age, impaired left ventricular ejection fraction (LVEF), and renal insufficiency.
- Reduced high-density lipoprotein (HDL) cholesterol concentrations correlate with an increased occurrence of calcified and ruptured plaques within saphenous vein grafts.
- OCT provides valuable insights into SVG plaque morphology, aiding in the understanding of graft degeneration and clinical outcomes.
Introduction:
Coronary artery bypass grafting (CABG), although widely used for a long time in diffuse coronary artery disease (CAD), has serious limitations associated with graft aging and its degeneration.
Aim:
The relationship between saphenous vein graft (SVG) plaque morphology assessed by optical coherence tomography (OCT) and clinical findings has not been elucidated yet.
Material And Methods:
We compared the morphology of SVG in stenotic vs. non-stenotic lesions using OCT imaging in 29 patients hospitalized in our center within the OCTOPUS registry.
Results:
Stenotic lesions were characterized by higher incidence of thin-cap fibroatheroma (TCFA) (33% vs. 0%, p = 0.0048), thrombus (28% vs. 0%, p = 0.0008), lipid-rich plaque (LRP) (75% vs. 35%, p = 0.0013) and plaque within the SVG valve (19% vs. 0%, p = 0.0114) as compared to non-stenotic lesions. Patients with intimal tearing or rupture (ITR) were older (75.8% vs. 68.9 years, p = 0.047) and had lower left ventricular ejection fraction (LVEF) (32.0% vs. 49.7%, p = 0.001) and glomerular filtration rate (GFR) (36.0 vs. 73.6 ml/min/1.73 m2, p = 0.010). Patients with calcified lesions vs. those without had lower high-density lipoprotein (HDL) cholesterol (33.2 vs. 44.1 mg/dl, p = 0.018), similarly to those with ruptured plaque vs. those without (28.3 vs. 41.7 mg/dl, p = 0.047).
Conclusions:
Presence of ITR was associated with advanced age, decreased LVEF and renal insufficiency. Decreased concentration of HDL was associated with higher occurrence of calcified and ruptured plaque.

Related Concept Videos
 01:17
Assessment of the Gastrointestinal System I: Subjective Data
Health History
The initial step in assessing the GI system is obtaining a comprehensive health history. This includes inquiring about the patient's history or presence of problems...
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...
 01:26
Atherosclerosis III: Management
 01:30
Atherosclerosis I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:23
Atherosclerosis IV: Nursing Management