Related Experiment Video
Updated: Feb 7, 2026
Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
Vesicoamniotic Shunting Improves Outcomes in a Subset of Prune Belly Syndrome Patients at a Single Tertiary Center
Jeffrey T White1,2, Kunj R Sheth1,2, Aylin N Bilgutay3
1Scott Department of Urology, Baylor College of Medicine, Houston, TX, United States.

Insights
Contemporary management of Prune Belly Syndrome (PBS) may reduce neonatal mortality. This rare condition often involves multiple congenital anomalies, with pulmonary issues in neonates and chronic kidney disease (CKD) in older children.
Area of Science:
- Pediatric Surgery
- Urology
- Genetics
Background:
- Prune Belly Syndrome (PBS) is a rare congenital disorder characterized by a triad of abdominal muscle deficiency, urinary tract abnormalities, and cryptorchidism.
- PBS is associated with significant morbidity and mortality, primarily due to pulmonary and renal complications.
Purpose of the Study:
- To review the outcomes of patients with Prune Belly Syndrome (PBS) managed with contemporary approaches.
- To test the hypothesis that modern management strategies improve mortality rates in PBS patients.
Main Methods:
- A retrospective chart review of 45 inpatient and outpatient PBS patients treated between 2000 and 2018.
- Data collected included demographics, medical conditions, imaging, surgical interventions, follow-up duration, and renal function.
- Patients were stratified according to the Woodard classification to analyze mortality trends.
Main Results:
- The neonatal mortality rate was 27% (12 deaths), primarily from cardiopulmonary complications.
- 36% of patients developed chronic kidney disease (CKD) stage 3 or higher; 7% received renal transplants.
- 84% of patients underwent surgery, with orchiopexy being the most common procedure (71%).
- A trend towards a 12% mortality improvement was observed in Woodard Classification 1 patients after valve-associated surgery (VAS).
Conclusions:
- Prune Belly Syndrome (PBS) patients commonly present with multiple congenital anomalies, including genitourinary, gastrointestinal, and cardiac defects.
- Pulmonary complications are frequent in neonates, while chronic kidney disease (CKD) is a significant concern in later childhood.
- Contemporary management, including prenatal interventions, appears to reduce neonatal mortality in a subset of PBS patients.
Abstract:
Objective: Review outcomes of Prune Belly Syndrome (PBS) with the hypothesis that contemporary management improves mortality. Methods: A retrospective chart review of inpatient and outpatient PBS patients referred between 2000 and 2018 was conducted to assess outcomes at our institution. Data collected included age at diagnosis, concomitant medical conditions, imaging, operative management, length of follow-up, and renal function. Results: Forty-five PBS patients presented during these 18 years. Prenatal diagnoses were made in 17 (39%); 65% of these patients underwent prenatal intervention. The remaining patients were diagnosed in the infant period (20, 44%) or after 1 year of age (8, 18%). Twelve patients died from cardiopulmonary complications in the neonatal period; the neonatal mortality rate was 27%. The mean follow-up among patients surviving the neonatal period was 84 months. Forty-two patients had at least one renal ultrasound (RUS); of the 30 patients with NICU RUSs, 26 (89%) had hydronephrosis and/or ureterectasis. Of the 39 patients who underwent voiding cystourethrogram (VCUG), 28 (62%) demonstrated VUR. Fifty-nine percent had respiratory distress. Nine patients (20%) were oxygen-dependent by completion of follow up. Thirty-eight patients (84%) had other congenital malformations including genitourinary (GU) 67%, gastrointestinal (GI) 52%, and cardiac 48%. Sixteen patients (36%) had chronic kidney disease (CKD) of at least stage 3; three patients (7%) had received renal transplants. Eighty-four percent of patients had at least one surgery (mean 3.4, range 0-6). The most common was orchiopexy (71%). The next most common surgeries were vesicostomy (39%), ureteral reimplants (32%), abdominoplasty (29%), nephrectomy (25%), and appendicovesicostomy (21%). After stratifying patients according to Woodard classification, a trend for 12% improvement in mortality after VAS was noted in the Woodard Classification 1 cohort. Conclusions: PBS patients frequently have multiple congenital anomalies. Pulmonary complications are prevalent in the neonate while CKD (36%) is prevalent during late childhood. The risk of CKD increased significantly with the presence of other congenital anomalies in our cohort. Mortality in childhood is most common in infancy and may be as low as 27%. Contemporary management of PBS, including prenatal interventions, reduced the neonatal mortality rate in a subset of our cohort.


Related Concept Videos
 01:13
Patient-centered Care
 01:26
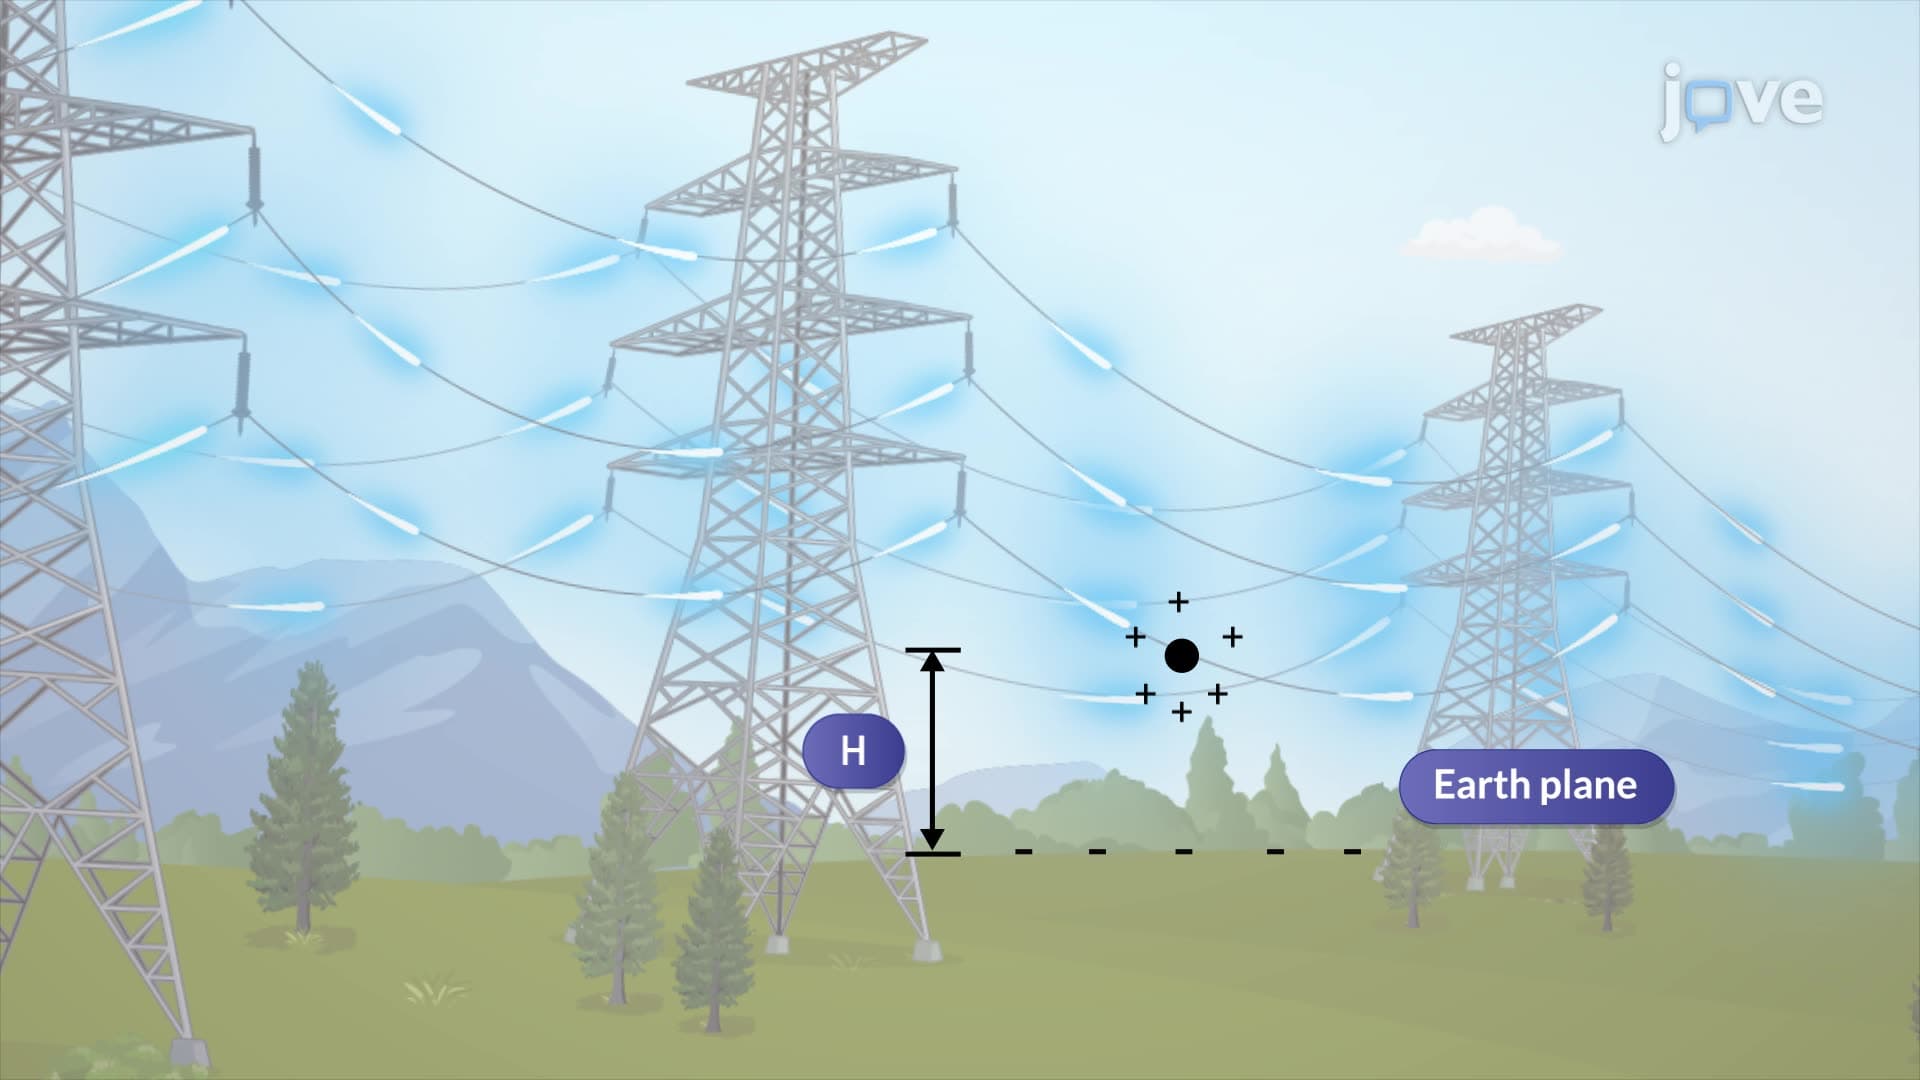
Shunt Admittances
To model this effect, the method of images is employed. This method involves replacing the Earth with an image conductor that mirrors the original...
 01:21
Tertiary Healthcare System
 01:12
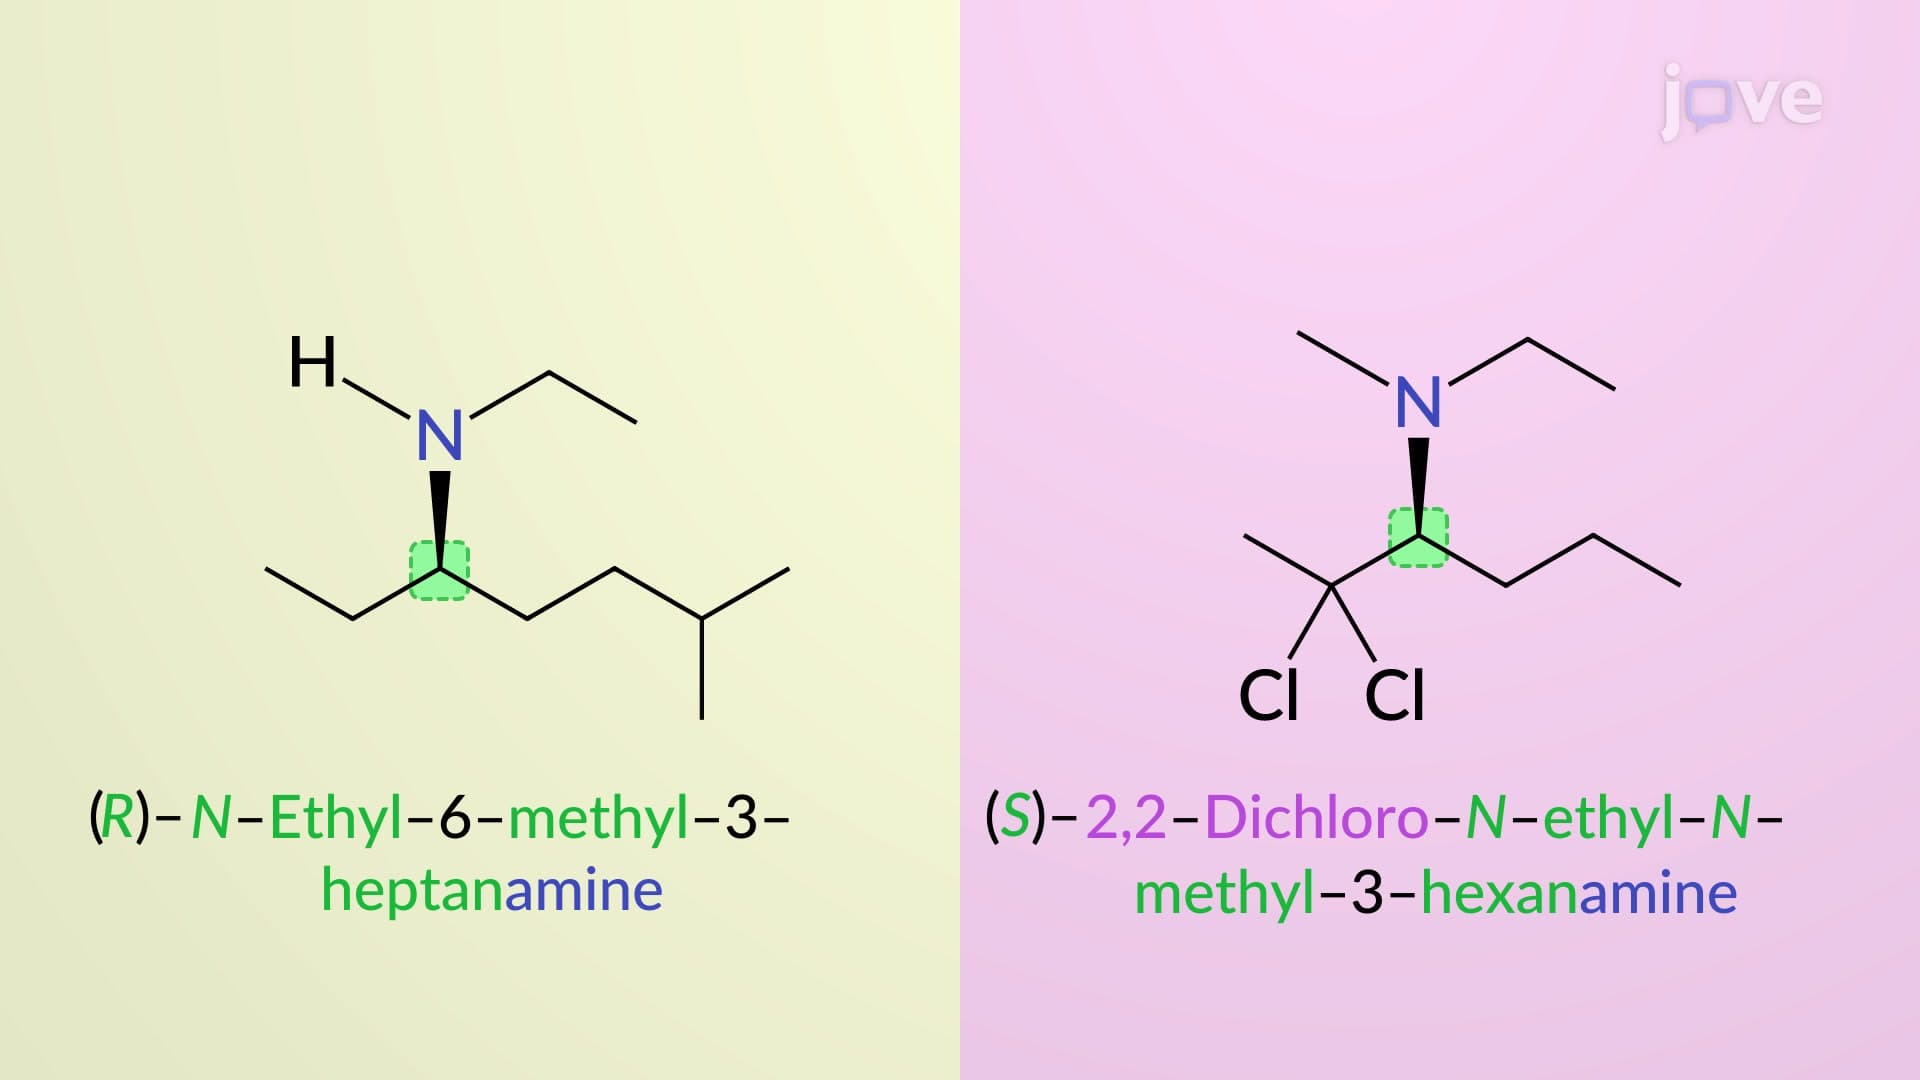
Nomenclature of Secondary and Tertiary Amines
 02:33
Lattice Centering and Coordination Number
Types of Unit Cells
Imagine taking a large number of identical...
 02:24
Predicting Reaction Outcomes