Related Experiment Video
Updated: Feb 7, 2026


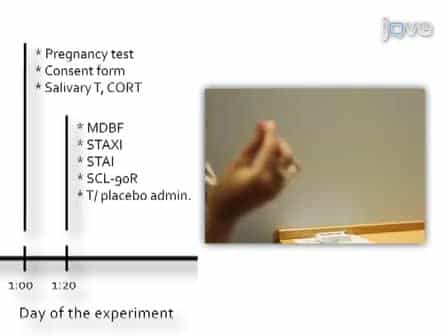
The Social Dimension of Stress: Experimental Manipulations of Social Support and Social Identity in the Trier Social Stress Test
Published on: November 19, 2015
Supporting shared decision making for older people with multiple health and social care needs: a realist synthesis
Frances Bunn1, Claire Goodman2, Bridget Russell2
1Centre for Research in Public Health and Community Care, University of Hertfordshire, College Lane, Hatfield, Hertfordshire, AL10 9AB, UK. f.bunn@herts.ac.uk.

Background:
Health care systems are increasingly moving towards more integrated approaches. Shared decision making (SDM) is central to these models but may be complicated by the need to negotiate and communicate decisions between multiple providers, as well as patients and their family carers; particularly for older people with complex needs. The aim of this review was to provide a context relevant understanding of how interventions to facilitate SDM might work for older people with multiple health and care needs, and how they might be applied in integrated care models.
Methods:
Iterative, stakeholder driven, realist synthesis following RAMESES publication standards. It involved: 1) scoping literature and stakeholder interviews (n = 13) to develop initial programme theory/ies, 2) systematic searches for evidence to test and develop the theories, and 3) validation of programme theory/ies with stakeholders (n = 11). We searched PubMed, The Cochrane Library, Scopus, Google, Google Scholar, and undertook lateral searches. All types of evidence were included.
Results:
We included 88 papers; 29 focused on older people or people with complex needs. We identified four context-mechanism-outcome configurations that together provide an account of what needs to be in place for SDM to work for older people with complex needs. This includes: understanding and assessing patient and carer values and capacity to access and use care, organising systems to support and prioritise SDM, supporting and preparing patients and family carers to engage in SDM and a person-centred culture of which SDM is a part. Programmes likely to be successful in promoting SDM are those that allow older people to feel that they are respected and understood, and that engender confidence to engage in SDM.
Conclusions:
To embed SDM in practice requires a radical shift from a biomedical focus to a more person-centred ethos. Service providers will need support to change their professional behaviour and to better organise and deliver services. Face to face interactions, permission and space to discuss options, and continuity of patient-professional relationships are key in supporting older people with complex needs to engage in SDM. Future research needs to focus on inter-professional approaches to SDM and how families and carers are involved.

Related Concept Videos
 01:21
Interdisciplinary Care: The Health Care Team-I
Physicians
The physician's primary responsibility is to diagnose illness and direct the medical or surgical treatment of the condition. The authority to admit patients to a healthcare agency or institution and practice care within that setting is granted to physicians by the healthcare agency or institution...
 01:18
Interdisciplinary Care: The Health Care Team-II
Physical Therapist
A physical therapist (PT) aims to restore function or prevent additional impairment in a patient following an injury or disease. Massage, heat, cold, water, sonar waves, exercises, and electrical stimulation are some treatments used by PTs to treat...
 01:41
Social Traps
 00:52
Social Proof
 01:18
Introduction To Health Care Delivery System
The Institute of Medicine (IOM) advocates for a patient-centered, effective, safe, timely, equitable, and effective healthcare system. The National Priorities...
 01:26
Traditional Level Of Health Care System
The preventive healthcare service includes tests for screening. Preventive health care services include identifying and reducing disease risk...