Related Experiment Video
Updated: Jun 22, 2026


Quantitative 3D In Silico Modeling (q3DISM) of Cerebral Amyloid-beta Phagocytosis in Rodent Models of Alzheimer's Disease
Published on: December 26, 2016
Inherited and Acquired Decrease in Complement Receptor 1 (CR1) Density on Red Blood Cells Associated with High Levels
Rachid Mahmoudi1,2, Sarah Feldman3,4, Aymric Kisserli5,6
1Department of Internal Medicine and Geriatrics, Reims University Hospitals, Maison Blanche Hospital, 45 rue cognac Jay, 51092 Reims, France. rmahmoudi@chu-reims.fr.

Insights
Alzheimer's disease (AD) is linked to lower complement receptor 1 (CR1) density on red blood cells, which may be acquired, not just inherited. This CR1 deficiency could impair amyloid clearance in AD.
Area of Science:
- Neuroscience
- Genetics
- Immunology
Background:
- The complement receptor 1 (CR1) gene is implicated in Alzheimer's disease (AD) pathogenesis.
- Previous research indicated AD is associated with reduced density of the long CR1 isoform, CR1*2 (S).
Purpose of the Study:
- To correlate CR1 phenotype data (CR1 density per erythrocyte (CR1/E), soluble CR1 (sCR1)) with CR1 genetic data (polymorphisms) in AD patients and healthy controls.
- To investigate the role of CR1 in AD pathogenesis and explore potential therapeutic targets.
Main Methods:
- CR1/E enumeration via flow cytometry and sCR1 quantification by ELISA.
- CR1 polymorphisms assessed using restriction fragment length polymorphism (RFLP), pyrosequencing, and high-resolution melting PCR.
- Multivariate analysis to determine associations between CR1 density, genetic factors, and methylation.
Main Results:
- AD patients with specific CR1 alleles (H or Q) exhibited significantly lower CR1/E compared to controls with the same alleles.
- AD patients showed significantly higher levels of sCR1 compared to controls.
- A reduction in CR1/E density was associated with increased CR1 methylation, suggesting acquired factors contribute to low CR1/E.
Conclusions:
- Low CR1/E density in AD is influenced by both inherited genetic factors and acquired epigenetic modifications.
- CR1's role in AD pathogenesis may involve impaired clearance of amyloid deposits.
- Findings suggest potential for novel therapeutic strategies targeting CR1 in AD treatment.
Abstract:
The complement receptor 1 (CR1) gene was shown to be involved in Alzheimer's disease (AD). We previously showed that AD is associated with low density of the long CR1 isoform, CR1*2 (S). Here, we correlated phenotype data (CR1 density per erythrocyte (CR1/E), blood soluble CR1 (sCR1)) with genetic data (density/length polymorphisms) in AD patients and healthy controls. CR1/E was enumerated using flow cytometry, while sCR1 was quantified by ELISA. CR1 polymorphisms were assessed using restriction fragment length polymorphism (RFLP), pyrosequencing, and high-resolution melting PCR. In AD patients carrying the H allele (HindIII polymorphism) or the Q allele (Q981H polymorphism), CR1/E was significantly lower when compared with controls carrying the same alleles (p < 0.01), contrary to sCR1, which was significantly higher (p < 0.001). Using multivariate analysis, a reduction of 6.68 units in density was associated with an increase of 1% in methylation of CR1 (estimate -6.68; 95% confidence intervals (CIs) -12.37, -0.99; p = 0.02). Our data show that, in addition to inherited genetic factors, low density of CR1/E is also acquired. The involvement of CR1 in the pathogenesis of AD might be linked to insufficient clearance of amyloid deposits. These findings may open perspectives for new therapeutic strategies in AD.
More Related Videos
Related Concept Videos
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:22
Alzheimer's Disease: Treatment
 01:27
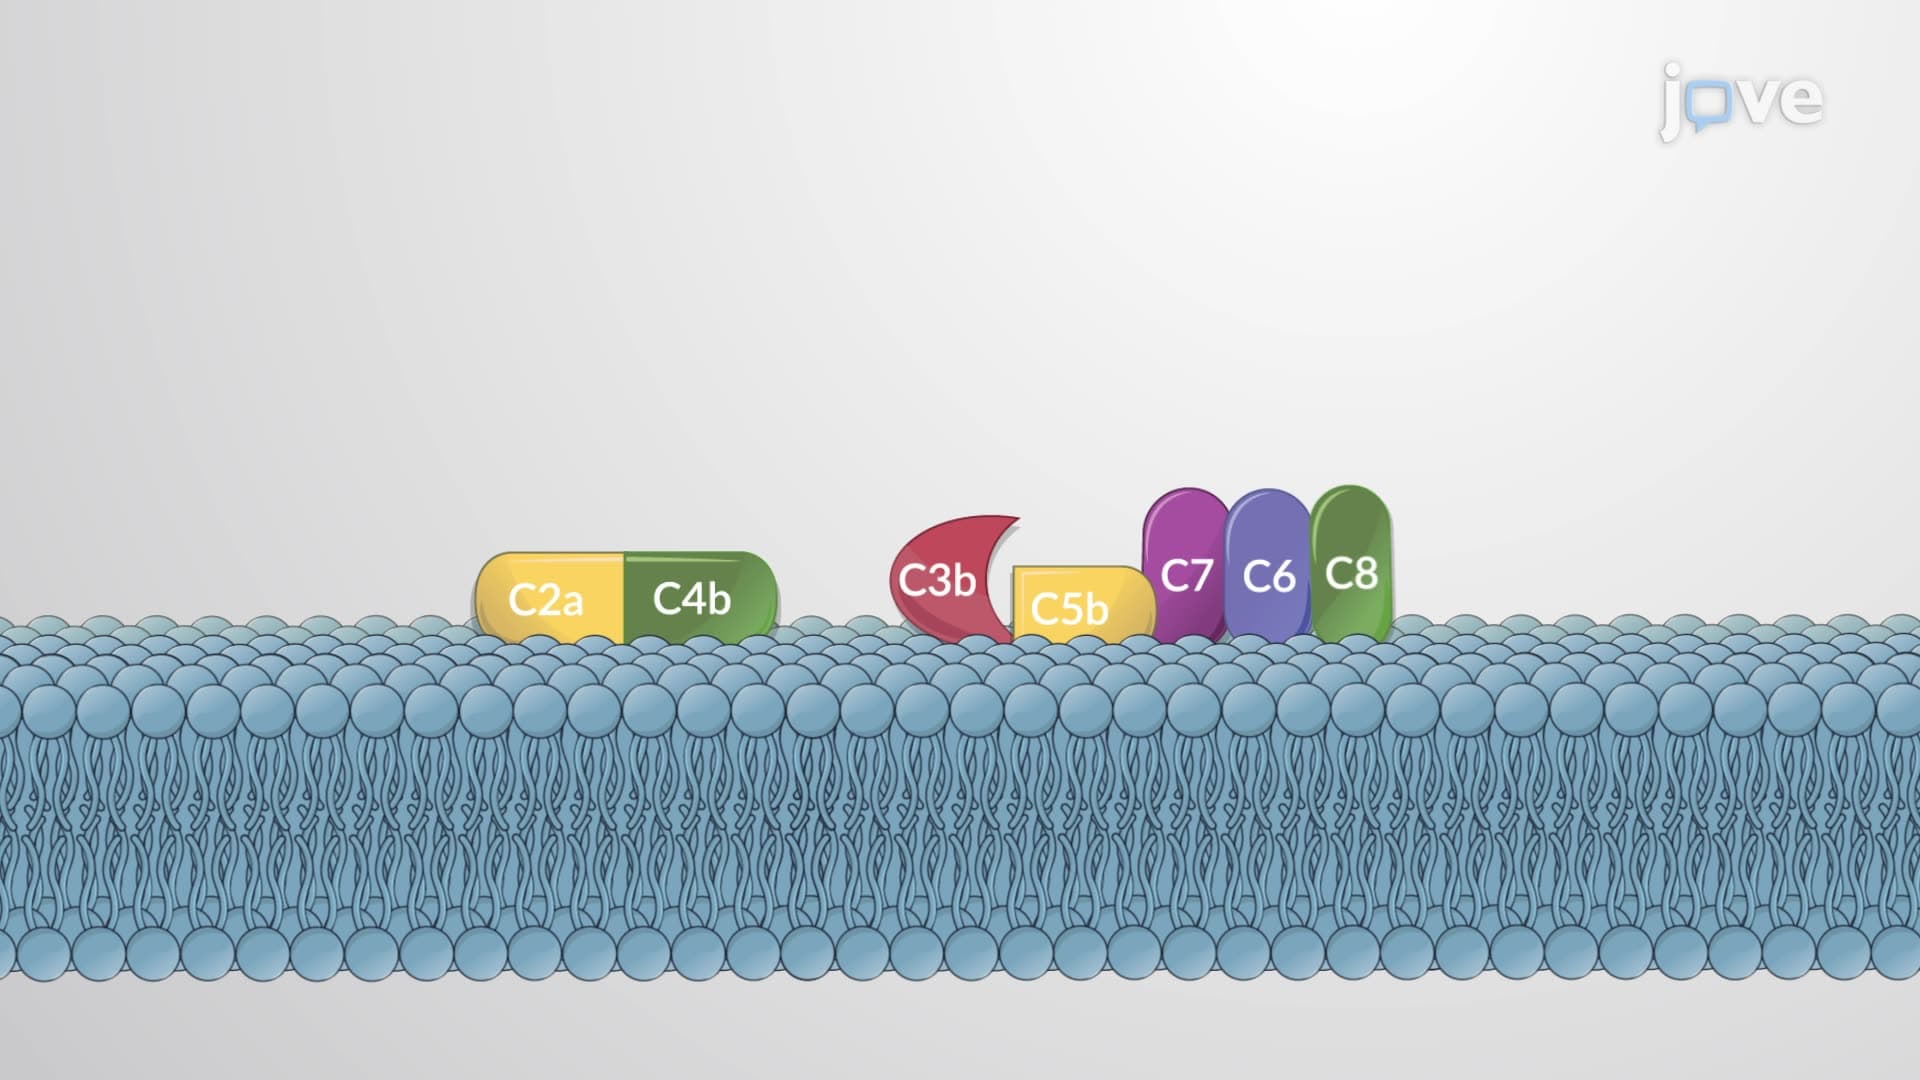
Complement System
 01:29
Alzheimer Disease l: Introduction
 01:23
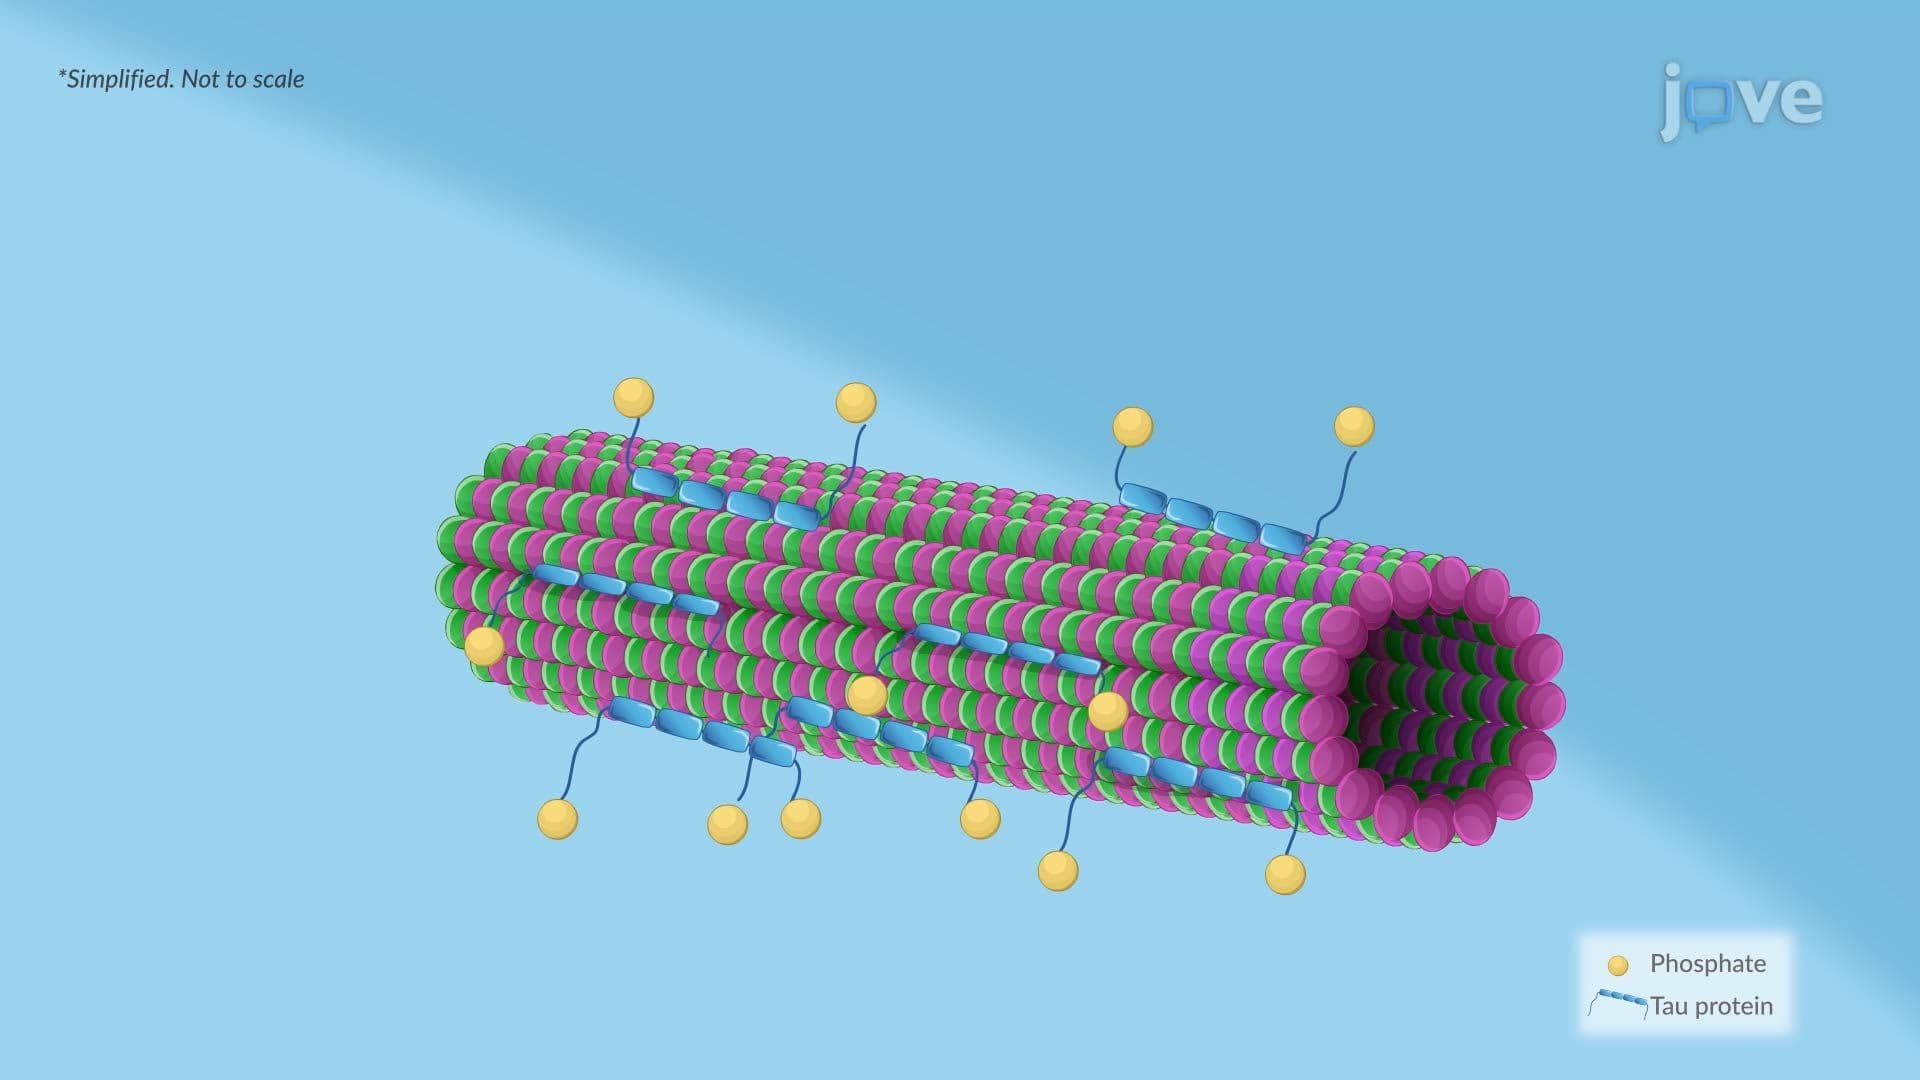
Alzheimer Disease ll: Pathophysiology
 01:22
Dementia l: Introduction