Related Experiment Video
Updated: Feb 7, 2026
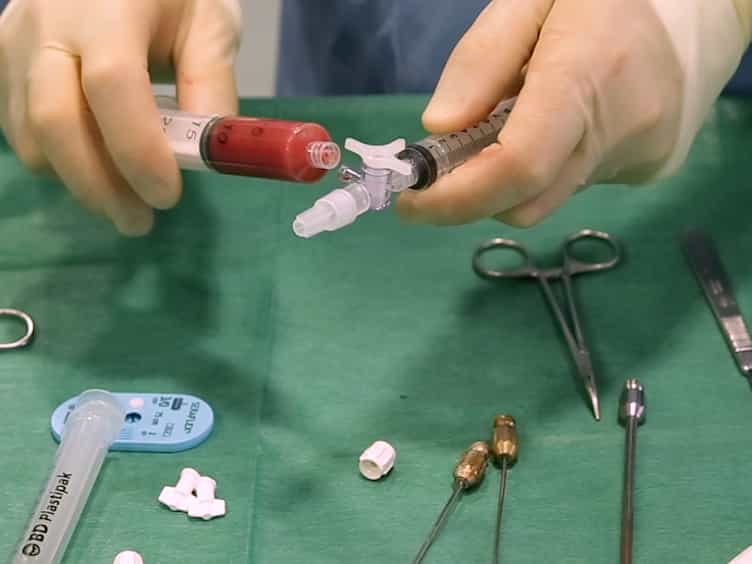
Regenerative Therapy by Suprachoroidal Cell Autograft in Dry Age-related Macular Degeneration: Preliminary In Vivo Report
Published on: February 12, 2018
Progression of Geographic Atrophy in Age-related Macular Degeneration: AREDS2 Report Number 16
Tiarnan D Keenan1, Elvira Agrón1, Amitha Domalpally2
1Division of Epidemiology and Clinical Applications, National Eye Institute, National Institutes of Health, Bethesda, Maryland.

Purpose:
To analyze the prevalence, incidence, and clinical characteristics of eyes with geographic atrophy (GA) in age-related macular degeneration (AMD), including clinical and genetic factors affecting enlargement.
Design:
Prospective cohort study within a controlled clinical trial.
Participants:
Age-Related Eye Disease Study 2 (AREDS2) participants, aged 50-85 years.
Methods:
Baseline and annual stereoscopic color fundus photographs were evaluated for GA presence and area. Analyses included GA prevalence and incidence rates, Kaplan-Meier rates, mixed-model regression, and multivariable analysis of the square root of GA, area adjusted for covariates, including clinical/imaging characteristics and genotype.
Main Outcome Measures:
(1) Presence or development of GA; (2) change in the square root of GA area over time.
Results:
At baseline, 517 eyes (6.2%) of 411 participants (9.8%) had pre-existing GA (without neovascular AMD), with the following characteristics: 33% central, 67% noncentral; and the following configurations: 36% small, 26% solid/unifocal, 24% multifocal, 9% horseshoe/ring, and 6% indeterminate. Of the remaining 6530 eyes at risk, 1099 eyes (17.3%) of 883 participants developed incident GA without prior neovascular disease during mean follow-up of 4.4 years. The Kaplan-Meier rate of incident GA was 19% of eyes at 5 years. In eyes with incident GA, 4-year risk of subsequent neovascular AMD was 29%. In eyes with incident noncentral GA, 4-year risk of central involvement was 57%. GA enlargement rate (following square root transformation) was similar in eyes with pre-existing GA (0.29 mm/year; 95% confidence interval 0.27-0.30) and incident GA (0.28 mm/year; 0.27-0.30). In the combined group, GA enlargement was significantly faster with noncentrality, multifocality, intermediate baseline size, and bilateral GA (P < 0.0001 for interaction in each case) but not with AREDS2 treatment assignment (P = 0.33) or smoking status (P = 0.05). Enlargement was significantly faster with ARMS2 risk (P < 0.0001), C3 non-risk (P = 0.0002), and APOE non-risk (P = 0.001) genotypes.
Conclusions:
Analyses of AREDS2 data on natural history of GA provide representative data on GA evolution and enlargement. GA enlargement, which was influenced by lesion features, was relentless, resulting in rapid central vision loss. The genetic variants associated with faster enlargement were partially distinct from those associated with risk of incident GA. These findings are relevant to further investigations of GA pathogenesis and clinical trial planning.
More Related Videos

Related Concept Videos
 01:24
Cattell's 16 Personality Factors
In contrast, source traits are the...
 01:25
Selected Data About Geographic Locations
 01:26
Aging
Cellular Clock Theory
The cellular clock theory posits that the human lifespan is closely tied to the finite capacity of cells to divide, a phenomenon governed by telomeres, which are protective caps at the ends of...
 01:24
Data Reporting and Recording
 02:07
Tumor Progression
Colon cancer is one of the best-documented examples of tumor progression. Early mutation in the APC gene in colon cells causes a small growth on the colon wall called a polyp. With time, this polyp grows into a benign, pre-cancerous tumor. Further...
 01:25
Types of Reports I: Hands-off Report
Following are the key components and categories of hand-off reports:
Purpose and Process: