Related Experiment Video
Updated: Feb 7, 2026

Adjustable Stiffness, External Fixator for the Rat Femur Osteotomy and Segmental Bone Defect Models
Published on: October 9, 2014
The management of infected nonunion of tibia with a segmental defect using simultaneous fixation with a monorail
S Gupta1, A Malhotra1, N Mittal1
1Department of Orthopaedics, Government Medical College Hospital, Chandigarh, India.

Aims:
The aims of this study were to establish whether composite fixation (rail-plate) decreases fixator time and related problems in the management of patients with infected nonunion of tibia with a segmental defect, without compromising the anatomical and functional outcomes achieved using the classical Ilizarov technique. We also wished to study the acceptability of this technique using patient-based objective criteria.
Patients And Methods:
Between January 2012 and January 2015, 14 consecutive patients were treated for an infected nonunion of the tibia with a gap and were included in the study. During stage one, a radical debridement of bone and soft tissue was undertaken with the introduction of an antibiotic-loaded cement spacer. At the second stage, the tibia was stabilized using a long lateral locked plate and a six-pin monorail fixator on its anteromedial surface. A corticotomy was performed at the appropriate level. During the third stage, i.e. at the end of the distraction phase, the transported fragment was aligned and fixed to the plate with two to four screws. An iliac crest autograft was added to the docking site and the fixator was removed. Functional outcome was assessed using the Association for the Study and Application of Methods of Ilizarov (ASAMI) criteria. Patient-reported outcomes were assessed using the Musculoskeletal Tumor Society (MSTS) score.
Results:
The mean age of patients was 38.1 years (sd 12.7). There were 13 men and one woman. The mean size of the defect was 6.4 cm (sd 1.3). the mean follow-up was 33.2 months (24 to 50). The mean external fixator index was 21.2 days/cm (sd 1.5). The complication rate was 0.5 (7/14) per patient. According to the classification of Paley, there were five problems and two obstacles but no true complications. The ASAMI bone score was excellent in all patients. The functional ASAMI scores were excellent in eight and good in six patients. The mean MSTS composite score was 83.9% (sd 7.1), with an MSTS emotional acceptance score of 4.9 (sd 0.5; maximum possible 5).
Conclusion:
Composite fixation (rail-plate) decreases fixator time and the associated complications, in the treatment of patients of infected nonunion tibia with a segmental defect. It also provides good anatomical and functional results with high emotional acceptance. Cite this article: Bone Joint J 2018;100-B:1094-9.
More Related Videos
 08:20
A Reliable and Reproducible Critical-Sized Segmental Femoral Defect Model in Rats Stabilized with a Custom External Fixator
Published on: March 24, 2019
 05:45
Author Spotlight: Exploring Regeneration in Axolotls Through Insights in Cellular and Molecular Mechanisms, Bone Healing, and Implications for Human Therapies
Published on: April 12, 2024
Related Concept Videos
 01:03
Fixation and Sectioning
The simplest type of preparation is the wet mount, in which the specimen is placed in a drop of liquid on the slide. A liquid specimen can be directly deposited on the slide using a dropper. Solid specimens, such as skin scraping, can be placed on the slide before adding a drop of liquid to prepare the wet mount. Sometimes the liquid is simply water, but stains are often added...
 01:28
Carbon-dioxide Fixation
 01:10
Bones of the Lower Limb: Tibia and Fibula
 01:16
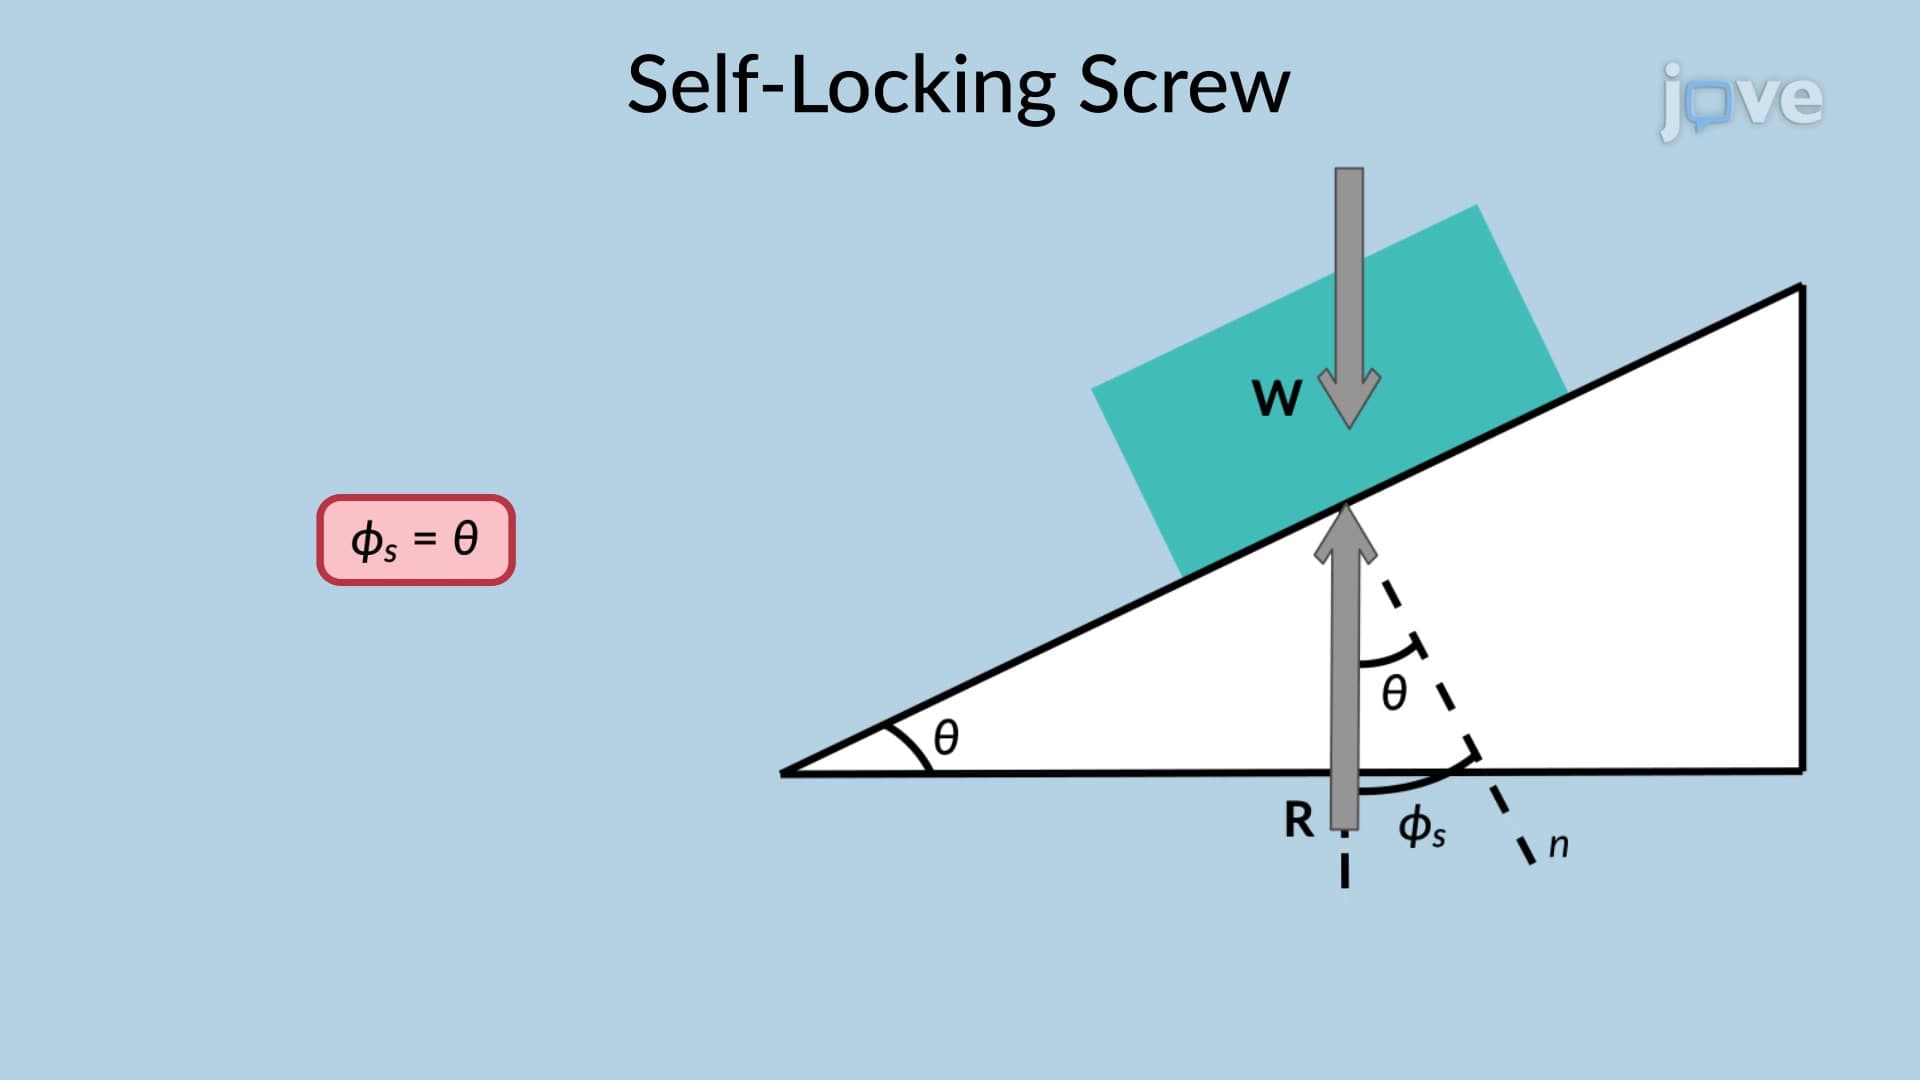
Self-Locking Screw
A square-threaded screw jack carrying a load is considered self-locking if the screw retains its position even after the moment applied to it is removed.
 01:17
Urinary Tract Infection IV: Nursing Management
 01:23
Lumber Defects
Shakes are minor fractures that run along or across the wood's annual rings, while wane is...