Related Experiment Video
Updated: Feb 7, 2026
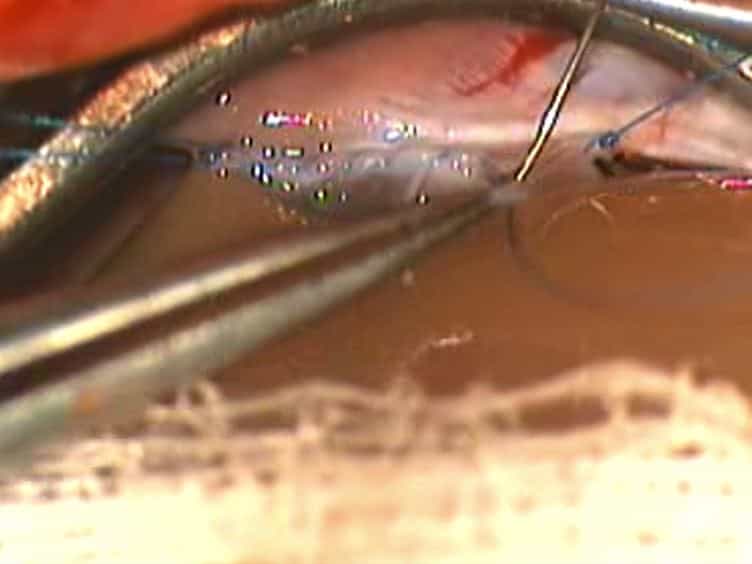

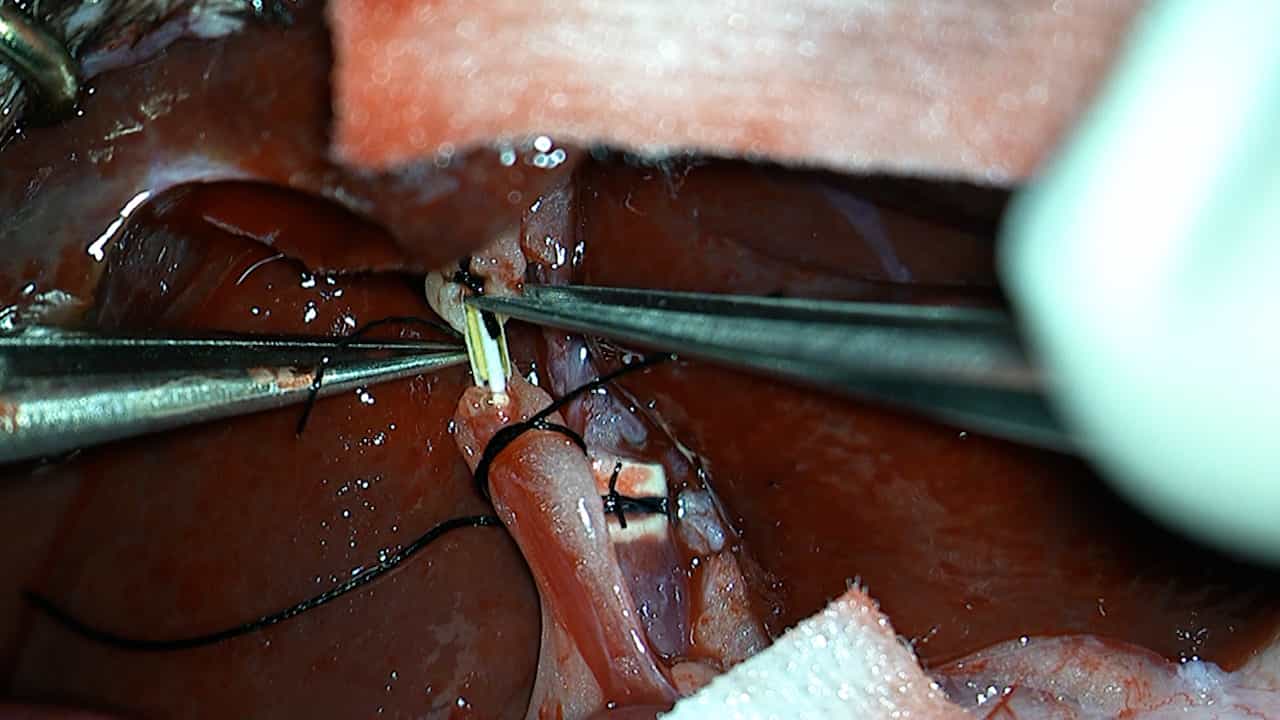
Surgical Procedures for a Rat Model of Partial Orthotopic Liver Transplantation with Hepatic Arterial Reconstruction
Published on: March 7, 2013
Immune-mediated graft dysfunction in liver transplant recipients with hepatitis C virus treated with direct-acting
Christine Chan1, Thomas Schiano2, Eliana Agudelo3
1Division of Gastroenterology and Hepatology, Northwestern University Feinberg School of Medicine, Chicago, IL, USA.

Interferon treatment of hepatitis C virus (HCV) infection after liver transplantation (LT) can result in immune-mediated graft dysfunction (IGD). The occurrence of, risk factors for, and outcomes of IGD with direct-acting antiviral (DAA) therapy have not been reported. We conducted a multicenter study of HCV+LT recipients who did or did not develop DAA-IGD (1 case: 2 controls-33 vs 66). Among all treated between 2014 and 2016, DAA-IGD occurred in 3.4% (33/978). IGD occurred only after treatment completion (76.0 [IQR, 47.0;176]). Among those treated, 48% had plasma cell hepatitis, 36% acute cellular rejection, 6% chronic rejection, and 9% combined findings. Median time to liver enzyme resolution was 77.5 days (IQR, 31.5;126). After diagnosis, hospitalizations, steroid-induced hyperglycemia, and infection occurred in a higher percentage of cases vs controls (33% vs 7.5%, 21% vs 1.5%, 9% vs 0%; all P < .05). Only one IGD patient died and none required retransplant. A multivariate regression analysis found that liver enzyme elevations during and soon after DAA therapy completion correlated with subsequent IGD. In conclusion, while DAA-IGD is uncommon, liver enzyme elevations during or after DAA therapy may be a sign of impending IGD. These indicators should guide clinicians to diagnose and treat IGD early before the more deleterious later clinical presentation.
Interferon treatment of hepatitis C virus (HCV) infection after liver transplantation (LT) can result in immune-mediated graft dysfunction (IGD). The occurrence of, risk factors for, and outcomes of IGD with direct-acting antiviral (DAA) therapy have not been reported. We conducted a multicenter study of HCV+LT recipients who did or did not develop DAA-IGD (1 case: 2 controls-33 vs 66). Among all treated between 2014 and 2016, DAA-IGD occurred in 3.4% (33/978). IGD occurred only after treatment completion (76.0 [IQR, 47.0;176]). Among those treated, 48% had plasma cell hepatitis, 36% acute cellular rejection, 6% chronic rejection, and 9% combined findings. Median time to liver enzyme resolution was 77.5 days (IQR, 31.5;126). After diagnosis, hospitalizations, steroid-induced hyperglycemia, and infection occurred in a higher percentage of cases vs controls (33% vs 7.5%, 21% vs 1.5%, 9% vs 0%; all P < .05). Only one IGD patient died and none required retransplant. A multivariate regression analysis found that liver enzyme elevations during and soon after DAA therapy completion correlated with subsequent IGD. In conclusion, while DAA-IGD is uncommon, liver enzyme elevations during or after DAA therapy may be a sign of impending IGD. These indicators should guide clinicians to diagnose and treat IGD early before the more deleterious later clinical presentation.

Related Concept Videos
 01:31
Direct-Acting Cholinergic Agonists: Pharmacokinetics
 01:11
Direct-Acting Cholinergic Agonists: Therapeutic Uses
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 00:59
Gene Therapy
 00:59
Direct-Acting Cholinergic Agonists: Pharmacological Actions
 01:40
Cell-mediated Immune Responses