Related Experiment Video
Updated: Feb 7, 2026


Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
Continuous administration of ramosetron with patient-controlled analgesia after laparoscopic distal gastrectomy does
Hong Soo Jung1, Jaewon Huh, Youngchan Kim
1Department of Anesthesiology and Pain Medicine, St. Vincent's Hospital Department of Anesthesiology and Pain Medicine, Seoul St. Mary's Hospital, The Catholic University of Korea, Seoul, Korea.

Background:
Currently, 5-hydroxytryptamine type 3 (5-HT3) receptor antagonists are indicated to slow gastrointestinal motility in the diarrhea-predominant subtype of irritable bowel syndrome. They are commonly used to prevent or treat postoperative nausea and vomiting (PONV) and opioid-induced nausea and vomiting (OINV). We conducted a prospective, randomized, double-blinded study to investigate whether the continuous administration of ramosetron, a selective 5-HT3 receptor antagonist, for preventing PONV and/or OINV after laparoscopic distal gastrectomy (LDG) might influence bowel function recovery.
Methods:
Patients scheduled to undergo LDG were randomly assigned to 1 of 3 treatment regimens: no prophylactic ramosetron (Group C); ramosetron 0.6 mg added to 2-day intravenous patient-controlled analgesia (IV-PCA) (Group R0.6); and ramosetron 1.2 mg added to 2-day IV-PCA (Group R1.2). Postoperative recovery profiles of bowel function, incidence of postoperative nausea/vomiting and pain, and perioperative data that affected bowel function recovery were evaluated.
Results:
Seventy-three patients completed the study protocol. Parameters associated with postoperative recovery of bowel function, such as time to first flatus, time to first bowel movement, time to first defecation, and time to commencement of soft diet, were not significantly different between the 3 groups. The incidence of nausea 2 to 24 hours after surgery was significantly lower in Group R0.6 (20.0%) and Group R1.2 (12.5%) than in Group C (45.8%) (P < .022). The ratio of complete response 2 to 24 hours after surgery was significantly higher in Group R0.6 (80.0%) and Group R1.2 (87.5%) than in Group C (54.2%) (P < .022). The incidence of retching 24 to 48 hours after surgery was significantly lower in Group R0.6 (0.0%) and Group R1.2 (4.2%) than in Group C (16.7%) (P < .043).
Conclusion:
Continuous administration of ramosetron with patient-controlled analgesia to prevent PONV and OINV after LDG did not delay postoperative bowel function recovery.

Related Concept Videos
 02:07
Blind Procedures
 01:23
Continuity of a Function
 01:29
Properties of Continuous Functions
 01:11
Blinding
 01:20
Bioequivalence Experimental Study Designs: Completely Randomized and Randomized Block Designs
 01:21
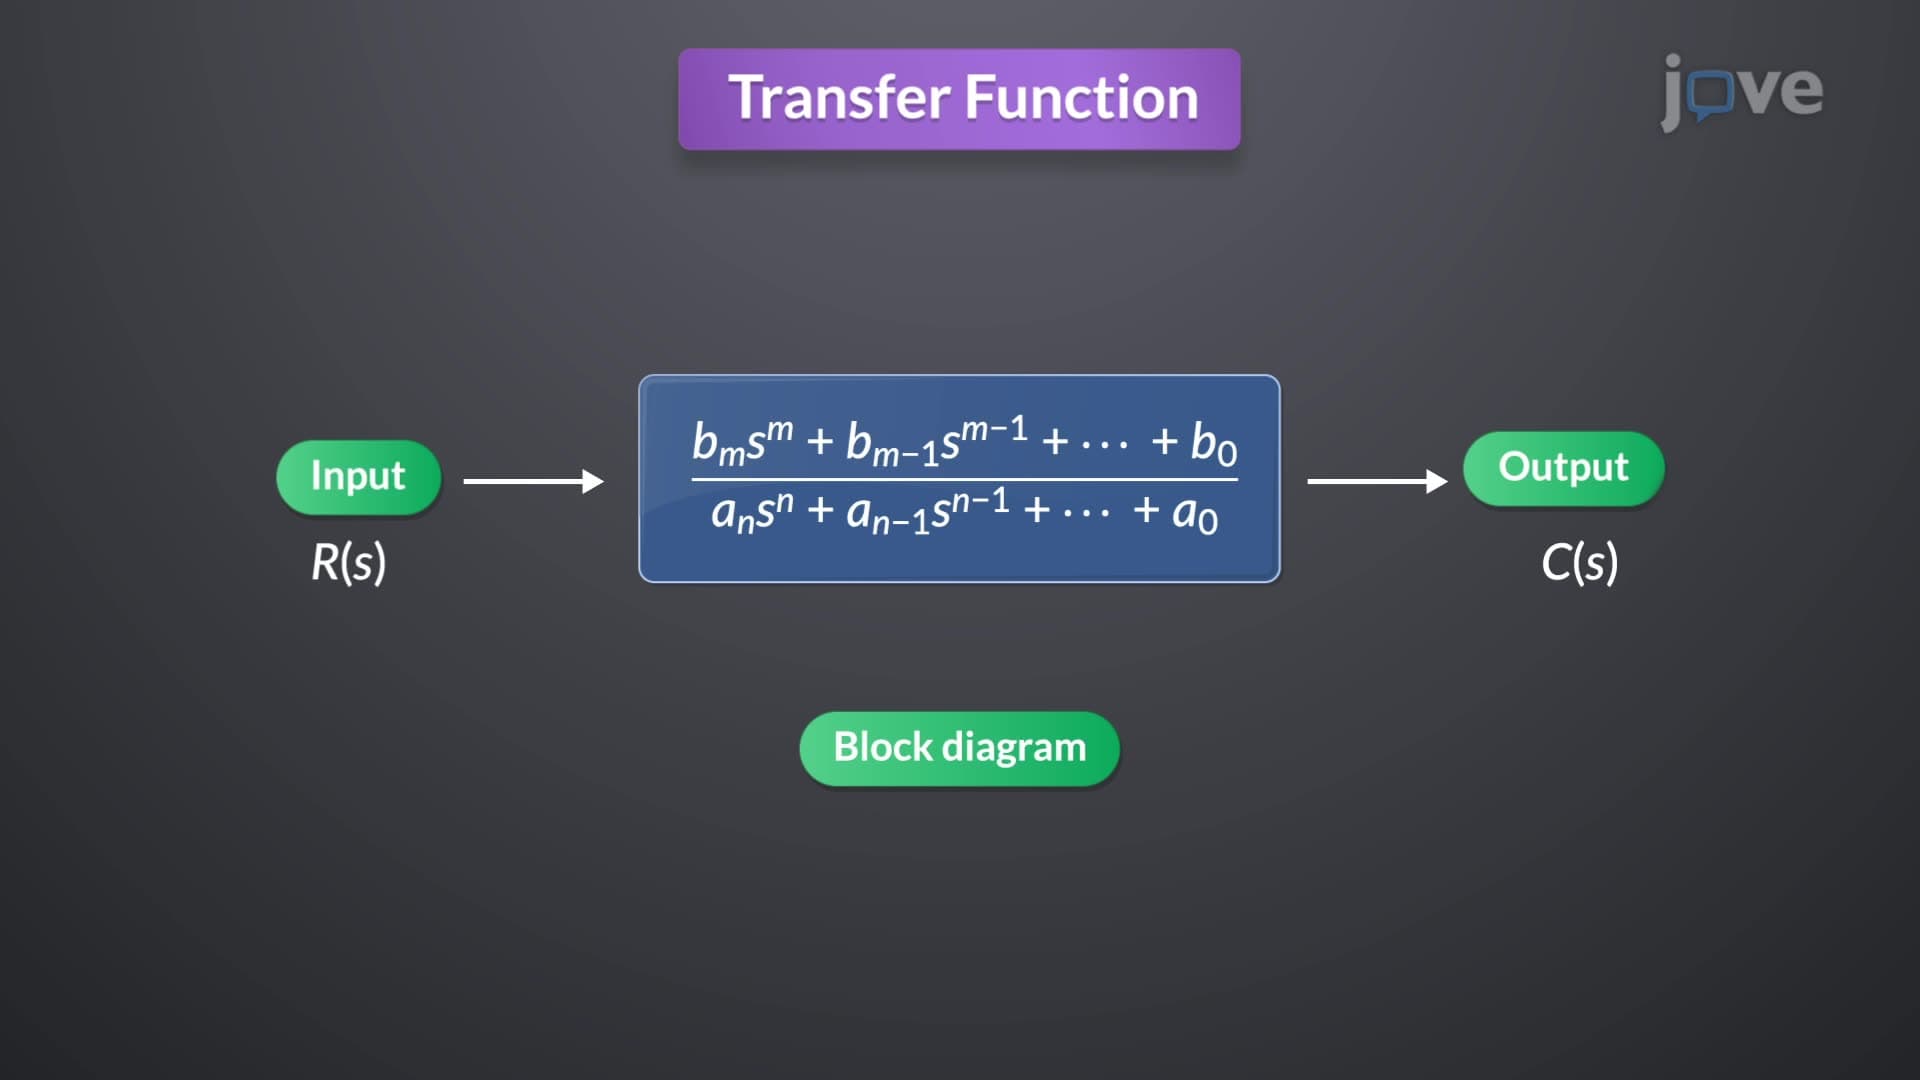
Transfer Function in Control Systems
To derive the transfer function, consider a general nth-order linear time-invariant...