Related Experiment Video
Updated: Feb 7, 2026
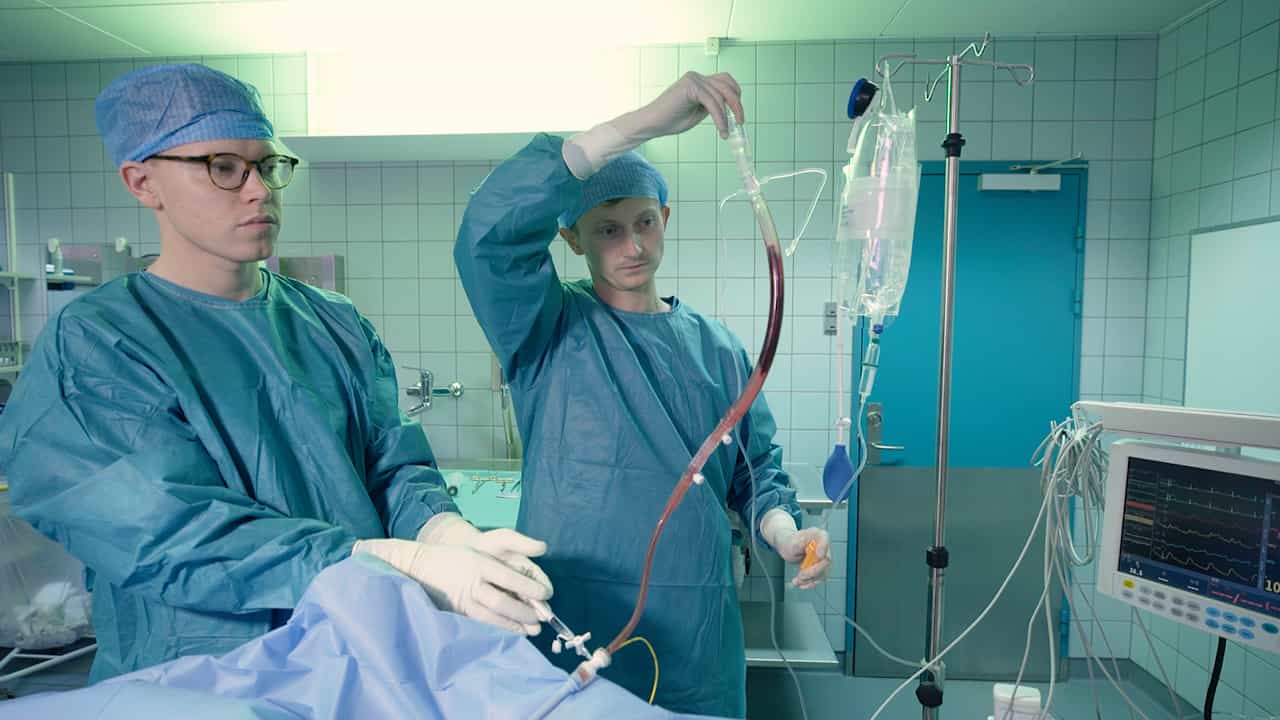

A Porcine Model of Acute Autologous Pulmonary Embolism
Published on: September 6, 2024
Comparison of the age-adjusted and clinical probability-adjusted D-dimer to exclude pulmonary embolism in the ED
Sameer Sharif1, Michelle Eventov2, Clive Kearon3
1Department of Medicine, Division of Emergency Medicine McMaster University, Canada.

Background:
Diagnosing pulmonary embolism (PE) in the emergency department (ED) can be challenging because its signs and symptoms are non-specific.
Objective:
We compared the efficacy and safety of using age-adjusted D-dimer interpretation, clinical probability-adjusted D-dimer interpretation and standard D-dimer approach to exclude PE in ED patients.
Design/Methods:
We performed a health records review at two emergency departments over a two-year period. We reviewed all cases where patients had a D-dimer ordered to test for PE or underwent CT or VQ scanning for PE. PE was considered to be present during the emergency department visit if PE was diagnosed on CT or VQ (subsegmental level or above), or if the patient was subsequently found to have PE or deep vein thrombosis during the next 30 days. We applied the three D-dimer approaches to the low and moderate probability patients. The primary outcome was exclusion of PE with each rule. Secondary objective was to estimate the negative predictive value (NPV) for each rule.
Results:
1163 emergency patients were tested for PE and 1075 patients were eligible for inclusion in our analysis. PE was excluded in 70.4% (95% CI 67.6-73.0%), 80.3% (95% CI 77.9-82.6%) and 68.9%; (95% CI 65.7-71.3%) with the age-adjusted, clinical probability-adjusted and standard D-dimer approach. The NPVs were 99.7% (95% CI 99.0-99.9%), 99.1% (95% CI 98.3-99.5%) and 100% (95% CI 99.4-100.0%) respectively.
Conclusion:
The clinical probability-adjusted rule appears to exclude PE in a greater proportion of patients, with a very small reduction in the negative predictive value.


Related Concept Videos
 01:25
The Anchoring-and-Adjustment Heuristic
 01:12
Adjusting a Traverse
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:29
Pulmonary Embolism I: Introduction
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:27
Pulmonary Embolism III: Nursing Management