Related Experiment Video
Updated: Feb 7, 2026

Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
A comparison between the 1981 and 2017 International League Against Epilepsy classification of seizure types based on
Hui Gao1, Josemir W Sander2, Yingfeng Xiao1
1Department of Neurology, West China Hospital, Sichuan University, Chengdu, China.

Abstract:
To compare between the 1981 and 2017 International League Against Epilepsy (ILAE) classification of seizure types based on an outpatient setting. We retrospectively reviewed 200 patients from our outpatient epilepsy registry. Based on clinical information, their seizure types were classified according to ILAE official reports, and differences between the 1981 and 2017 classifications were compared. All unclassifiable cases based on either one or both classification systems were discussed. The 200 patients had a total of 243 manifestations. Some terms in the 2017 classification clearly correspond to those of the 1981 classification, while others lack clarity and are more controversial. The three most frequently encountered seizure types based on the 2017 classification were focal to bilateral tonic-clonic (83; 34.1%), unknown-onset tonic-clonic (56; 23.0%), and focal impaired awareness (52; 21.4%). Based on the 1981 classification, the three most frequently encountered seizure types were unclassified (89; 36.6%), secondary generalized tonic-clonic (sGTCS) (83; 34.1%), and complex partial (CPS) (36; 14.8%). Seventy-five of 89 (84.3%) unclassified cases based on the 1981 classification were classified using the 2017 classification mainly due to the addition of the "unknown origin" category and a combination of different levels of terms (level of awareness and motor/non-motor features). In 14 cases, seizures were unclassifiable using both classification systems; eight were rare manifestations with unclear awareness or unusual bilateral movements and six were due to a lack of detailed description. The 2017 seizure classification greatly reduces the number of unclassifiable cases. The combination of awareness level and motor/non-motor features introduces greater flexibility and allows for detailed seizure description. Several cases, however, remain unclassified, but these are mostly due to a lack of understanding of epilepsy. The 2017 seizure classification demonstrates a steady transition from the 1981 classification with acceptable consistency and improvements.
Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types:
 01:01
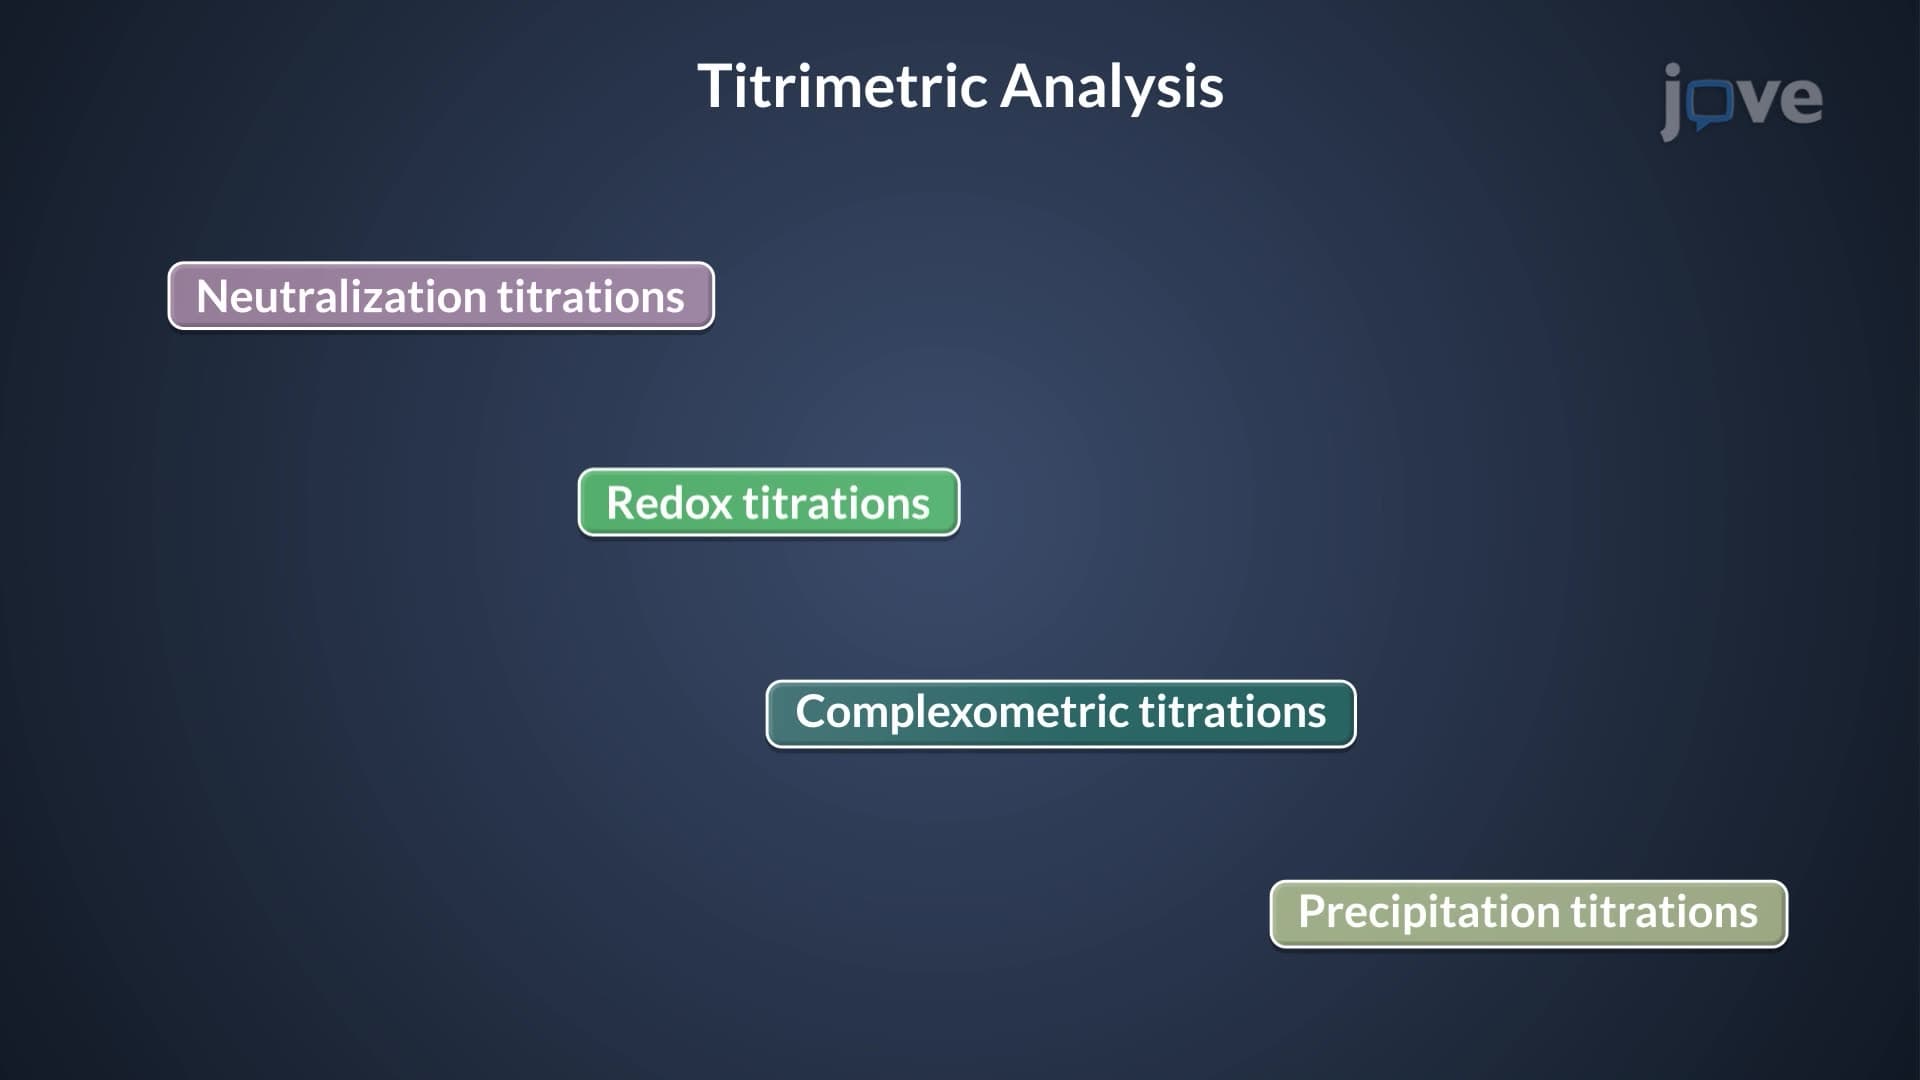
Classification of Titrimetric Analysis Based on Reaction Types
Titrations between an acid and a base lead to neutralization reactions that form...
 01:07
Types of Receptors: Internal Receptors
Similar to membrane-bound receptors, the binding of a ligand to the intracellular receptor of causes a conformational change in the...
 02:57
The Sense of Self: Reflected Self-Appraisal and Social Comparison
 02:00
Internal Energy