Related Experiment Video
Updated: Feb 7, 2026


Murine Surgical Model of Topical Elastase Induced Descending Thoracic Aortic Aneurysm
Published on: August 24, 2019
Revised Endografting for a Giant Descending Thoracic Aorta Aneurysm due to Synchronous Type III/Ib Endoleak, Causing
George S Georgiadis1, Christos Argyriou1, Andreas Koutsoumpelis1
1Department of Vascular Surgery, "Democritus" University of Thrace, University General Hospital of Alexandroupolis, Alexandroupolis, Greece.

Background:
Although surgical resection and graft replacement therapy for thoracic aortic aneurysms has advanced greatly over the last 20 years, significant perioperative morbidity and mortality still occur, particularly in patients considered high risk due to significant coexisting medical illness or previous operations performed for the treatment of intrathoracic disease.
Methods:
The case described is that of a patient with a giant (13.8 cm) symptomatic descending thoracic aorta aneurysm (DTAA), previously treated endovascularly 15 years ago. The expanding aneurysm was due to undiagnosed synchronous type III/Ib endoleak resulting in chronic malnutrition and eventually dysphagia and dyspnea due to compressive symptoms of the esophagus. Besides the risk of rupture, dyspnea and dysphagia with progressive weight loss were significant indications necessitating repair. Regarding his major comorbidities, the patient was identified as high risk for open surgical repair, therefore an endovascular option was offered. Two valiant tube endografts were inserted and deployed successfully without complications.
Results:
Postoperatively, upper gastrointestinal endoscopy imaging that was performed to the patient revealed marked persistent stenosis of the esophagus despite aneurysm pressure relief. However, at the multidisciplinary team meeting, an esophageal stenting was ruled out due to the risk of stent fracture and esophageal perforation with its devastating complications. Therefore, a conservative management was deemed appropriate for the patient taking into consideration the risks of prolonged hospitalization and malnourishment coupled with an unpredictable clinical course regarding the remission of the symptoms. Despite the slight gradual clinical improvement in the immediate postoperative period, the patient passed away at the 40th postoperative day due to hospital acquired pneumonia.
Conclusions:
Following endovascular repair of giant DTAA compressing the esophagus, significant symptomatic improvement should not be always expected due to the large residual thrombotic aneurysm sac. Although compression symptoms can be managed conservatively in patients deemed at high risk for esophageal perforation, postoperative course and management is of paramount importance and should be treated on an individual basis.

Related Concept Videos
 01:15
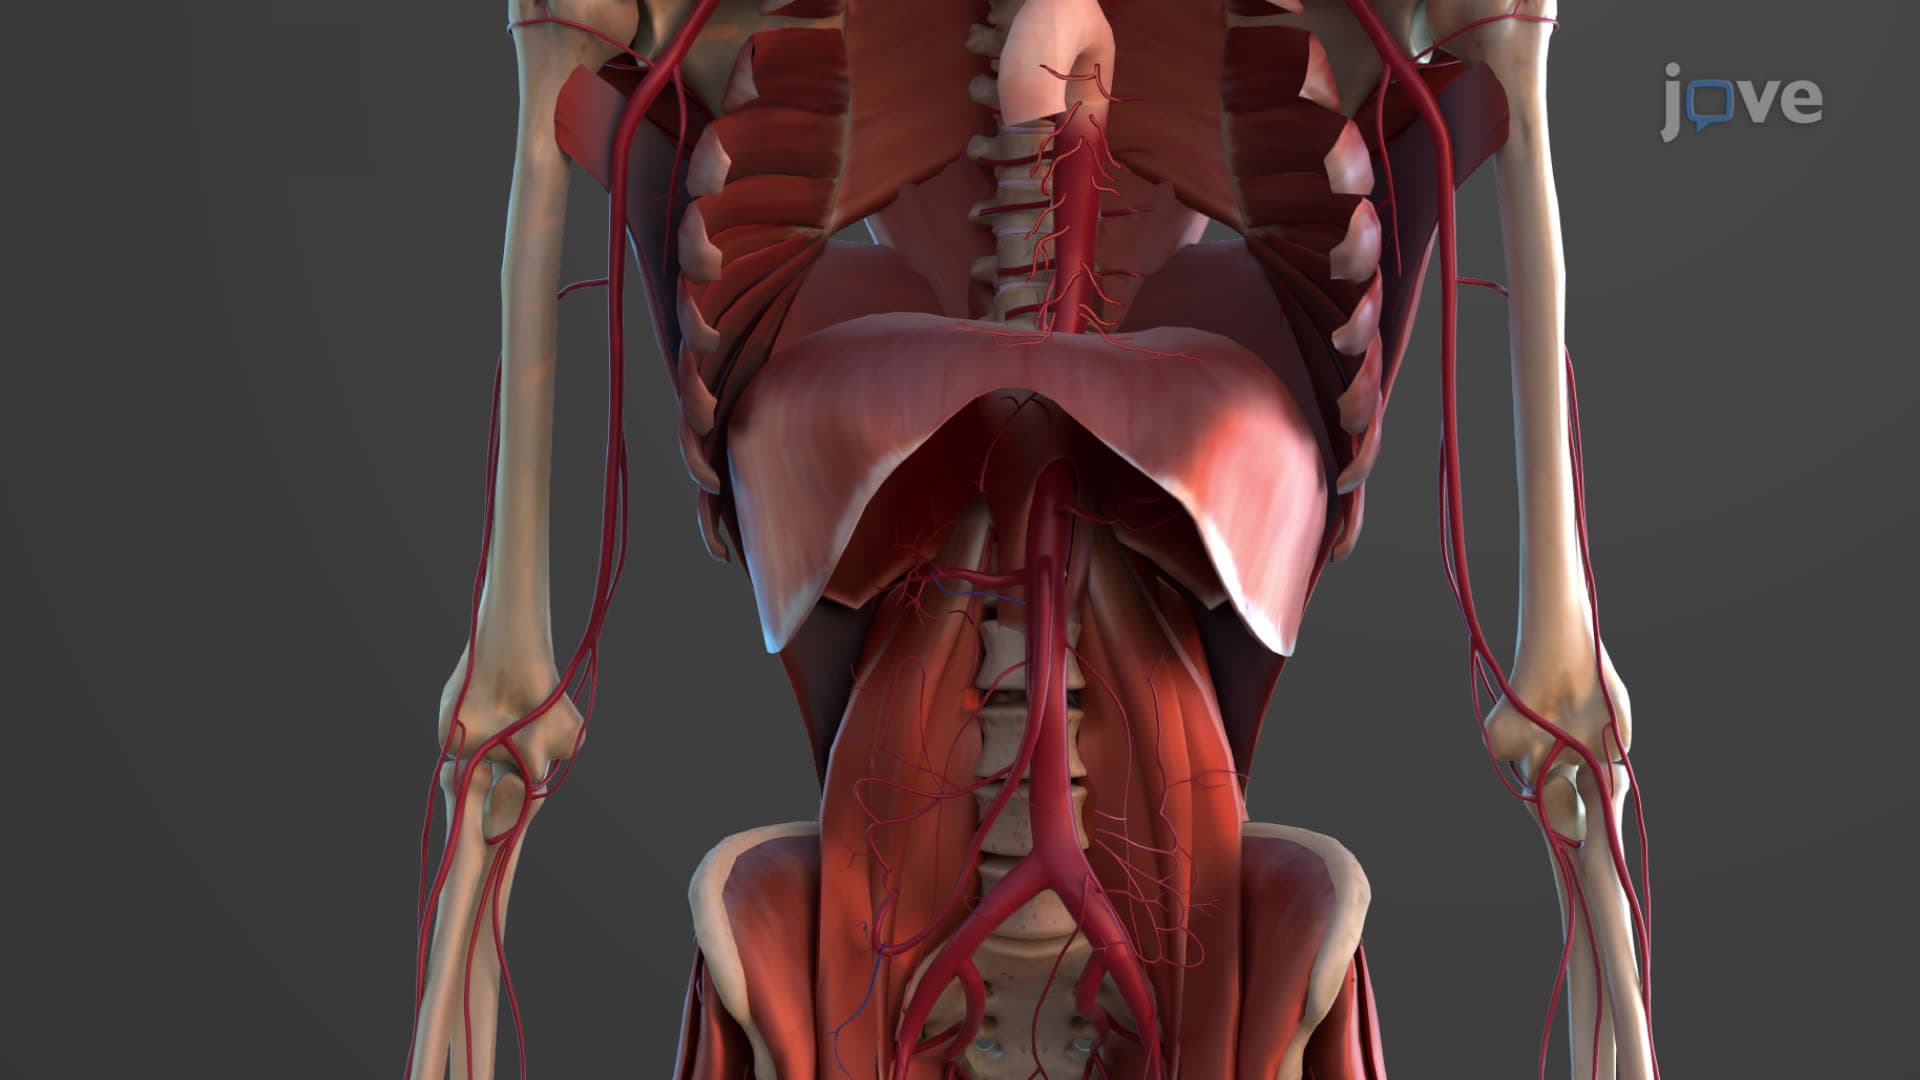
Thoracic Aorta
 01:26
Aneurysm III: Interprofessional Care
 01:28
Types of Functions III
 01:14
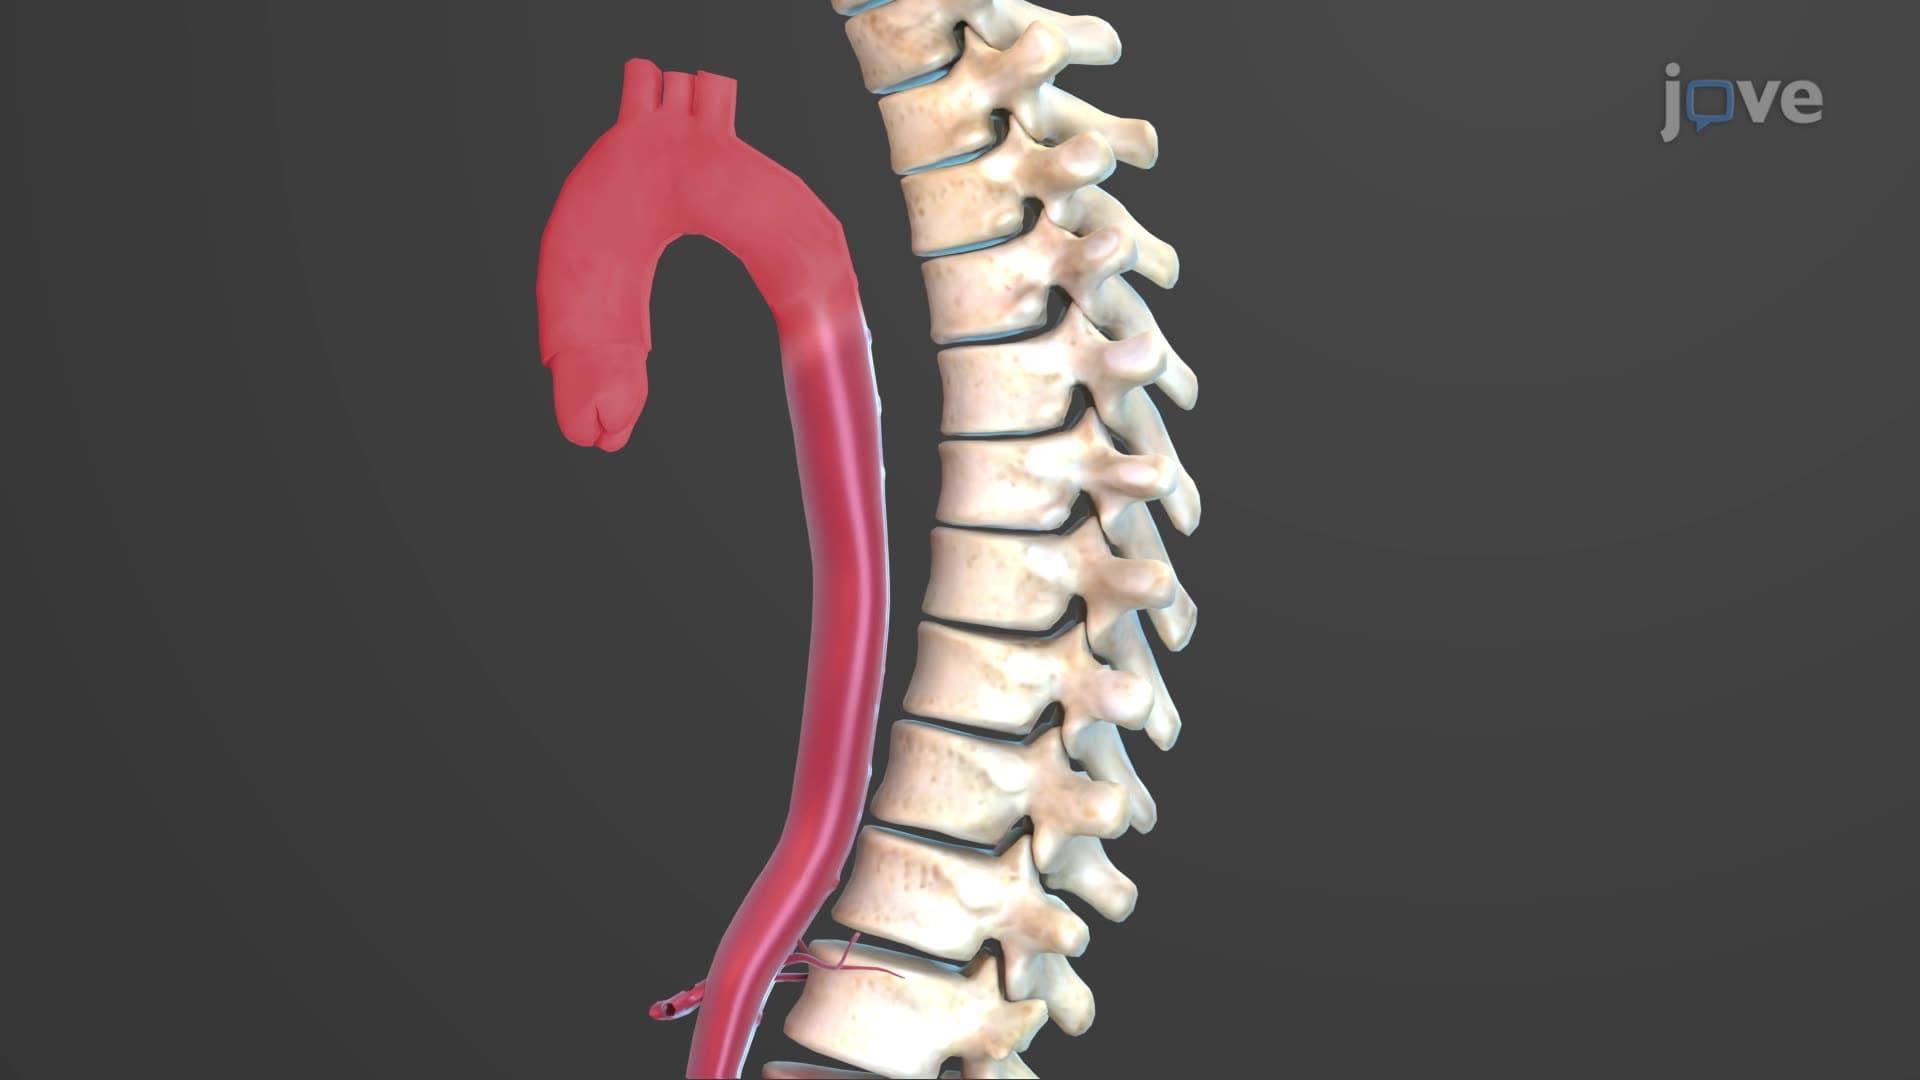
The Aorta
The average diameter of the aorta is approximately 2-3 cm, but the size can vary depending on the section of the aorta and the individual's age, sex, and body size. The aorta is...
 01:30
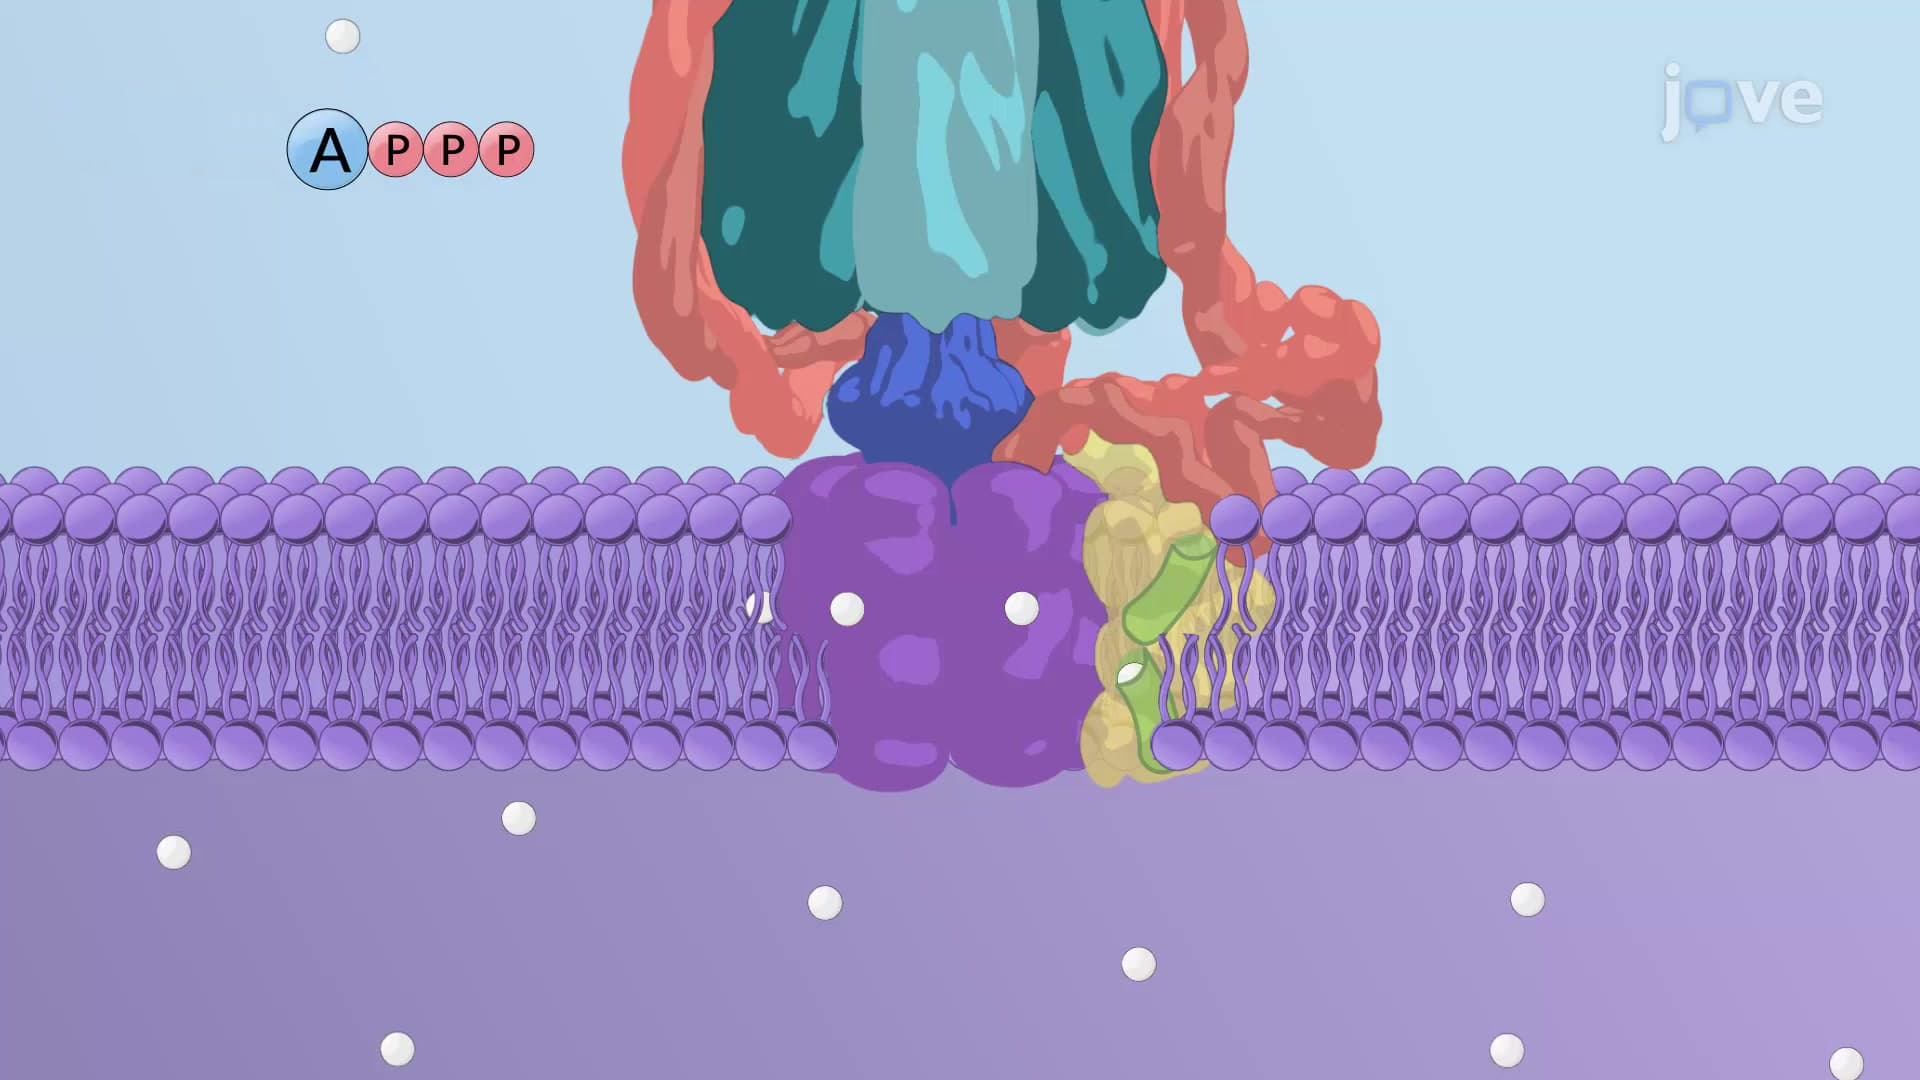
ATP Driven Pumps III: V-type Pumps
The peripheral or cytosolic V1 domain with eight subunits is involved in ATP hydrolysis. The integral or transmembrane V0 domain containing at least five subunits...
 01:26
Types of Reports III: Telephone and Verbal Reports
Here's an overview of each type:
Telephone Orders