Related Experiment Video
Updated: Feb 6, 2026


Activity-based Training on a Treadmill with Spinal Cord Injured Wistar Rats
Published on: January 16, 2019
Spinal Cord Infarction: Clinical and Radiological Features
Nishtha Yadav1, Hima Pendharkar1, Girish Baburao Kulkarni2
1Department of Neuroimaging & Interventional Radiology, National Institute of Mental Health and Neurosciences, Bangalore 560029, India.

Introduction:
Spinal cord infarction is an uncommon disease varying in its clinical presentation. This study describes the clinical and radiological presentation of spinal cord infarcts in 17 consecutive patients.
Material And Methods:
Clinical and MR imaging data of 17 patients were reviewed. Inclusion criteria were acute or subacute presentation (peak within 72 hours) and MRI showing typical signal changes on T2WI compatible with spinal cord infarct. Exclusion criteria were clinical or MRI findings suggesting other etiologies.
Results:
Clinical presentation included dissociative anesthesia, weakness of limbs, back or neck pain, and autonomic symptoms with symptom onset to peak time ranging from few minutes to 48 hours in patients with anterior spinal artery infarct (n = 16), and weakness and sensory loss in ipsilateral upper limb in patient with posterior spinal artery infarct (n = 1). One patient presented with "man-in-the-barrel syndrome (MIB)." MRI findings in anterior spinal artery infarcts included pencillike hyperintensities on T2 sagittal (n = 16, 100%) and "owl eye" appearance on T2 axial (n = 6, 37.5%) images. Diffusion restriction was noted in 8 cases and enhancement was noted in 2 cases. The posterior spinal artery infarct showed T2 hyperintensity in left posterior paramedian triangular distribution in cervical cord (C2-C7). Follow-up was available for 9 patients (period ranging from 15-41 months). Four patients had a favorable outcome who could walk independently, 1 patient could walk with support, and 2 patients were wheelchair bound. Two patients died.
Conclusion:
Spinal cord infarction is a rare but important cause of acute spinal syndrome. Typical distribution and appropriate imaging can help in timely diagnosis.
Insights
Spinal cord infarction is a rare condition causing acute spinal syndromes. This study details clinical and MRI findings in 17 patients, aiding in timely diagnosis of spinal cord infarcts.
Area of Science:
- Neurology
- Radiology
- Vascular Medicine
Background:
- Spinal cord infarction is an uncommon neurological condition with variable clinical presentations.
- This study focuses on the clinical and radiological characteristics of spinal cord infarcts.
Purpose of the Study:
- To describe the clinical and radiological presentation of spinal cord infarcts.
- To identify key diagnostic features on MRI for spinal cord infarction.
Main Methods:
- Review of clinical and MRI data from 17 consecutive patients with spinal cord infarct.
- Inclusion criteria: acute/subacute onset (peak within 72 hours) and MRI findings consistent with spinal cord infarct.
- Exclusion criteria: alternative etiologies for clinical or MRI findings.
Main Results:
- Anterior spinal artery infarcts (n=16) presented with symptoms like dissociative anesthesia, limb weakness, and autonomic dysfunction.
- Posterior spinal artery infarct (n=1) showed ipsilateral upper limb weakness and sensory loss.
- MRI revealed characteristic signal changes, including "pencillike" hyperintensities on sagittal T2WI and "owl eye" appearance on axial T2WI for anterior infarcts.
Conclusions:
- Spinal cord infarction is a rare but significant cause of acute spinal cord syndromes.
- Characteristic imaging findings on MRI, particularly T2WI signal changes, are crucial for diagnosis.
- Timely diagnosis of spinal cord infarcts can be achieved with typical imaging patterns and clinical correlation.

Related Concept Videos
 01:26
Spinal Cord
 01:54
The Spinal Cord
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:10
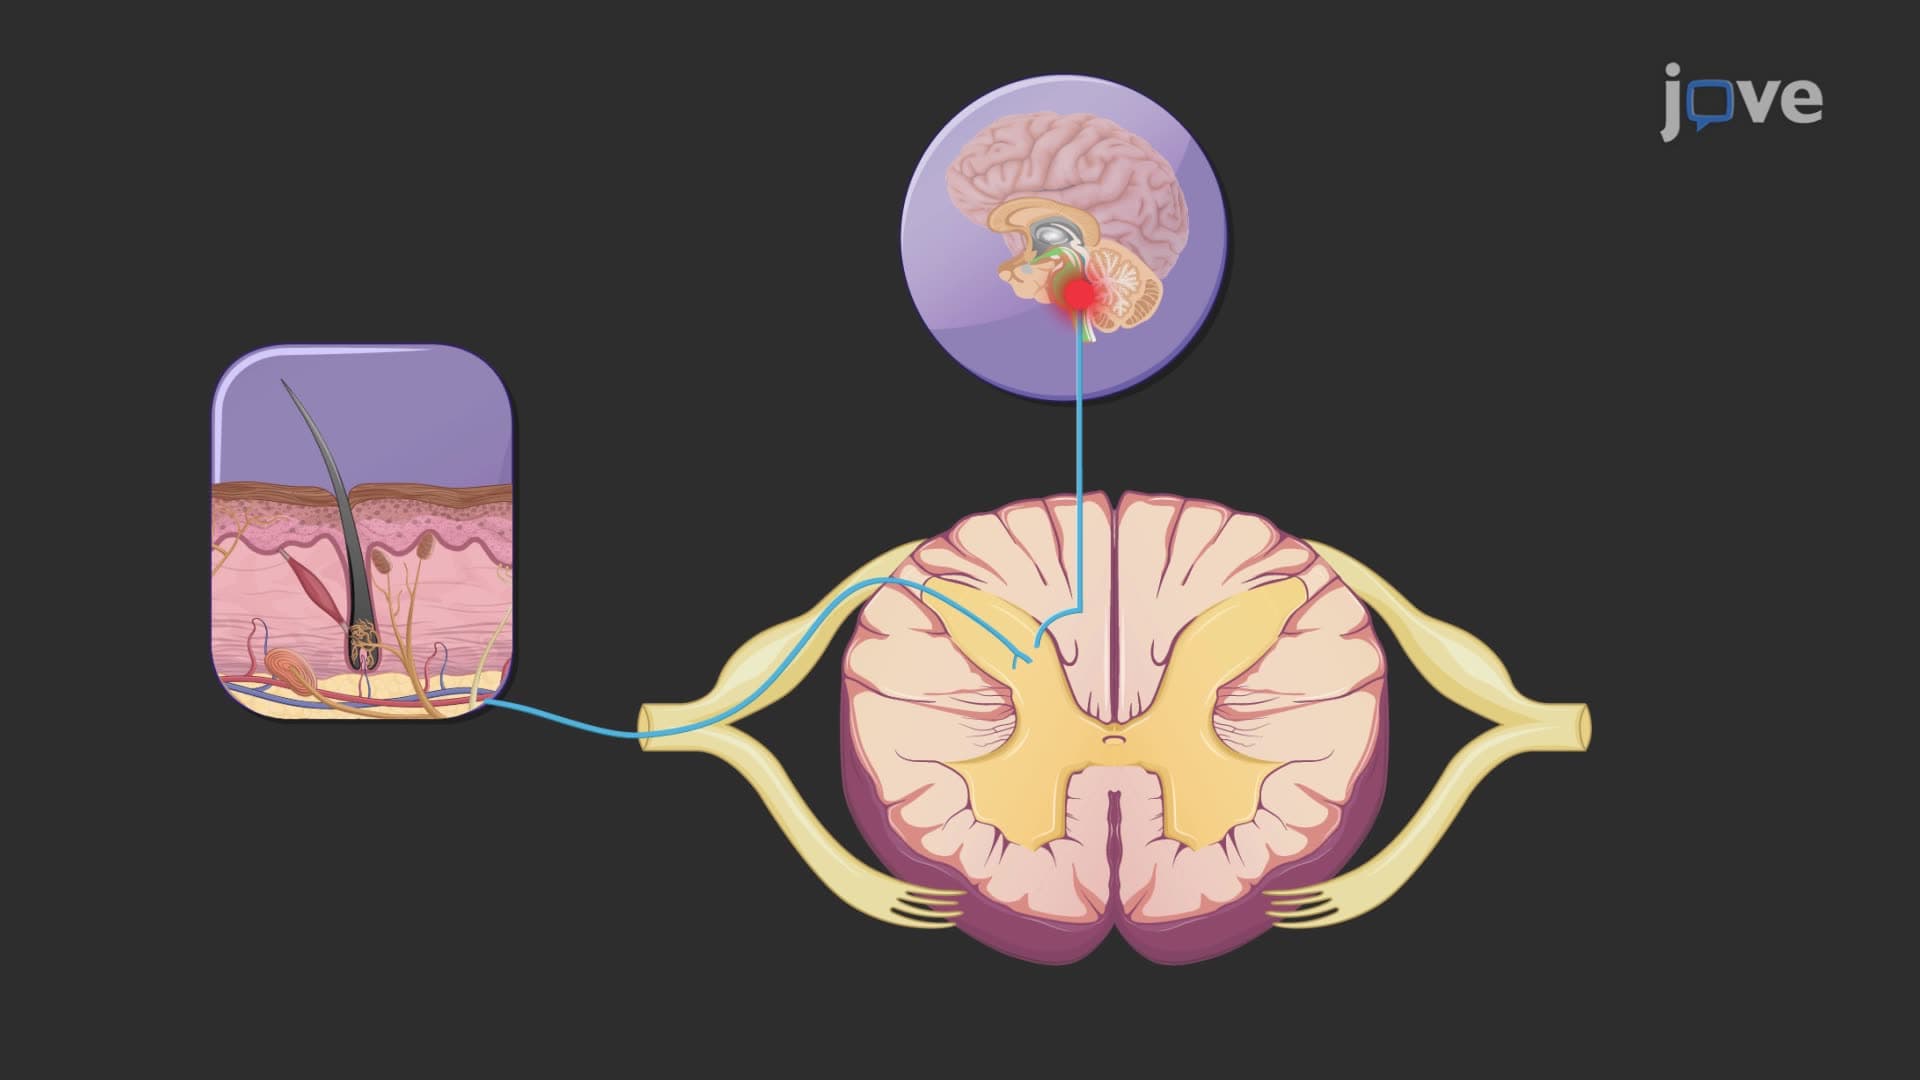
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis