Related Experiment Video
Updated: Feb 6, 2026
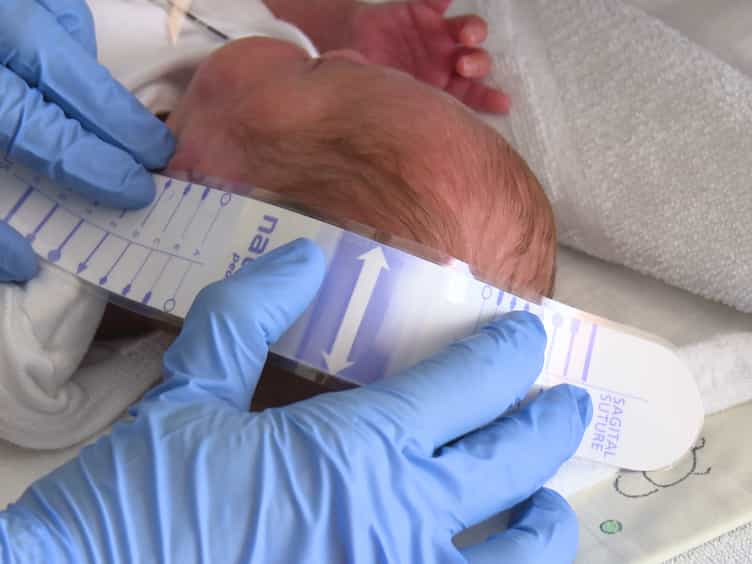
Application of an Amplitude-integrated EEG Monitor Cerebral Function Monitor to Neonates
Published on: September 6, 2017
The temporal effect of Category II fetal monitoring on neonatal outcomes
Tal Weissbach1, Ishai Heusler1, Michal Ovadia1
1Department of Obstetrics and Gynecology, Meir Medical Center, Kfar Saba, Israel(1).

Objective:
To correlate the duration of Category II cardiotocograms (CTG) with adverse neonatal outcomes associated with perinatal asphyxia and determine the duration before fetal compromise.
Study Design:
This retrospective, observational study used electronic medical record data from a cohort of 271 patients, delivered by C-section due to non-reassuring fetal heart rate, at a tertiary medical center, from 2015 through 2017. Duration of Category II CTG, variability, tachycardia and deceleration frequency were analyzed and correlated to immediate postnatal outcomes. including cord pH ≤ 7, cord base excess >12, 1- and 5-min Apgar scores ≤7, need for ventilation, need for chest compressions, NICU admission, hypoglycemia and convulsions. Intrapartum fever and meconium stained amniotic fluid were correlated to the same outcomes. Categorical and continuous variables were analyzed using chi-square and t-tests, respectively. P < 0.05 was considered significant.
Results:
The mean duration of Category II CTG was 146 min (range 17-553). Longer duration did not result in increased rates of adverse neonatal outcomes. In contrast, reduced fetal heart rate (FHR) variability, fetal tachycardia and intrapartum fever did show increased rates of adverse neonatal outcomes, as follows: patients exhibiting reduced vs. normal (FHR) variability had 12.9% vs. 1.4% cord pH ≤ 7, P = 0.006 and 12.5% vs. 1.3% cord BE > 12, P = 0.004: patients with fetal tachycardia vs. normal baseline FHR exhibited 48% vs. 17.9% 1-minute Apgar score ≤7, P = 0.0004; 8% vs. 0.8% 5-minute Apgar score ≤7, P = 0.04; and 48% vs. 18.7% ventilation support, P < 0.001; patients with intrapartum fever vs. normal temperature, cord BE > 12 was seen in 9.7% vs. 1.7%, P = 0.035; 1-minute Apgar score was ≤7 in 35.5% vs. 18.7%, P = 0.03; 5-minute Apgar score ≤7 in 9.7% vs. 0.4%, P = 0.005; need for ventilation in 35.5% vs. 19.6%, P = 0.042; need for chest compressions in 6.45% vs. none, P = 0.013; and NICU admission in 12.9% vs. 2.5%, P = 0.018.
Conclusions:
Our results suggest that the duration of Category II CTG alone does not appear to predict perinatal asphyxia. Parameters associated with perinatal asphyxia are reduced FHR variability, fetal tachycardia and intrapartum fever. Therefore, when contemplating intervention during labor to avoid fetal asphyxia, these parameters should be strongly considered.
More Related Videos

Related Concept Videos
 01:30
Categories of Equilibrium
One of the categories of equilibrium is collinear equilibrium, which involves forces acting along a straight line. This type of equilibrium requires only one force equation in the direction of the forces, as the other equations are...
 01:25
Drug Classes and Categories
 02:24
Predicting Reaction Outcomes
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care...