Related Experiment Video
Updated: Feb 6, 2026
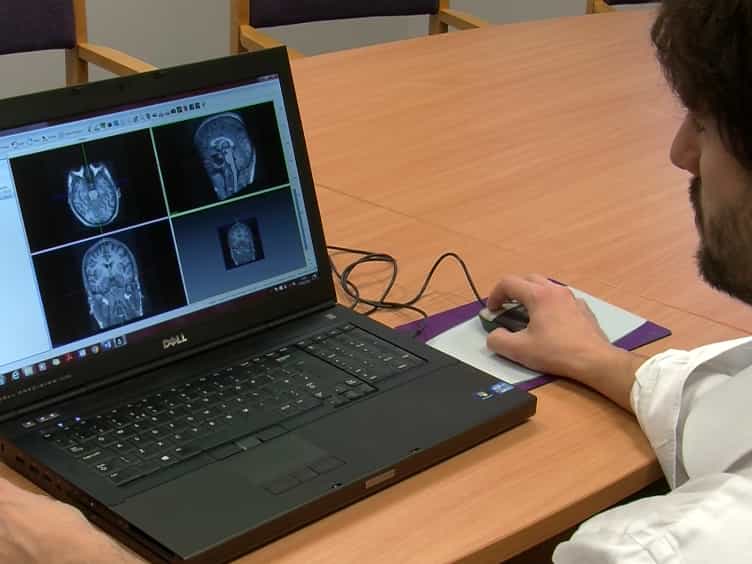

A Pipeline for 3D Multimodality Image Integration and Computer-assisted Planning in Epilepsy Surgery
Published on: May 20, 2016
A 6-month prospective randomized controlled trial of remotely delivered group format epilepsy self-management versus
Martha Sajatovic1,2, Kari Colon-Zimmermann1,2, Mustafa Kahriman3
1Department of Neurology, Neurological & Behavioral Outcomes Center, Cleveland, Ohio.

Objective:
Despite advances in care, many people with epilepsy have negative health events (NHEs) such as accidents, emergency department visits, and poor quality of life. "Self-management for people with epilepsy and a history of negative health events" (SMART) is a novel group format epilepsy self-management intervention. A community participatory approach informed the refinement of SMART, which was then tested in a 6-month randomized controlled trial of SMART (n = 60) versus waitlist control (WL, n = 60).
Methods:
Participants were adults aged ≥18 years with epilepsy and an NHE within the past 6 months (seizure, accident, self-harm attempt, emergency department visit, or hospitalization). Assessments were conducted at screening, baseline, 10 weeks, and 24 weeks (6 months). Primary outcome was 6-month change in total NHE count. Additional outcomes included depression on the nine-item Patient Health Questionnaire and Montgomery-Asberg Depression Rating Scale, quality of life on the 10-item Quality of Life in Epilepsy, functioning on the 36-item Short-Form Health Survey, and seizure severity on the Liverpool Seizure Severity Scale.
Results:
Mean age was 41.3 years (SD = 11.82), 69.9% were African American, 74.2% were unemployed, and 87.4% had an annual income < US$25 000; 57.5% had a seizure within 30 days of enrollment. Most NHEs were seizures. Six-month study attrition was 14.2% overall and similar between arms. Individuals randomized to SMART had greater reduction in total median NHEs from baseline to 6 months compared to WL (P = 0.04). SMART was also associated with improved nine-item Patient Health Questionnaire (P = 0.032), Montgomery-Asberg Depression Rating Scale (P = 0.002), 10-item Quality of Life in Epilepsy (P < 0.001), and 36-item Short-Form Health Survey (P = 0.015 physical health, P = 0.003 mental health) versus WL. There was no difference in seizure severity.
Significance:
SMART is associated with reduced health complications and improved mood, quality of life, and health functioning in high-risk people with epilepsy. Additional efforts are needed to investigate potential for scale-up.
Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:16
Precipitate Formation and Particle Size Control
The obtained precipitate should be either a pure substance of known composition or easily converted to one by a simple process, such as ignition or drying. In addition, the precipitate should be insoluble and easily filterable. In general, filterability...
 02:33
Combinatorial Gene Control
The expression of more than 30,000 genes is controlled by approximately 2000-3000 transcription factors. This is possible because a single transcription factor can recognize more than one regulatory sequence. The specificity in gene...
 01:21
Control System Problem
When forming a closed-loop system, issues can arise if the poles cross into the unstable region, leading to potential...
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:10
Control Systems
At the heart...