Related Experiment Video
Updated: Feb 6, 2026
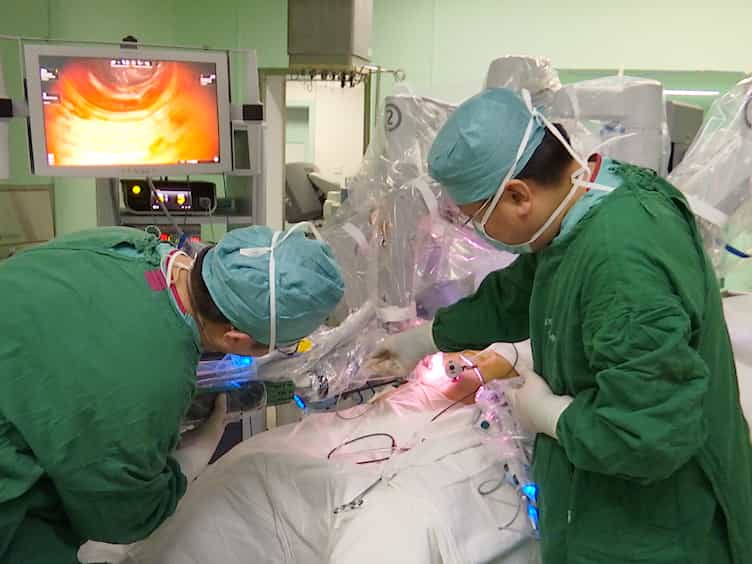
Application of End-to-end Anastomosis in Robotic Central Pancreatectomy
Published on: June 2, 2018
From Laparoscopic Right Colectomy with Extracorporeal Anastomosis to Robot-Assisted Intracorporeal Anastomosis to
Giovanni Scotton1,2, Tania Contardo1, Antonio Zerbinati1
11 Department of Surgery, Regional Specialized Center of Videolaparoscopic Robotic Surgery , Hospital of Camposampiero, Padua, Italy .

Background:
Intracorporeal anastomosis (IA) in right colectomies shows many advantages over extracorporeal anastomosis (EA). Many difficulties encountered in laparoscopic IA can be overcome with hybrid robot-assisted IA or recently with totally robotic procedures. In the literature, few works have been published comparing laparoscopic, hybrid, and totally robotic right colectomies. The aim of this study is to retrospectively analyze the improvements brought on by the evolution of robotic surgery at our specialized center.
Materials And Methods:
Two hundred six (hybrid and totally) robotic right colectomies (RRCs) with IA were compared with 160 laparoscopic right colectomies (LRCs) with EA. A separate analysis carried out by the robotic group compared 30 totally robotic right colectomies (TRRCs) with 176 hybrid robot-assisted right colectomies (HRRCs). Demographics, pathological features, operative details, and postoperative outcomes were retrospectively analyzed from a prospectively maintained database.
Results:
The groups were comparable with respect to demographics and tumor staging. When compared with LRC, RRC showed shorter time to first flatus (P < .001), stools (P < .001), solid diet (P < .001), and discharge (P < .001). The number of lymph nodes harvested was 23.13 ± 11.2 in RRC versus 20.5 ± 11.2 in LRC (P = .031). Operative time was longer in RRC (253.0 ± 47 minutes versus 209.9 ± 64 minutes; P < .001), but conversion to open (2.4% versus 18.1%; P < .001), anastomotic leaks (0.5% versus 5%; P = .012), and bleeding (0.3% versus 4.4%; P = .024) were significantly less frequent. Subsequent analysis shows no significant increase in operative time in TRRC versus HRRC (261.0 ± 41 minutes versus 251.6 ± 47.6 minutes; P = .310). Even if not statistically significant, TRRC showed faster bowel function recovery and tolerance to solid diet.
Conclusions:
We confirmed the clinical advantages of RRC with IA over LRC with EA in postoperative recovery outcomes and complication rate. Furthermore, our preliminary analysis in a cohort of 30 TRRC shows promising results.
Related Concept Videos
 02:55
The Evidence for Evolution
 01:54
Convergent Evolution
 01:24
Eukaryotic Evolution
Contrary to the endosymbiont theory, the eukaryote-first hypothesis proposes that the simpler prokaryotic and...
 02:31
Synteny and Evolution
Around 80 million years ago, the human and mice lineages diverged from the common ancestor. During the course of evolution, the ancestral...
 01:25
Abdominal Aorta
The celiac trunk, a singular artery, divides into the left gastric artery, which...
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration