The risk-treatment paradox in non-ST-elevation myocardial infarction patients according to their estimated GRACE risk
Related Experiment Video
Updated: Feb 6, 2026

Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Aet Saar1, Toomas Marandi2, Tiia Ainla1
1Heart Clinic, University of Tartu, 1a L. Puusepa Str., 50406 Tartu, Estonia; Centre of Cardiology, North Estonia Medical Centre, 19 J. Sütiste Str., 13419 Tallinn, Estonia.

Background:
The purpose was to describe the treatment and outcomes of non-ST-elevation myocardial infarction (NSTEMI) in Estonia according to patients' estimated mortality risk by the Global Registry of Acute Coronary Events (GRACE) score and investigate if inequalities in treatment had an impact on prognosis.
Methods:
We performed a linkage between Estonian Myocardial Infarction Registry, Population Registry and Estonian Health Insurance Fund. All NSTEMI patients 2012-2014 were stratified into low (<4%), intermediate (4-12%), or high (>12%) mortality risk according to GRACE. All-cause mortality and composite endpoint of death, recurrent myocardial infarction, stroke or unplanned revascularization were compared between optimally - defined as concomitant in-hospital use of medicines from recommended groups and coronary angiography - and suboptimally managed patients, using the Cox regression.
Results:
Out of 3803 NSTEMI patients (median age 73 years, 44% women) 20% were classified into low, 35% into intermediate and 45% into high risk category. In these groups, respectively, 62%, 46% and 23% of patients received optimal in-hospital management. Over the mean follow-up of 2.4 years the association between suboptimal in-hospital management and outcomes was the following: in the low risk group mortality hazard ratio (HR) 1.6 (95% confidence interval 0.8-3.2), composite endpoint HR 1.2 (0.8-1.8); in the intermediate risk group mortality HR 2.4 (1.7-3.3), composite endpoint HR 1.8 (1.4-2.3); and in the high risk group mortality HR 2.2 (1.8-2.8), composite endpoint HR 1.6 (1.3-2.0).
Conclusions:
Higher risk NSTEMI patients received less guideline-recommended in-hospital management, which was associated with a worse prognosis.
Related Concept Videos
 01:12
Relative Risk
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:17
Design Example: Analyzing Capacity Contours for Flood Risk Assessment
 03:12
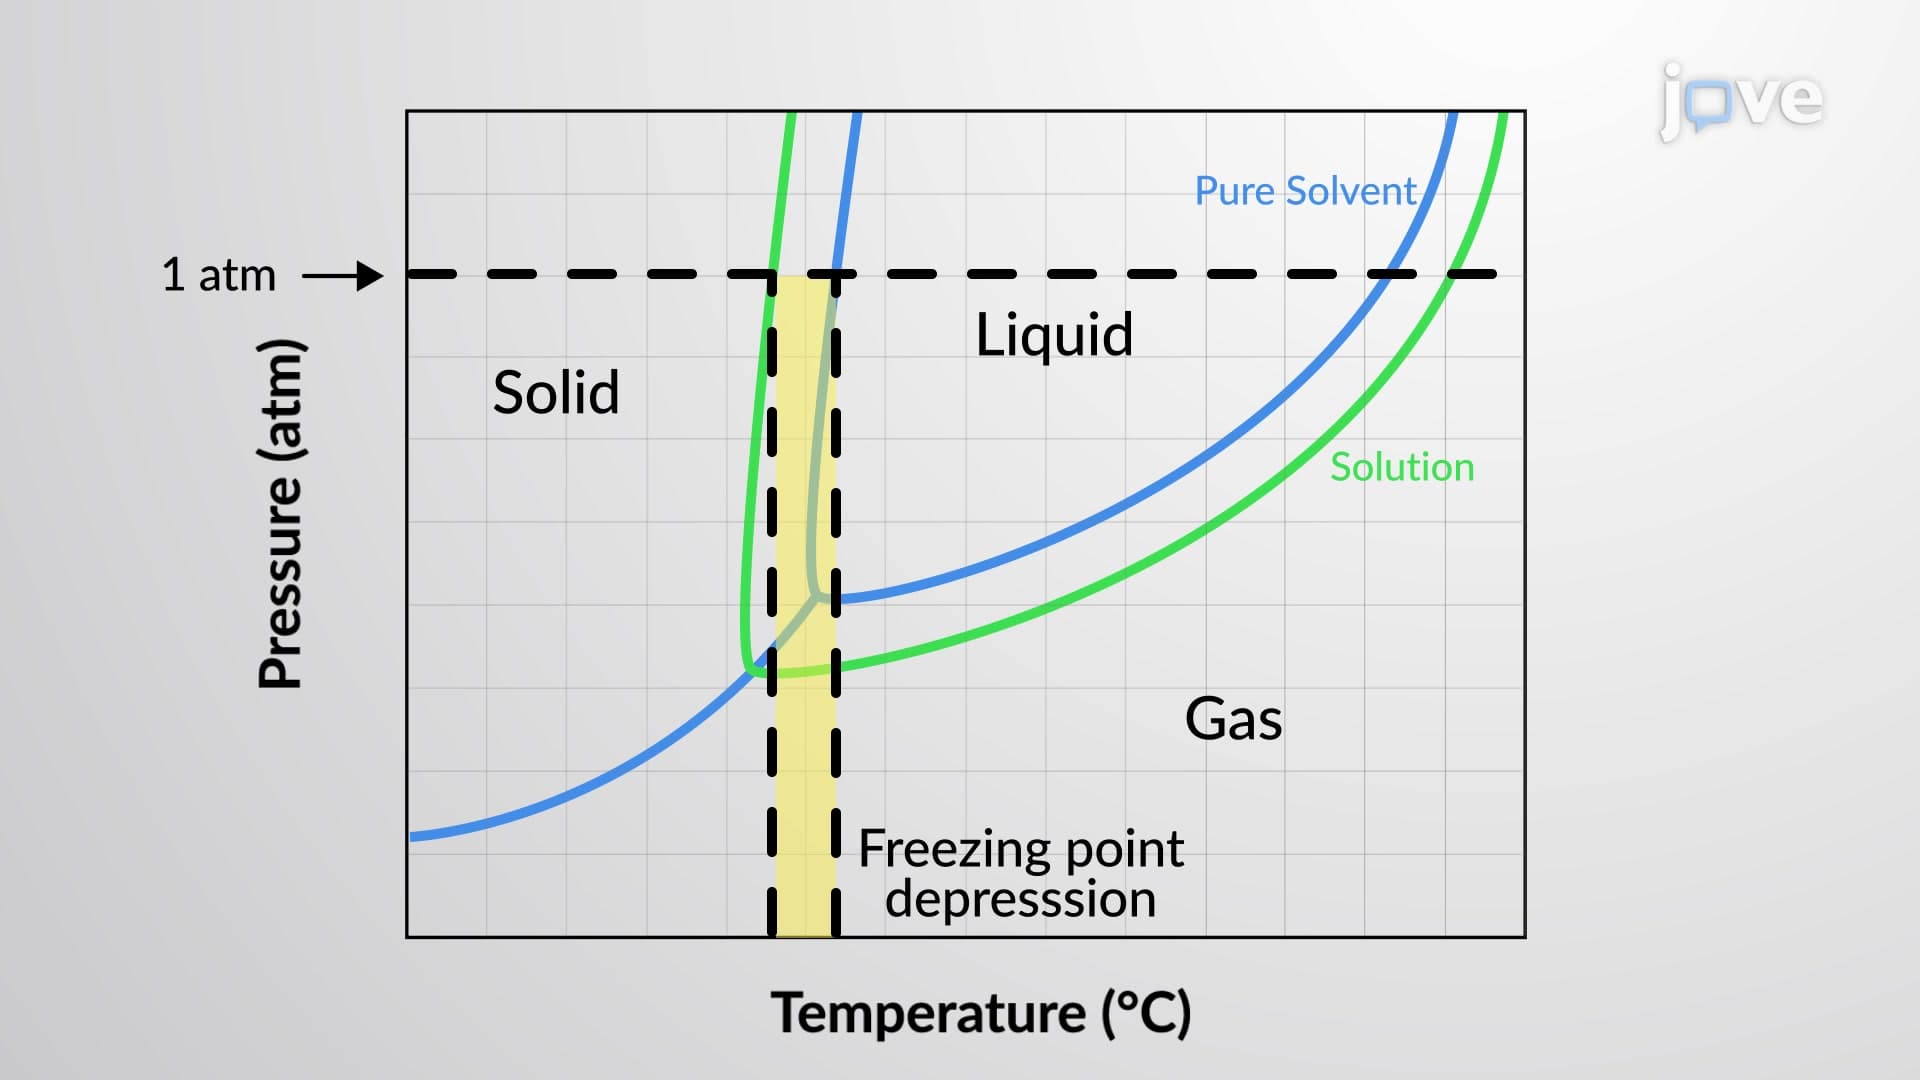
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:06
What are Estimates?
The estimate for the mean of a sample is denoted by ͞x, whereas the mean of the population is designated as μ. Further, parameters such...
 01:20
Elevation of Intermediate Points on Vertical Curves