Modified cranial closing wedge ostectomy in 25 dogs
Related Experiment Video
Updated: Feb 6, 2026

Intravital Microscopy of the Mouse Brain Microcirculation using a Closed Cranial Window
Published on: November 18, 2010
Jeffrey P Christ1, Jonathan R Anderson1, Ada O Youk2
1Pittsburgh Veterinary Specialty and Emergency Center, Pittsburgh, Pennsylvania.

Objective:
To describe the planning of a modified cranial closing wedge ostectomy (mCCWO) and determine the accuracy of execution without intraoperative jigs or alignment guides.
Study Design:
Retrospective study.
Animals:
Twenty-five client-owned dogs (32 stifles) with cranial cruciate ligament disease.
Methods:
Medical records of dogs treated with mCCWO between July 2014 and December 2016 were reviewed. Preoperative, postoperative, and 8-week-recheck radiographs were reviewed to measure changes in the conformation of the proximal tibia. The accuracy of execution was assessed by comparing planned and actual postoperative tibial plateau angle (TPA) and the lengths of bone contact along osteotomy lines. Radiographic healing and clinical outcome were subjectively evaluated 8 weeks after surgery.
Results:
Preoperative planning of mCCWO decreased the cranial wedge length by a mean of 23% compared with the traditional CCWO planning. Mean TPA decreased from 40.69 ° (range 28-63) to 6.94 ° (range 2-20) after surgery (P < .001). Mean tibial length decreased by 0.5 mm (±0.16, P = .003), from 138 mm (range 65-267) to 137.5 mm (range 65-265) after mCCWO. The tibial long axis (TLA) shifted by a mean of 3.47 ° (range 0-10). Planned and actual postoperative TPA differed by -0.66 ° (±0.47, P = .034). The proximal and distal apposing osteotomies differed in length by 1.81 mm (±0.35). No bone healing complications or implant failures were diagnosed, and all dogs returned to subjectively satisfactory function by 8 weeks after surgery.
Conclusion:
The preoperative planning and methods of execution of the mCCWO resulted in differences in target TPA and postoperative TPA, differences in lengths of proximal and distal osteotomies, and tibial shortening that did not appear clinically significant in this study.
Clinical Significance:
mCCWO can be planned and accurately executed without consideration of TLA shift or the intraoperative use of alignment guides or jigs.


Related Concept Videos
 01:24
Wedges
Consider using a wedge to lift a heavy slab. Here, the wedge functions by converting the applied force into a much larger force directed almost perpendicular to the initial force. This...
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:14
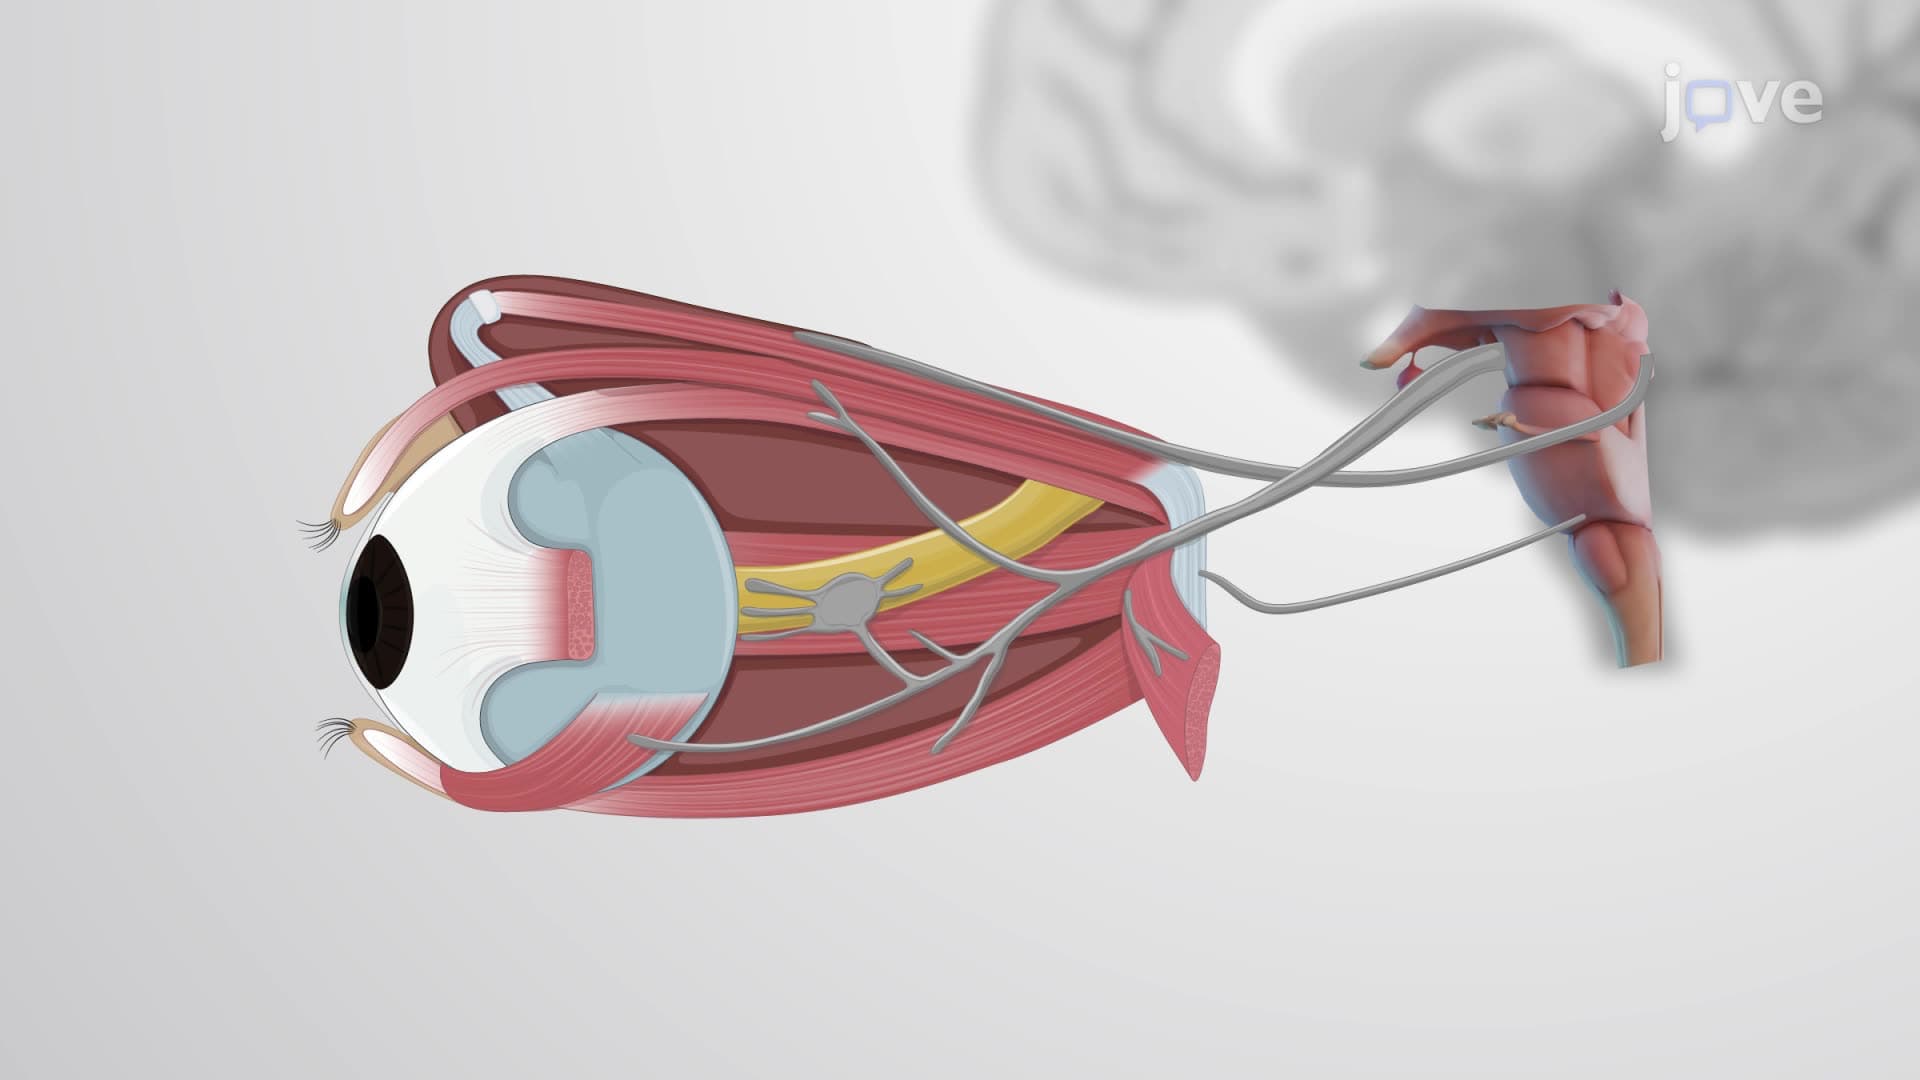
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:22
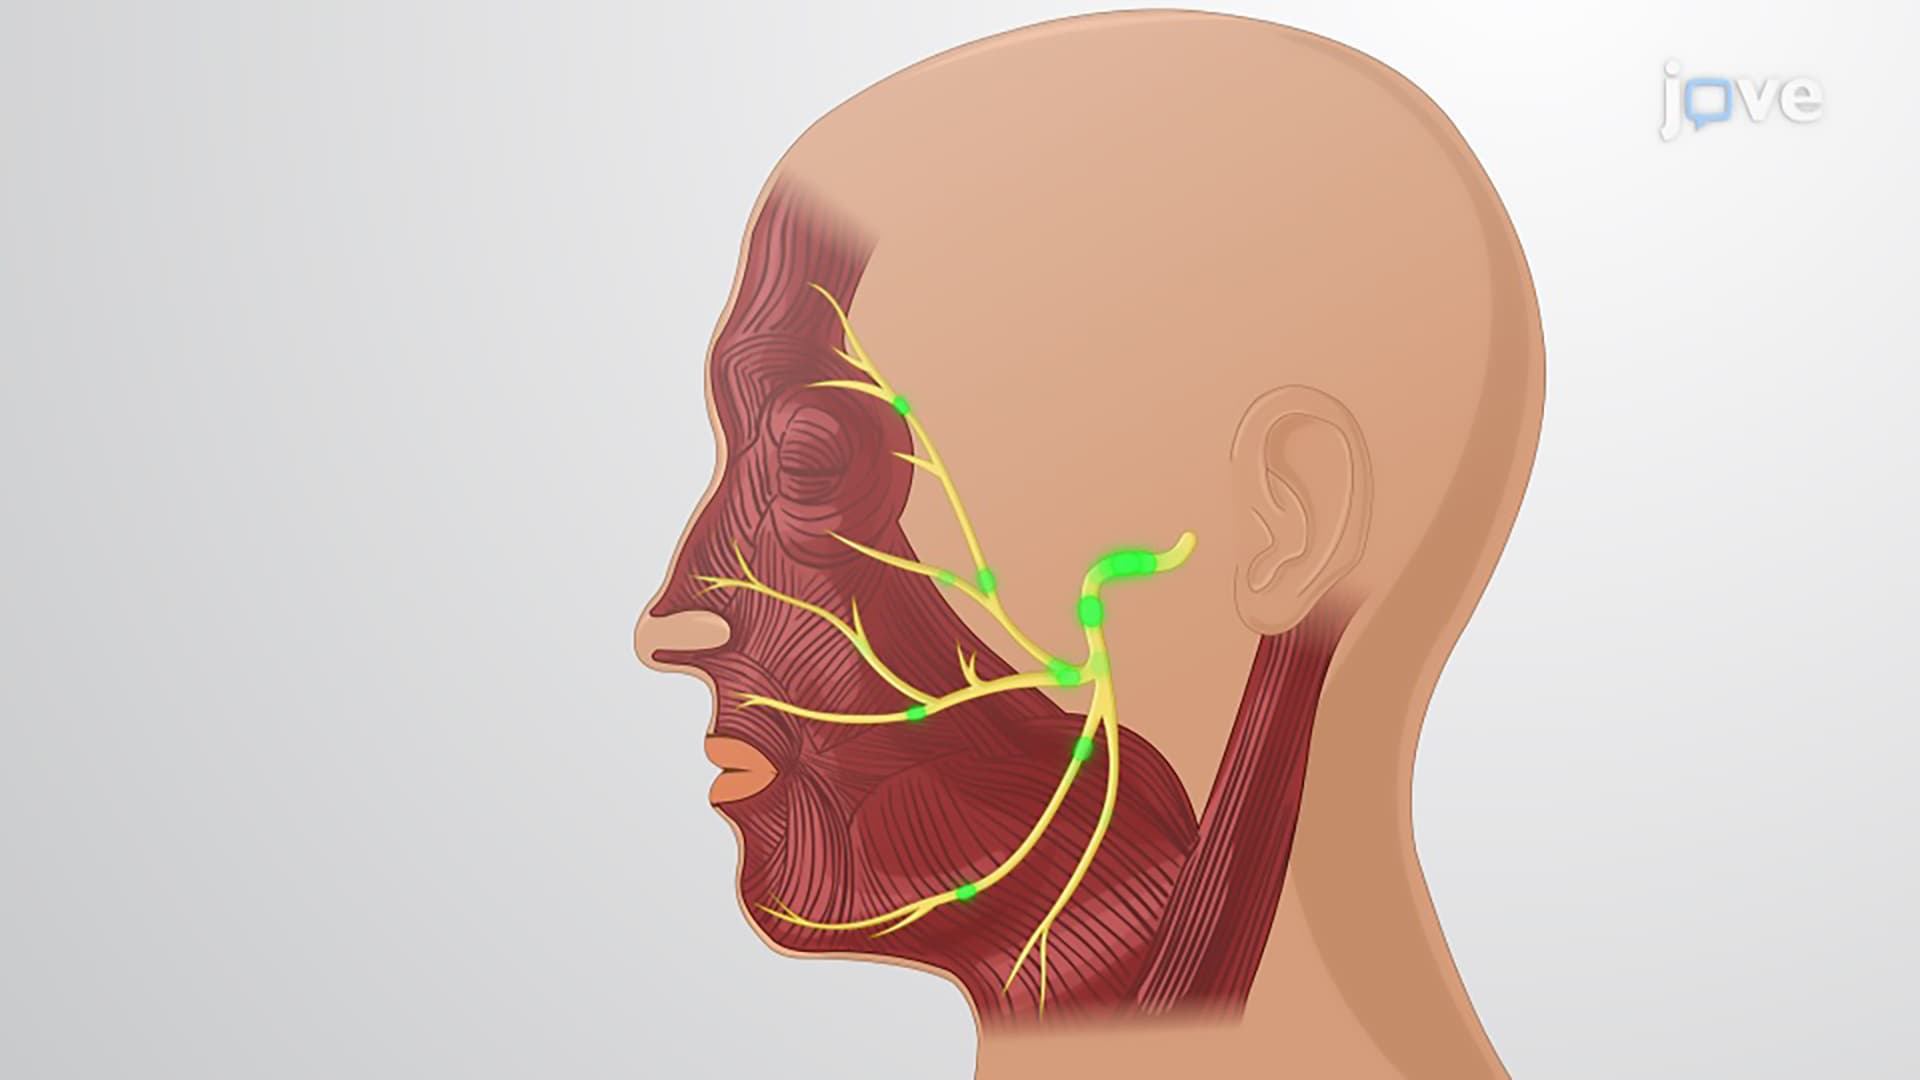
Cranial Nerves: Types Part II
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:18
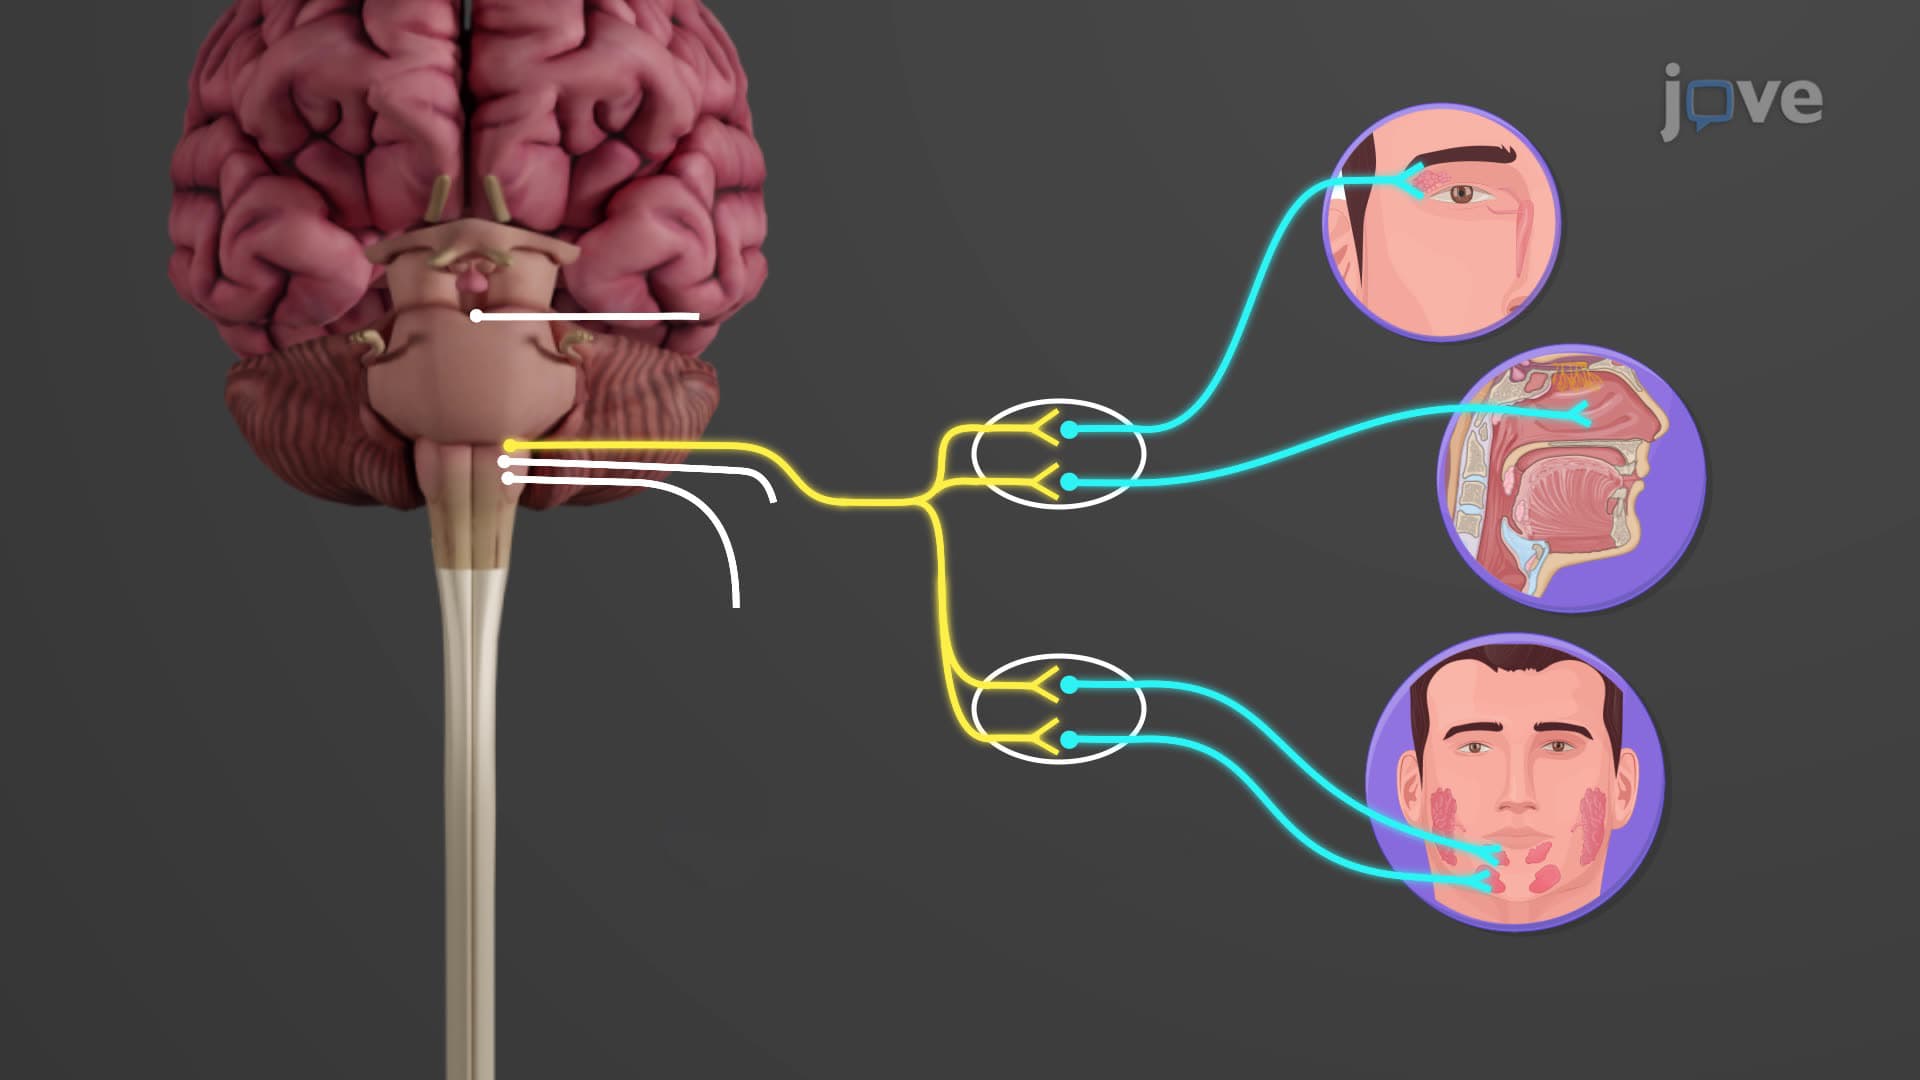
Cranial Part of Parasympathetic Division
The vagus nerve (cranial nerve X) alone accounts for approximately 75...
 01:29
Close Relationships and Culture