Related Experiment Video
Updated: Feb 6, 2026
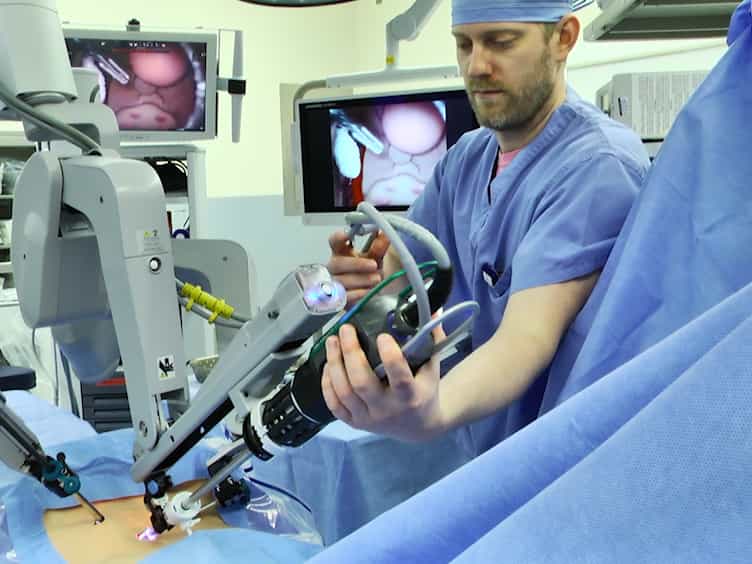

Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
[Emergencies in Plastic Surgery: Analysis of Emergency Presentation within a University Department for Plastic and
Seyed Arash Alawi1, Dennis Werner1, Sören Könneker1
1Medizinische Hochschule Hannover, Klinik für Plastische, Ästhetische, Hand- und Wiederherstellungschirurgie, Replantationszentrum Niedersachsen, Schwerbrandverletztenzentrum Niedersachsen.

Background:
Interdisciplinary emergency departments in Germany are seeing an increasing inflow of patients for several reasons. Since the number of patients in the emergency room cannot be planned, there may be a lack of capacity with prolonged waiting periods and delays. In particular, a significant amount of capacities is consumed by hand injuries. Also it is suspected for the discipline of plastic surgery that the majority of emergency presentations are unjustified. We provide a collection of data followed by an analysis of emergencies to better understand the increased number of patients with the aim of identifying possible solutions for the relief of emergency care.
Methods:
We performed a retrospective analysis of documented patient cases seen in the interdisciplinary emergency room of the Department of Plastic, Aesthetic, Hand and Reconstructive Surgery of a university hospital. Over the span of one year, we evaluated the diagnosis, waiting time and distribution of patients over 24 hours at 7 weekdays. Furthermore, we evaluated the justification of emergency presentation and the necessity of inpatient admission.
Results:
We assessed a total of 2768 patients with an average age of 40 years (median = 37 years, male 59 %/ female 41 %) within one year (2016-2017). Of 2450 patients, 69 % were legitimate emergencies, defined by severity of trauma or disease. Proportionally, the most common cause of presentation for 2768 cases was upper extremity injury with cut and saw injuries amounting to 25 % (n = 697), followed by lacerations/bite injuries with 22 % (n = 611) and burns with 17 % (n = 477). Most services were performed between 09:00 a.m. and 01:00 p.m. There were no significant differences regarding the distribution over different weekdays. In 24 % (n = 583) of these cases, the patient was hospitalised for inpatient treatment. In 45 % of cases, there was no indication for hospitalisation after treatment. The waiting time for 2450 patients averaged 2:23 h (median = 01:43 h) until treatment.
Discussion:
In face of these results it may be argued, that a majority of emergency cases could be selected through filter structures to be distributed to suitable facilities. This could cover a large proportion of the 45 % legitimate, but ambulatory emergencies. Furthermore a concentration of emergency departments should take place with a simultaneous supply of financial resources to expanding emergency departments with high patient flow.
More Related Videos
 04:05
Author Spotlight: Unveiling Prognostic Indicators in Heart Failure - The Role of Phase Angle and Bioelectrical Impedance Analysis
Published on: June 30, 2023
 07:52
Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
Related Concept Videos
 01:27
Emerging Adulthood
 00:58
Plasticity
 01:31
Plasticizers
Plasticizers function by using surface-active agents to create repulsive electrostatic forces between cement particles. This dispersion enhances the concrete's...
 01:21
Plastic Behavior
 01:14
Plastic Deformations
 01:19
Plastic Deformations