Related Experiment Video
Updated: Feb 6, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Long-term use of carvedilol in patients with ST-segment elevation myocardial infarction treated with primary
Hiroki Watanabe1, Neiko Ozasa1, Takeshi Morimoto2
1Department of Cardiovascular Medicine, Graduate School of Medicine, Kyoto University, Kyoto, Japan.

Insights
Long-term carvedilol therapy did not improve outcomes for ST-segment elevation myocardial infarction (STEMI) patients without heart failure after primary percutaneous coronary intervention (PCI). This randomized trial found no significant differences in major adverse events between groups.
Area of Science:
- Cardiology
- Clinical Trials
- Pharmacotherapy
Background:
- Current guidelines recommend long-term oral beta-blockers for ST-segment elevation myocardial infarction (STEMI).
- However, randomized trials have not evaluated this therapy in uncomplicated STEMI patients without heart failure after primary percutaneous coronary intervention (PCI).
Purpose of the Study:
- To evaluate the efficacy of long-term oral carvedilol therapy in STEMI patients who underwent successful primary PCI.
- To assess the impact of carvedilol on major adverse cardiovascular events and left ventricular ejection fraction.
Main Methods:
- A multi-center, open-label, randomized controlled trial (CAPITAL-RCT) involving 801 STEMI patients with LVEF ≥40% post-primary PCI.
- Patients were assigned to receive carvedilol or no beta-blocker within 7 days of PCI.
- The primary endpoint was a composite of all-cause death, myocardial infarction, heart failure hospitalization, and acute coronary syndrome hospitalization over 3 years.
Main Results:
- No significant difference in the 3-year cumulative incidence of the primary endpoint between the carvedilol and no beta-blocker groups (6.8% vs. 7.9%, P=0.20).
- No significant difference in the 3-year incidence of coronary revascularization (20.3% vs. 17.7%, P=0.65).
- No significant difference in left ventricular ejection fraction at 1-year between the groups (60.9% vs. 59.6%, P=0.06).
Conclusions:
- Long-term carvedilol therapy, added to contemporary evidence-based medications, did not demonstrate additional benefit in selected STEMI patients treated with primary PCI.
- The findings suggest that beta-blocker therapy may not be necessary for all STEMI patients post-PCI if they have preserved left ventricular function and no heart failure.
Background:
Despite its recommendation by the current guidelines, the role of long-term oral beta-blocker therapy has never been evaluated by randomized trials in uncomplicated ST-segment elevation myocardial infarction (STEMI) patients without heart failure, left ventricular dysfunction or ventricular arrhythmia who underwent primary percutaneous coronary intervention (PCI).
Methods And Results:
In a multi-center, open-label, randomized controlled trial, STEMI patients with successful primary PCI within 24 hours from the onset and with left ventricular ejection fraction (LVEF) ≥40% were randomly assigned in a 1-to-1 fashion either to the carvedilol group or to the no beta-blocker group within 7 days after primary PCI. The primary endpoint is a composite of all-cause death, myocardial infarction, hospitalization for heart failure, and hospitalization for acute coronary syndrome. Between August 2010 and May 2014, 801 patients were randomly assigned to the carvedilol group (N = 399) or the no beta-blocker group (N = 402) at 67 centers in Japan. The carvedilol dose was up-titrated from 3.4±2.1 mg at baseline to 6.3±4.3 mg at 1-year. During median follow-up of 3.9 years with 96.4% follow-up, the cumulative 3-year incidences of both the primary endpoint and any coronary revascularization were not significantly different between the carvedilol and no beta-blocker groups (6.8% and 7.9%, P = 0.20, and 20.3% and 17.7%, P = 0.65, respectively). There also was no significant difference in LVEF at 1-year between the 2 groups (60.9±8.4% and 59.6±8.8%, P = 0.06).
Conclusion:
Long-term carvedilol therapy added on the contemporary evidence-based medications did not seem beneficial in selected STEMI patients treated with primary PCI.
Trial Registration:
CAPITAL-RCT (Carvedilol Post-Intervention Long-Term Administration in Large-scale Randomized Controlled Trial) ClinicalTrials.gov.number, NCT 01155635.
More Related Videos


Related Concept Videos
 03:12
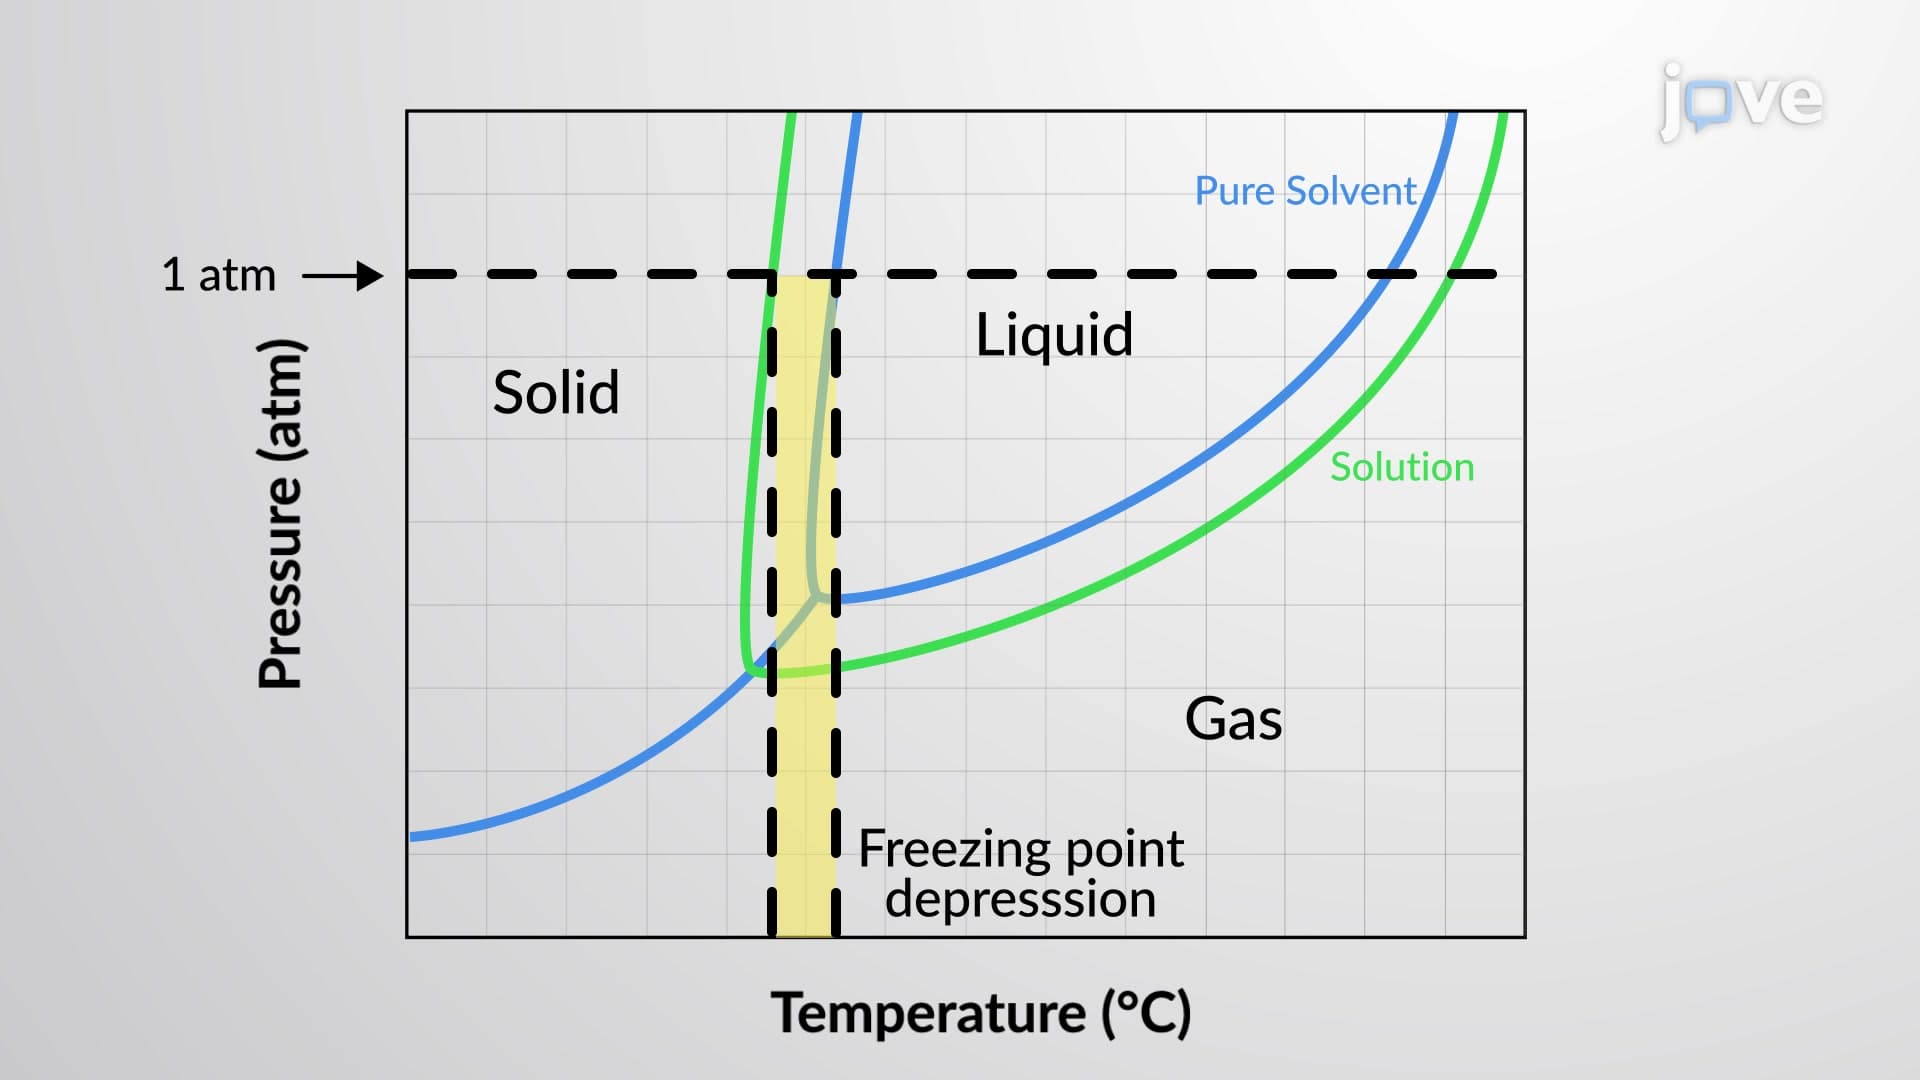
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:03
Nursing Interventions I: Taxonomy of Nursing Interventions
A nursing intervention is a treatment or action based on scientific concepts and knowledge from the nursing, behavioral, and physical sciences. Identifying and prioritizing nursing interventions based on the desired outcome...
 01:29
Nursing Interventions II: Selecting and Classifying the Nursing Interventions
 01:20
Elevation of Intermediate Points on Vertical Curves
 01:05
Long-term Depression
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...