Related Experiment Video
Updated: Feb 6, 2026
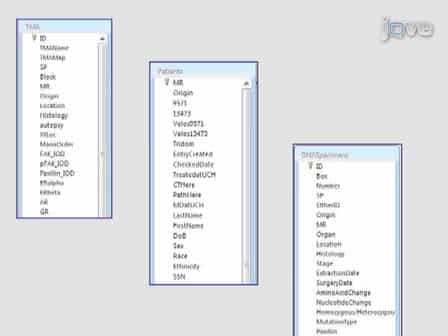

Generation of Comprehensive Thoracic Oncology Database - Tool for Translational Research
Published on: January 22, 2011
Forequarter Amputation, Thoracic Resection, and Reconstruction on Giant Ulcer Due to Locally Advanced Oncological
Elena García-Vilariño1, Enrique Salmerón-González, Alberto Pérez-García
1Elena García-Vilariño, MD, is a plastic surgeon, Plastic and Reconstructive Surgery Department, University and Polytechnic Hospital La Fe, Valencia, Spain. Enrique Salmerón-González, MD, is a plastic surgeon, Plastic and Reconstructive Surgery Department, University and Polytechnic Hospital La Fe, Valencia, Spain. Alberto Pérez-García, MD, is a plastic surgeon, Plastic and Reconstructive Surgery Department, University and Polytechnic Hospital La Fe, Valencia, Spain. Alberto Ruiz-Cases, MD, is a plastic surgeon, Plastic and Reconstructive Surgery Department, University and Polytechnic Hospital La Fe, Valencia, Spain. Eloy Condiño-Brito, MD, is a plastic surgeon, Plastic and Reconstructive Surgery Department, University and Polytechnic Hospital La Fe, Valencia, Spain. Alberto Sánchez-García, MD, is a plastic surgeon, Plastic and Reconstructive Surgery Department, University and Polytechnic Hospital La Fe, Valencia, Spain.

Abstract:
We present the case of a 67-year-old man suffering from a squamous cell carcinoma with extensive thoracic locoregional affection measuring 28 cm. After being considered inoperable at another center, he underwent an aggressive tumor resection and coverage with a free latissimus dorsi flap as a palliative reconstructive procedure that allowed for a considerable improvement of his quality of life.
Related Concept Videos
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors