Related Experiment Video
Updated: Jul 29, 2026


Esophageal Heat Transfer for Patient Temperature Control and Targeted Temperature Management
Published on: November 21, 2017
Effect of audit and feedback on physicians' intraoperative temperature management and patient outcomes: a three-arm
Sylvain Boet1,2,3, Gregory L Bryson4,5, Monica Taljaard5,6
1Department of Anesthesiology and Pain Medicine, The Ottawa Hospital, University of Ottawa, 501 Smyth Rd, Critical Care Wing 1401, Ottawa, ON, K1H 8L6, Canada. sboet@toh.ca.

Purpose:
Audit and feedback can improve physicians' practice; however, the most effective type of feedback is unknown. Inadvertent perioperative hypothermia is associated with postoperative complications and remains common despite the use of effective and safe warming devices. This study aimed to measure the impact of targeted audit and feedback on anesthesiologists' intraoperative temperature management and subsequent patient outcomes.
Methods:
This study was a three-arm cluster randomized-controlled trial. Anesthesiologists' intraoperative temperature management performance was analyzed in two phases. The first was a baseline phase with audit but no feedback for eight months, followed by an intervention phase over the next seven-month period after participants had received interventions according to their randomized group allocation of no feedback (control), benchmarked feedback, or ranked feedback. Anesthesiologists' percentage of hypothermic patients at the end of surgery (primary endpoint) and use of a warming device were compared among the groups.
Results:
Forty-five attending anesthesiologists who took care of 7,846 patients over 15 months were included. The odds of hypothermia (temperature < 36°C at the end of surgery) increased significantly from pre- to post-intervention in the control and ranked groups (control odds ratio [OR], 1.27; 95% confidence interval [CI], 1.03 to 1.56; P = 0.02; ranked OR, 1.26; 95% CI, 1.01 to 1.56; P = 0.04) but not in the benchmarked group (OR, 1.05; 95% CI, 0.87 to 1.28; P = 0.58). Between-arm differences in pre- to post-intervention changes were not significant (benchmark vs control OR, 0.83; 95% CI, 0.62 to 1.10; P = 0.19; ranked vs control OR, 0.99; 95% CI, 0.73 to 1.33, P = 0.94). No significant overall effect on intraoperative warmer use change was detected.
Conclusion:
We found no evidence to suggest that audit and feedback, using benchmarked or ranked feedback, is more effective than no feedback at all to change anesthesiologists' intraoperative temperature management performance. Feedback may need to be included in a bundle to produce its effect.
Trials Registration:
www.clinicaltrials.gov (NCT02414191). Registered 19 March 2015.
More Related Videos

Related Concept Videos
 01:28
Factors Affecting Body Temperature
Factors may include:
 01:14
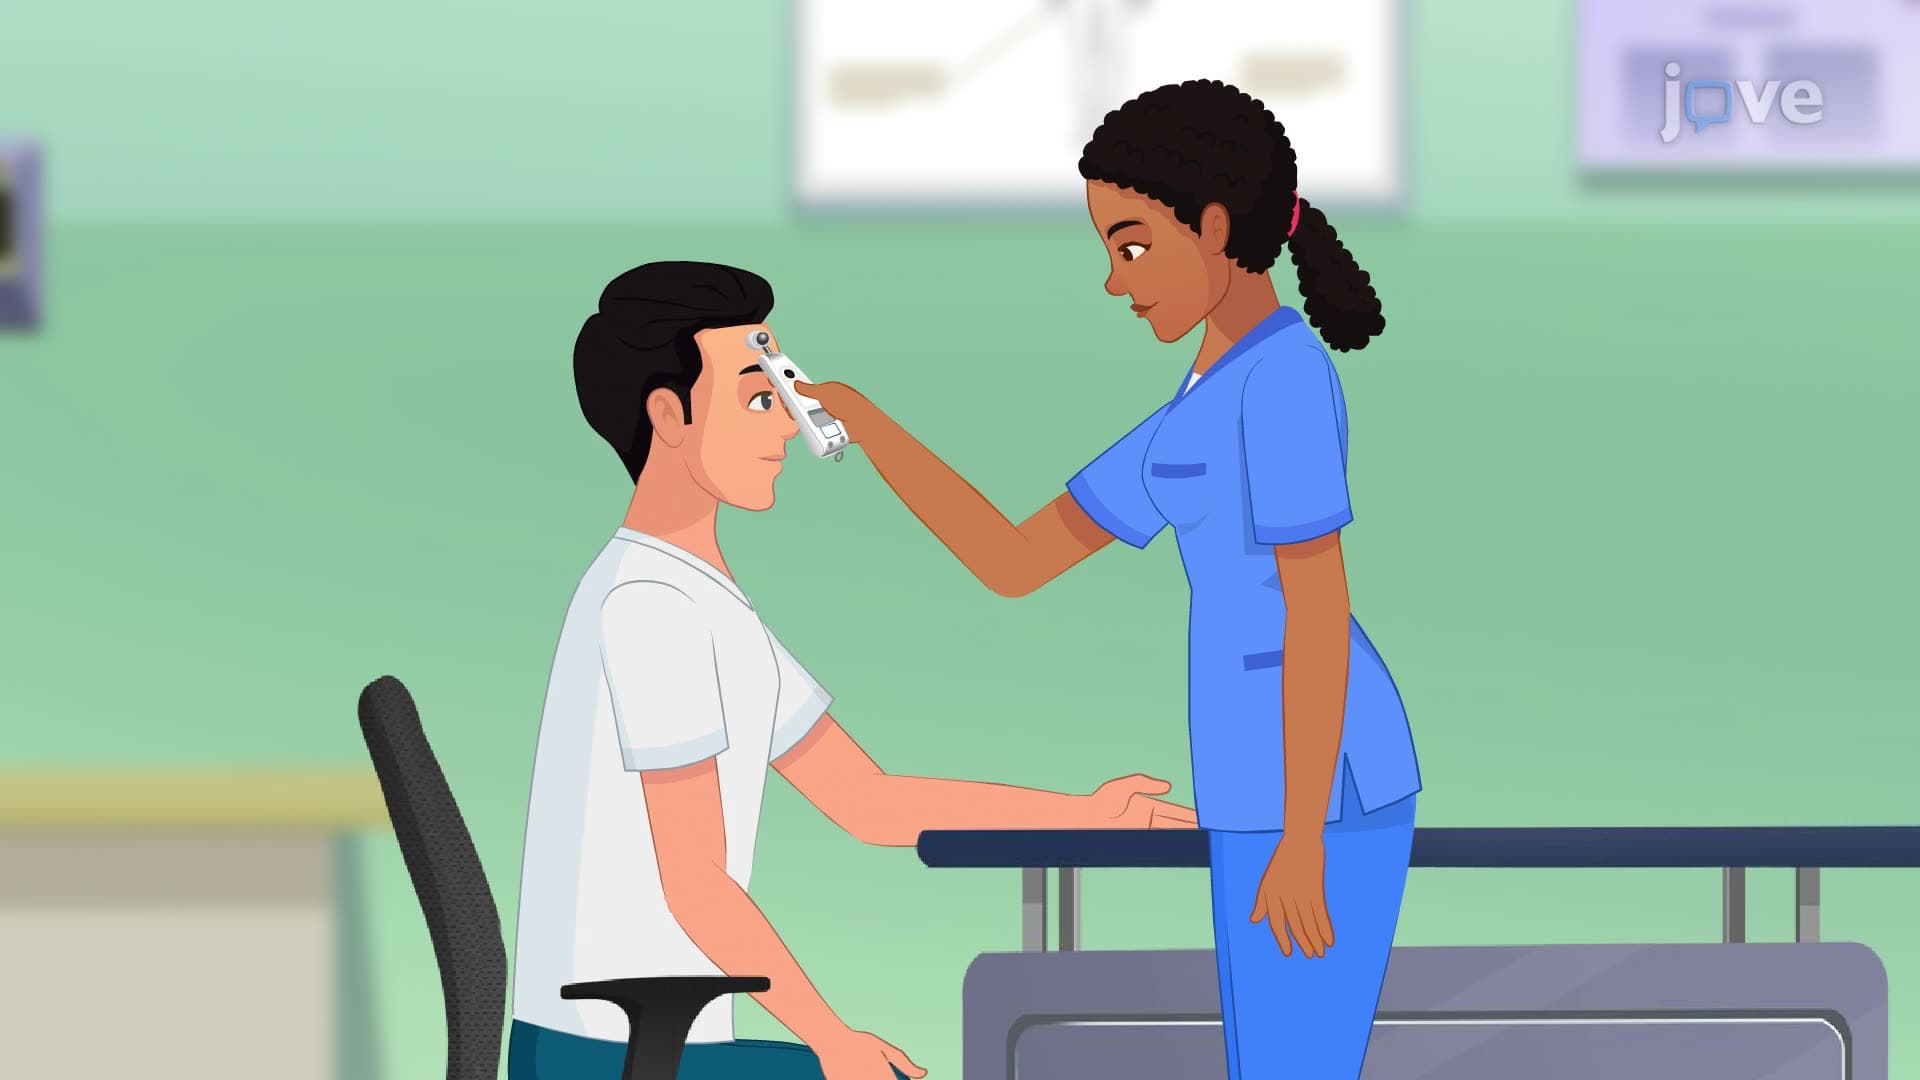
Temperature Measurement Sites
Oral: When assessing oral temperature, the thermometer tip should be placed under the tongue in the posterior sublingual pocket. It offers accurate readings and can be...
 01:14
Assessing Body Temperature - Oral
Step 1:
Start by practicing proper hand hygiene to prevent the spread of microorganisms.
Step 2:
Take the thermometer out of the charging unit, switch it on, and wait for the ready sign.
Step 3:
Gently slide the probe cover until a click is heard. This simple action prevents cross-contamination and ensures the correct placement of the probe cover.
Step 4:
Instruct the patient to open their mouth and place...
 01:27
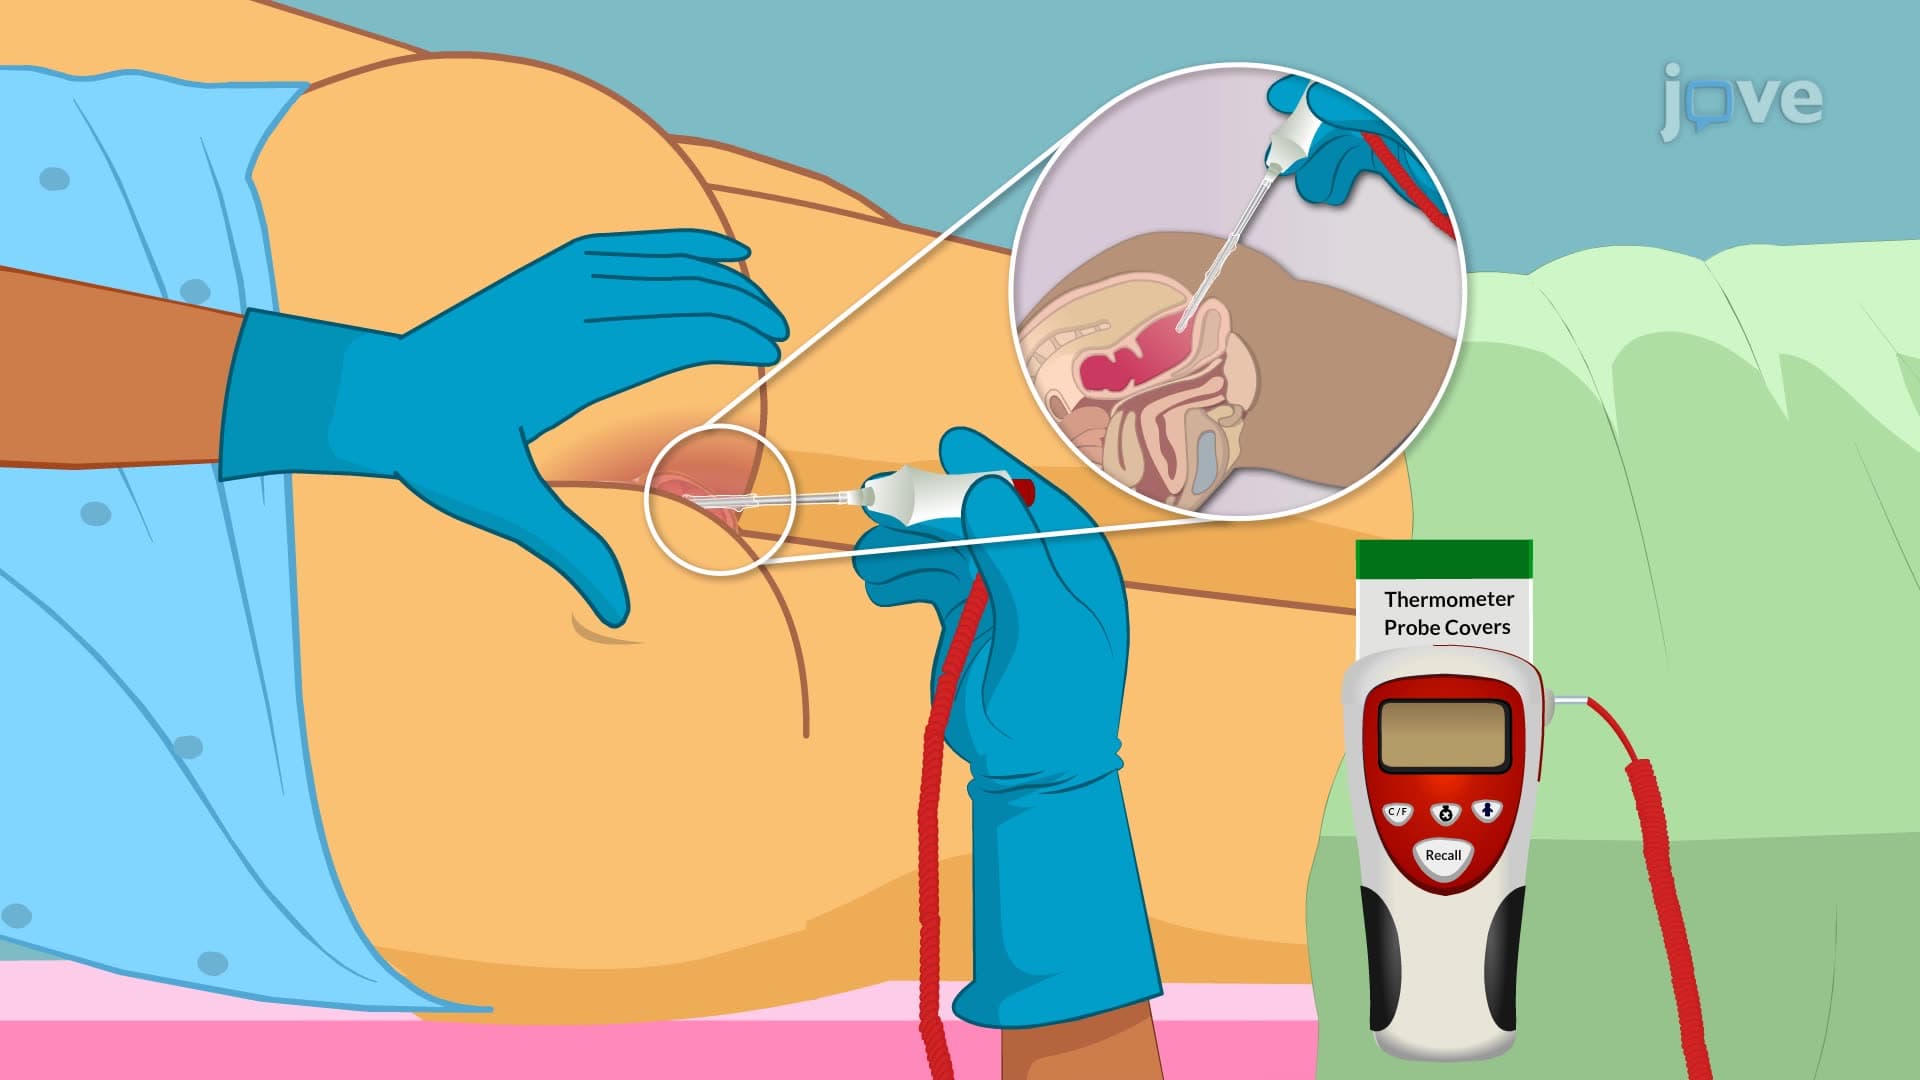
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:19
Assessing Body Temperature - Temporal Artery
Step 1: Perform hand hygiene and don a fresh pair of gloves to prevent cross-infection and ensure patient safety.
Step 2: Explain the procedure to the patient to establish trust. Clear communication establishes trust with the patient, ensures they understand what to expect, promotes cooperation, and enhances comfort during the procedure.
Step 3: Assess the patient's forehead...
 01:11
Blinding