Related Experiment Video
Updated: Feb 5, 2026

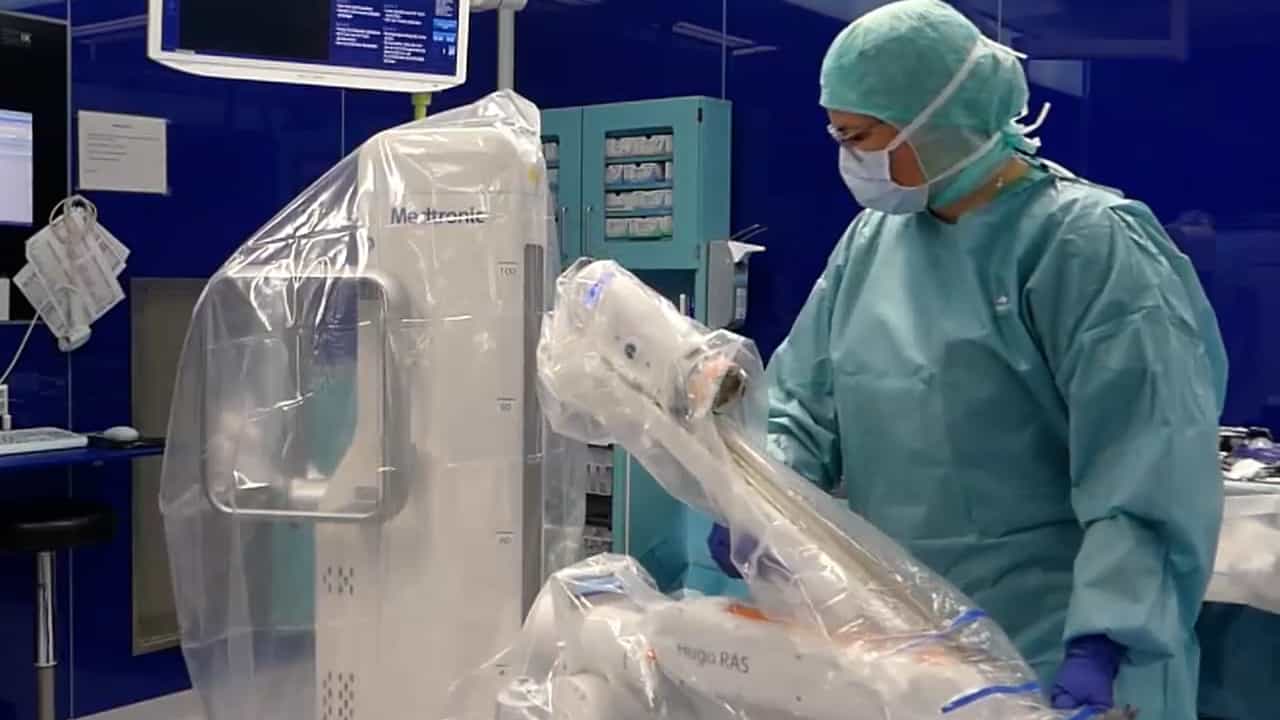
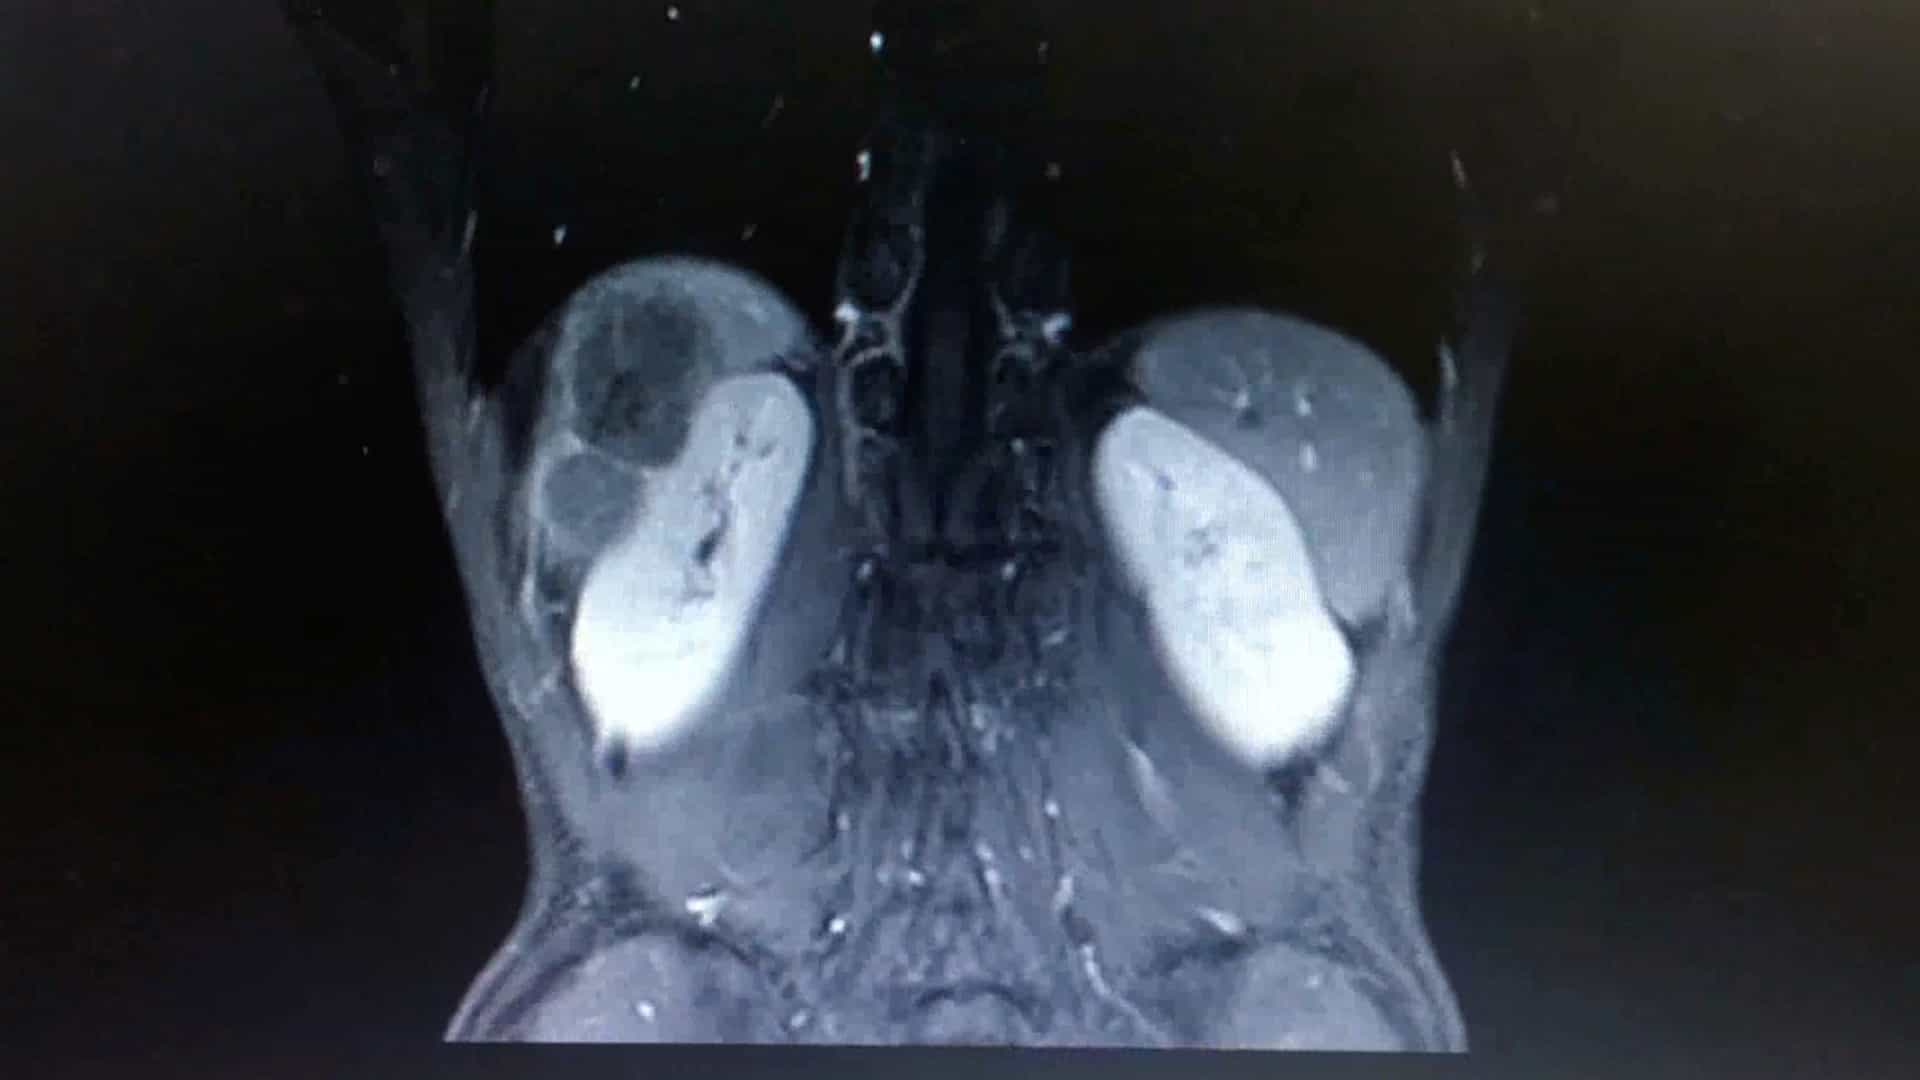
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Robotic Versus Laparoscopic Total Mesorectal Excision for Sphincter-Saving Surgery: Results of a Single-Center Series
Philippe Rouanet1, Martin Marie Bertrand2, Marta Jarlier3
1Surgical Oncology Department, Institut du Cancer de Montpellier (ICM), Univ Montpellier, Montpellier, France. philippe.rouanet@icm.unicancer.fr.

Objective:
The aim of this study is to compare robotic total mesorectal excision (R-TME) with laparoscopic TME (L-TME) in a series of consecutive rectal cancer patients.
Background:
R-TME and L-TME have drawn contradictory reports. A recent phase III trial (ROLARR) concluded that R-TME performed by surgeons with varying experience did not confer an advantage in rectal cancer resection.
Patients And Methods:
In this retrospective single-center cohort study (8/2008 to 4/2015), data were prospectively registered. A total of 200 L-TME and 200 R-TME were operated consecutively without selection. The primary outcome was the conversion rate to open laparotomy or transanal TME. The secondary endpoints were type of anastomosis, operative time, postoperative morbidity, circumferential radial (CRM) and distal margins, quality of life, bladder and sexual dysfunction, and oncological outcomes.
Results:
Baseline characteristics were well balanced. Type of anastomosis [colo-anal anastomosis (CAA) 40% vs 49%; p < 0.001], transanal TME (5% vs 13%; p = 0.005), and conversion rate (2% vs 9.5%; odd ratio (OR): 0.19 [95% confidence interval (CI): 0.05-0.60]) were significantly different. Intersphincteric resection (39% vs 47%), diverting stoma (66.5% vs 68%), CRM involvement, median operative time (243 vs 232 min), and R0 resection rate were similar. Conversion risk was lower for R-TME in male patients and those with small tumors (< 5 cm). The 3-year overall survival rate was 84.1% [77.3-88.9%] and 88.4% [82.9-92.2%] in the R-TME and L-TME group. No significant differences were reported in quality of life, and urinary or sexual function.
Conclusions:
R-TME is less likely to be converted to open surgery than L-TME; operative time and curative pathologic criteria are equivalent. Future prospective trial should compare standardized procedures performed by experienced surgeons for subgroups of high-risk patients.
Related Concept Videos
 01:13
Patient-centered Care
 01:54
Base Excision Repair
The first step of...
 01:08
Nucleotide Excision Repair
 01:27
Psychodynamic Perspectives on Personality
Psychodynamic theorists argue that unconscious...
 02:33
Lattice Centering and Coordination Number
Types of Unit Cells
Imagine taking a large number of identical...
 00:58
Center of Gravity