Related Experiment Video
Updated: Feb 5, 2026

Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Consolidation mFOLFOX6 Chemotherapy After Chemoradiotherapy Improves Survival in Patients With Locally Advanced
Michael R Marco1, Lihong Zhou1, Sujata Patil2
1Department of Surgery, Memorial Sloan Kettering Cancer Center, New York, New York.

Background:
Adding modified FOLFOX6 (folinic acid, fluorouracil, and oxaliplatin) after chemoradiotherapy and lengthening the chemoradiotherapy-to-surgery interval is associated with an increase in the proportion of rectal cancer patients with a pathological complete response.
Objective:
The purpose of this study was to analyze disease-free and overall survival.
Design:
This was a nonrandomized phase II trial.
Settings:
The study was conducted at multiple institutions.
Patients:
Four sequential study groups with stage II or III rectal cancer were included.
Intervention:
All of the patients received 50 Gy of radiation with concurrent continuous infusion of fluorouracil for 5 weeks. Patients in each group received 0, 2, 4, or 6 cycles of modified FOLFOX6 after chemoradiation and before total mesorectal excision. Patients were recommended to receive adjuvant chemotherapy after surgery to complete a total of 8 cycles of modified FOLFOX6.
Main Outcome Measures:
The trial was powered to detect differences in pathological complete response, which was reported previously. Disease-free and overall survival are the main outcomes for the current study.
Results:
Of 259 patients, 211 had a complete follow-up. Median follow-up was 59 months (range, 9-125 mo). The mean number of total chemotherapy cycles differed among the 4 groups (p = 0.002), because one third of patients in the group assigned to no preoperative FOLFOX did not receive any adjuvant chemotherapy. Disease-free survival was significantly associated with study group, ypTNM stage, and pathological complete response (p = 0.004, <0.001, and 0.001). A secondary analysis including only patients who received ≥1 cycle of FOLFOX still showed differences in survival between study groups (p = 0.03).
Limitations:
The trial was not randomized and was not powered to show differences in survival. Survival data were not available for 19% of the patients.
Conclusions:
Adding modified FOLFOX6 after chemoradiotherapy and before total mesorectal excision increases compliance with systemic chemotherapy and disease-free survival in patients with locally advanced rectal cancer. Neoadjuvant consolidation chemotherapy may have benefits beyond increasing pathological complete response rates. See Video Abstract at http://links.lww.com/DCR/A739.
Related Concept Videos
 01:21
Cancer Survival Analysis
 01:27
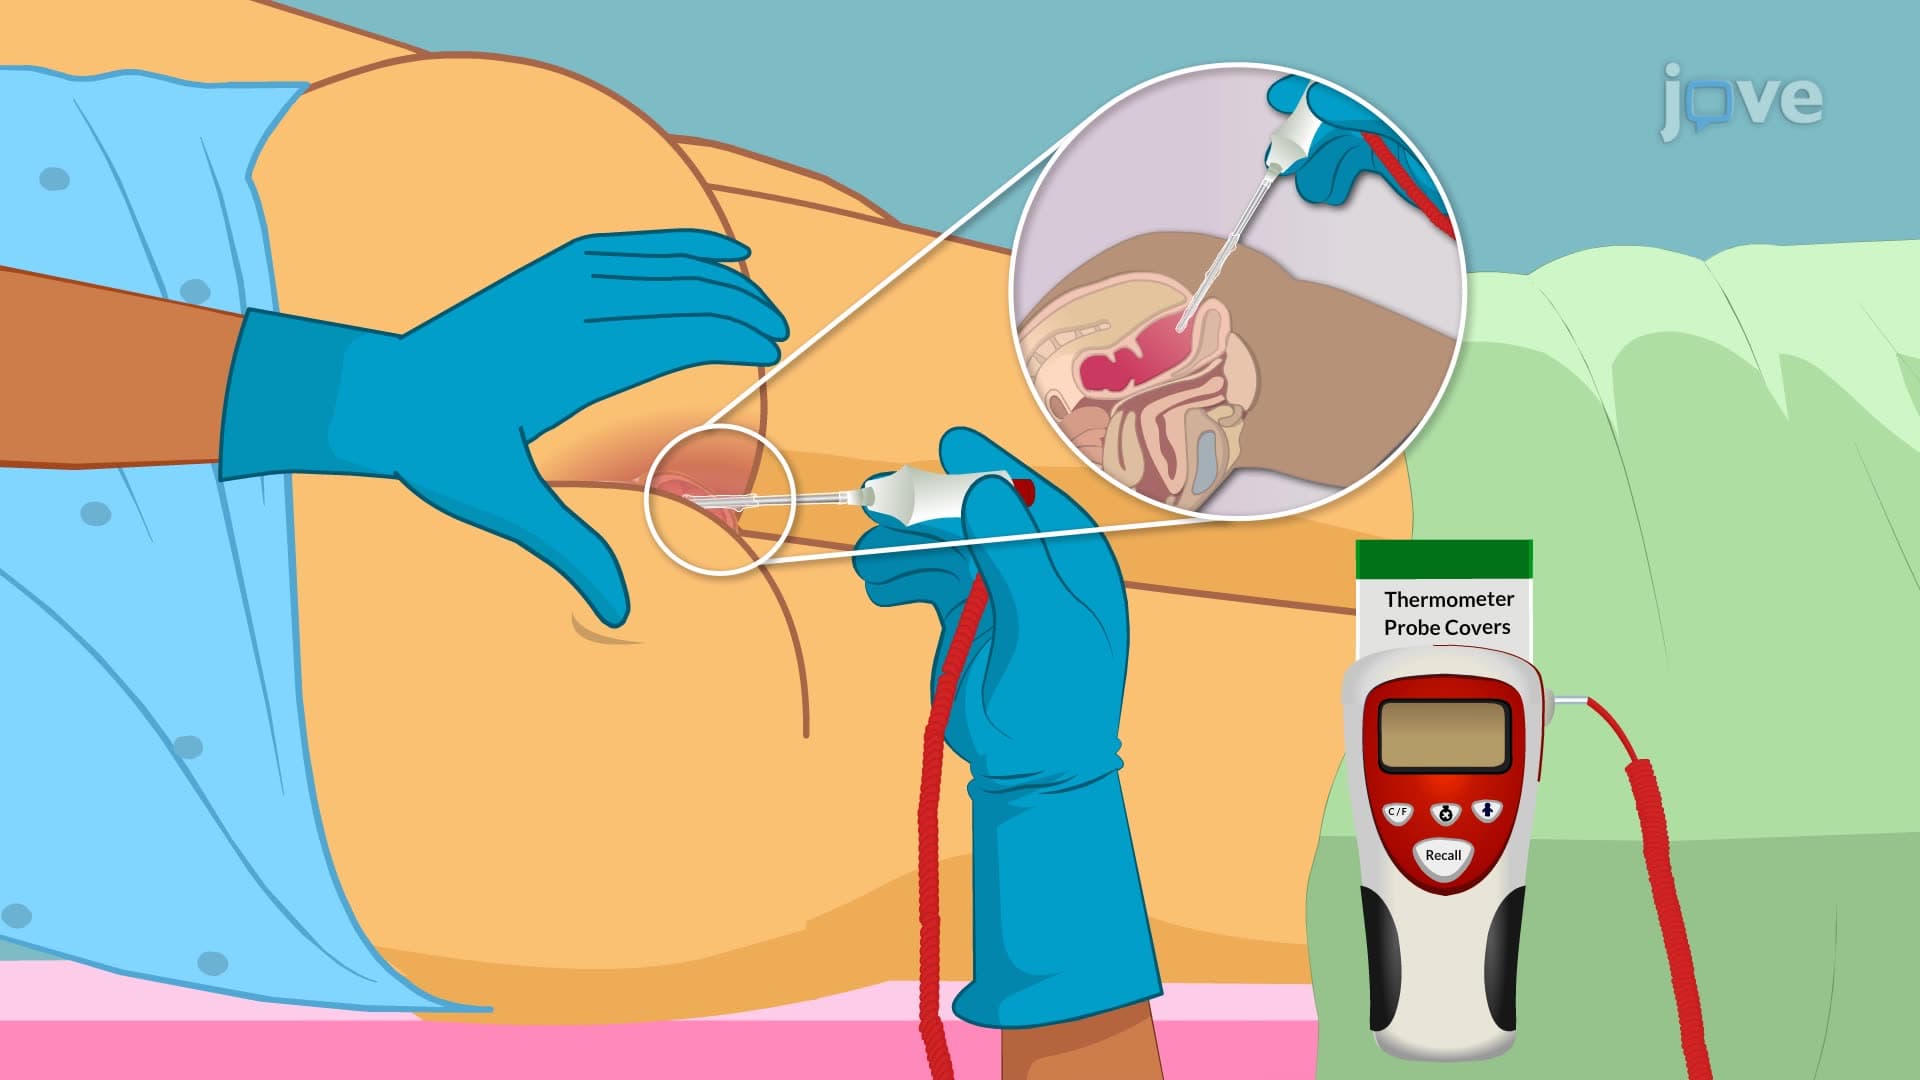
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:11
Clinical Trials: Overview
 01:12
Trial and Error and Algorithm
 01:16
Clinical Trials
There are four phases in a clinical trial. A phase one...
 01:18
Survival Curves
The Kaplan-Meier estimator is the most common method for constructing survival curves. This...