Related Experiment Video
Updated: Feb 5, 2026
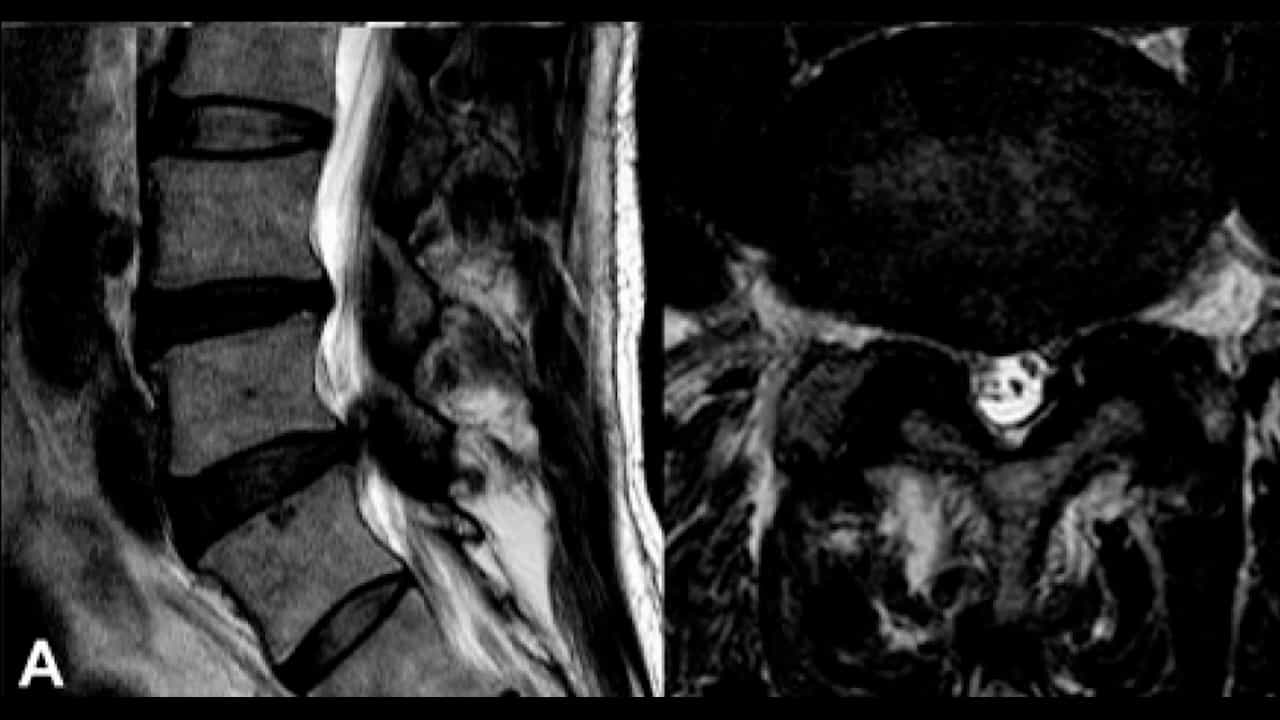
Full-Endoscopic Interlaminar Approach for Decompression of Lateral Recess Stenosis
Published on: February 24, 2023
C5 palsy following posterior decompression and instrumentation in cervical stenosis: Single center experience and
Patrick W Hitchon1, Toshio Moritani2, Royce W Woodroffe1
1University of Iowa Carver College of Medicine, Department of Neurosurgery, Iowa City, IA, United States.

Objective:
Causation and avoidance of C5 palsy after laminectomy have proven elusive, with multiple factors incriminated including width of the laminectomy, spinal cord migration, C5 neural foraminal stenosis, or intraoperative C5 root traction. In an attempt to identify risk factors for C5 palsy after decompression in cervical stenosis and myelopathy, the following review was conducted. This report is from a single center with consistent criteria for diagnosis and management of cervical stenosis and myelopathy.
Patients And Methods:
We retrospectively reviewed 63 patients with cervical stenosis and myelopathy who had been treated with laminectomy with instrumentation at the C4-6 level. Imaging studies reviewed included plain X-ray films, magnetic resonance imaging (MRI), and computed tomography (CT) scans of the cervical spine. Health-related outcomes were assessed before and at follow-up and included Visual Analog Scale (VAS) for pain (1-10), Japanese Orthopedic Association (JOA) score for myelopathy (0-18), and SF-36 physical functioning, energy and fatigue, and general health categories (0-100).
Results:
In 53 patients (control group), decompression and instrumentation was accomplished without incident, but 5 patients developed lasting postoperative C5 palsy. At follow-up, there were overall significant improvements in VAS, JOA, and SF-36 physical functioning and general health domains. Subsequent to surgery, a loss of lordosis of 5° and an increase in C2 sagittal vertical axis (SVA) of 17 mm was significant. There was, however, no significant difference between control and C5 palsy patients in lordosis and C2 SVA, before or after surgery. Postoperative MRI studies were obtained in 15 of the control patients and 6 of the C5 palsy patients. Postoperative width of the laminectomy as well as the caliber of the C5 neural foramina in the control and C5 palsy cohorts were not statistically different. Though the posterior displacement of the cord in the C5 palsy cohort was larger than in controls, this difference was also not significant.
Conclusion:
The above findings suggest that the cause of C5 palsy remains elusive. Though our incidence of lasting C5 palsy subsequent to laminectomy and instrumentation was 8%, it is probably under-reported. In our experience, laminectomy and instrumentation failed to increase lordosis and, in fact, were associated with an increase in positive cervical balance. Complications with cervical laminectomy and instrumentation are not by any means rare, and need to be emphasized in counselling patients, and selecting the approach.
Related Concept Videos
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 02:33
Lattice Centering and Coordination Number
Types of Unit Cells
Imagine taking a large number of identical...
 01:12
Instrument Calibration
Analytical Balance Calibration
An analytical balance measures mass and requires regular calibration to...
 01:25
Instrumentation Amplifier
To overcome this challenge, an ECG machine utilizes an instrumentation amplifier. This specialized amplifier is...
 01:23
Instrument Transformers