Related Experiment Video
Updated: Feb 5, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Optimal timing of complete revascularization in patients with ST-segment elevation myocardial infarction and
Wen-Qin Guo1, Lang Li1, Qiang Su1
1Department of Cardiology, the First Affiliated Hospital of Guangxi Medical University, Nanning, China, gmxu2015@163.com.

Insights
Early complete revascularization (CR) significantly reduces major adverse cardiac events (MACE) and myocardial infarction (MI) in ST-elevation myocardial infarction patients with multivessel disease compared to culprit-only revascularization (COR). Optimal timing for CR requires further investigation.
Area of Science:
- Cardiology
- Interventional Cardiology
- Clinical Research
Background:
- Optimal revascularization strategy for ST-elevation myocardial infarction (STEMI) with multivessel disease remains unclear.
- This meta-analysis addresses the optimal treatment approach for these complex cardiac patients.
Purpose of the Study:
- To determine the optimal revascularization strategy for patients with STEMI and multivessel disease.
- To compare early complete revascularization (CR), delayed CR, and culprit-only revascularization (COR).
Main Methods:
- Systematic literature search of PubMed, Cochrane Library, and clinicaltrials.gov (2000-2017).
- Pairwise and Bayesian network meta-analysis of 11 randomized controlled trials (3,170 patients).
- Primary endpoint: Major Adverse Cardiac Events (MACE); Secondary endpoints: mortality, MI, repeat revascularization.
Main Results:
- Early CR significantly reduced MACE (RR 0.47), MI (RR 0.55), and repeat revascularization (RR 0.35) compared to COR.
- Early CR demonstrated the highest probability for optimal treatment of MACE, MI, and repeat revascularization.
- No significant difference in all-cause mortality was observed between early CR and COR.
Conclusions:
- Early complete revascularization during index hospitalization is superior to culprit-only revascularization for reducing MACE in STEMI patients with multivessel disease.
- Further research is needed to confirm survival benefits of early CR.
- The optimal timing for complete revascularization requires additional investigation due to limited data.
Introduction:
The optimal revascularization strategy for patients with ST-segment elevation myocardial infarction and multivessel disease is unclear. In this study, we performed a meta-analysis to determine the optimal revascularization strategy for treating these patients.
Methods:
Searches of PubMed, the Cochrane Library, clinicaltrial.gov, and the reference lists of relevant papers were performed covering the period between the year 2000 and March 20, 2017. A pairwise analysis and a Bayesian network meta-analysis were performed to compare the effectiveness of early complete revascularization (CR) during the index hospitalization, delayed CR, and culprit only revascularization (COR). The primary endpoint was the incidence of major adverse cardiac events (MACE), which were defined as the composite of recurrent myocardial infarction (MI), repeat revascularization, and all-cause mortality. The secondary endpoints were the rates of all-cause mortality, recurrent MI, and repeat revascularization. This study is registered at PROSPERO under registration number CRD42017059980.
Results:
Eleven randomized controlled trials including a total of 3,170 patients were identified. A pairwise meta-analysis showed that compared with COR, early CR was associated with significantly decreased risks of MACE (relative risk [RR] 0.47, 95% CI 0.39-0.56), MI (RR 0.55, 95% CI 0.37-0.83), and repeat revascularization (RR 0.35, 95% CI 0.27-0.46) but not of all-cause mortality (RR 0.78, 95% CI 0.52-1.16). These results were confirmed by trial sequential analysis. The network meta-analysis showed that early CR had the highest probability of being the first treatment option during MACE (89.2%), MI (83.3%), and repeat revascularization (80.4%).
Conclusion:
Early CR during the index hospitalization was markedly superior to COR with respect to reducing the risk of MACE, as CR significantly decreased the risks of MI and repeat revascularization compared with COR. However, further study is warranted to determine whether CR during the index hospitalization can improve survival in patients with concurrent ST-segment elevation myocardial infarction and multivessel disease. The optimal timing of CR remains inconclusive considering the small number of studies and patients included in the analysis comparing early and delayed CR.
More Related Videos


Related Concept Videos
 03:12
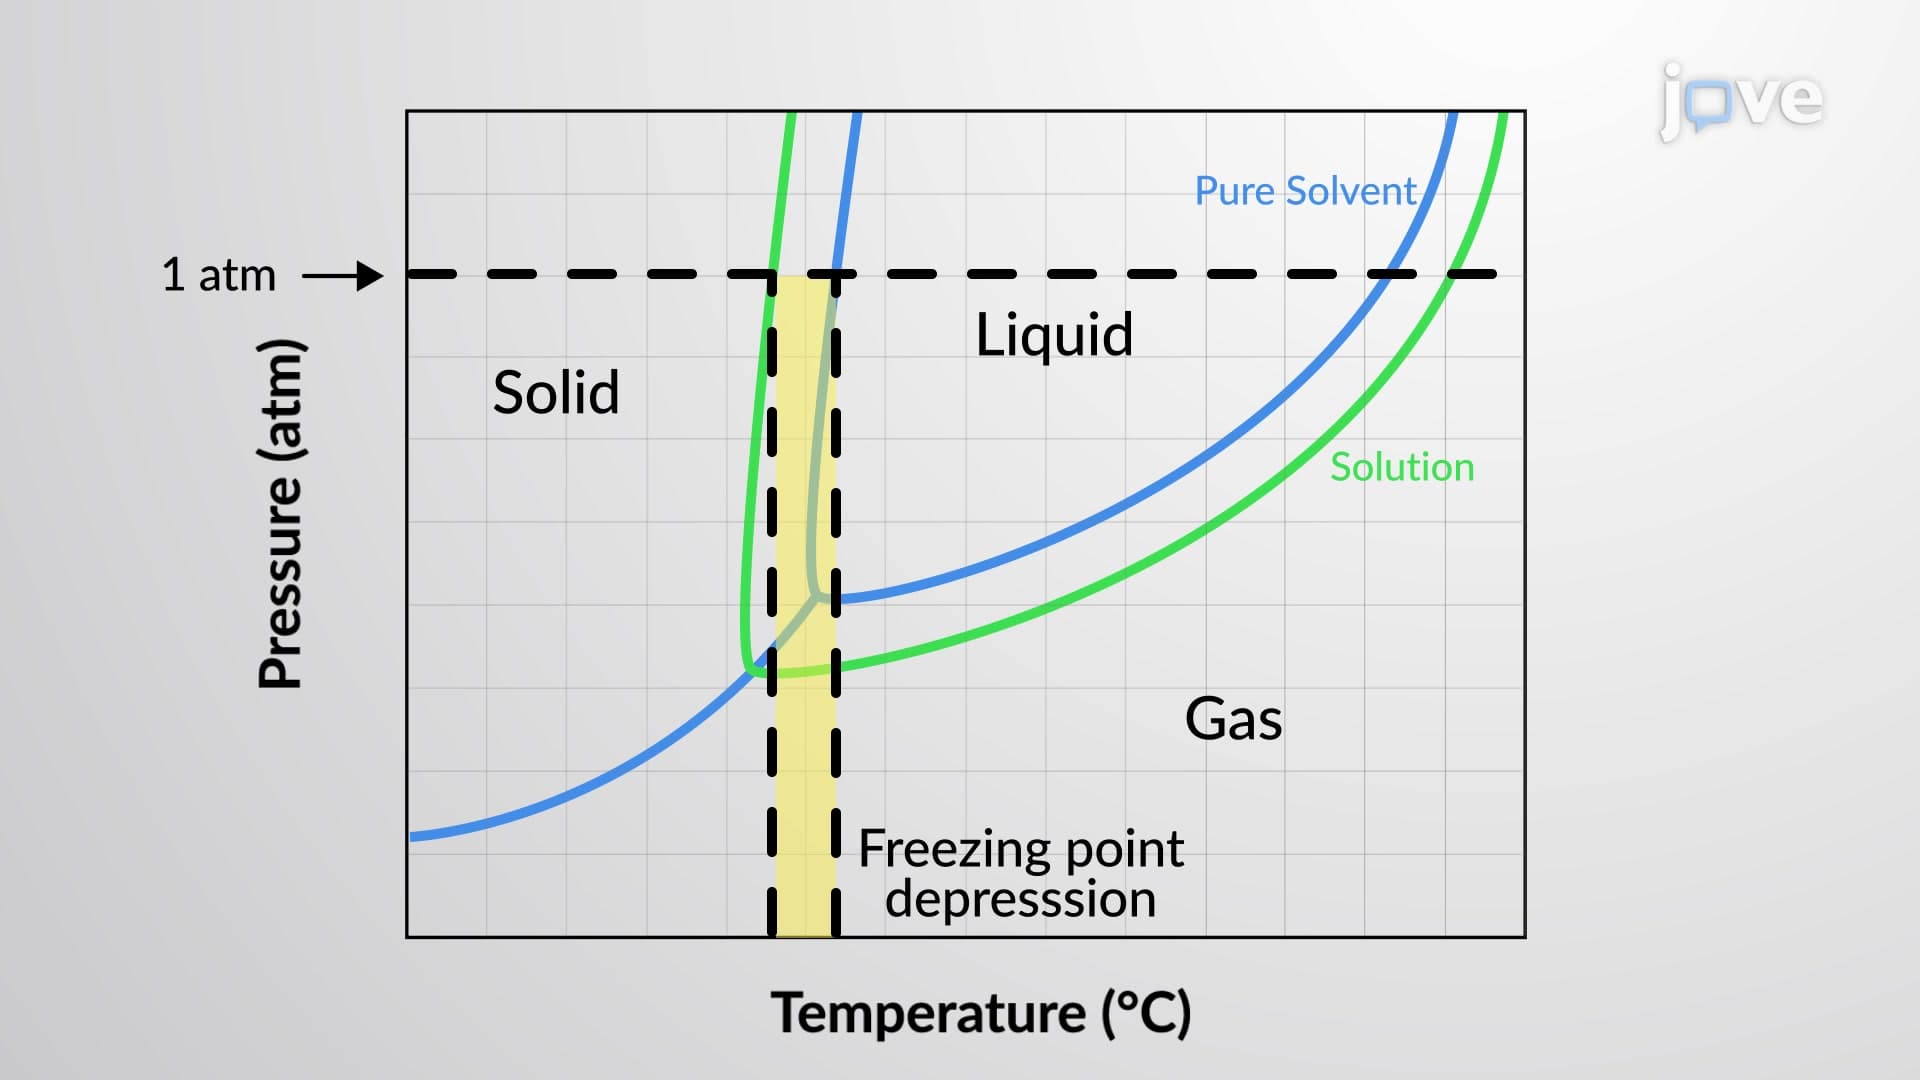
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 02:26
Protein Networks
These interactions can be represented through maps depicting protein-protein interaction networks, represented as nodes and edges. Nodes are circles that are representative of a protein,...
02:26Protein Networks
 01:09
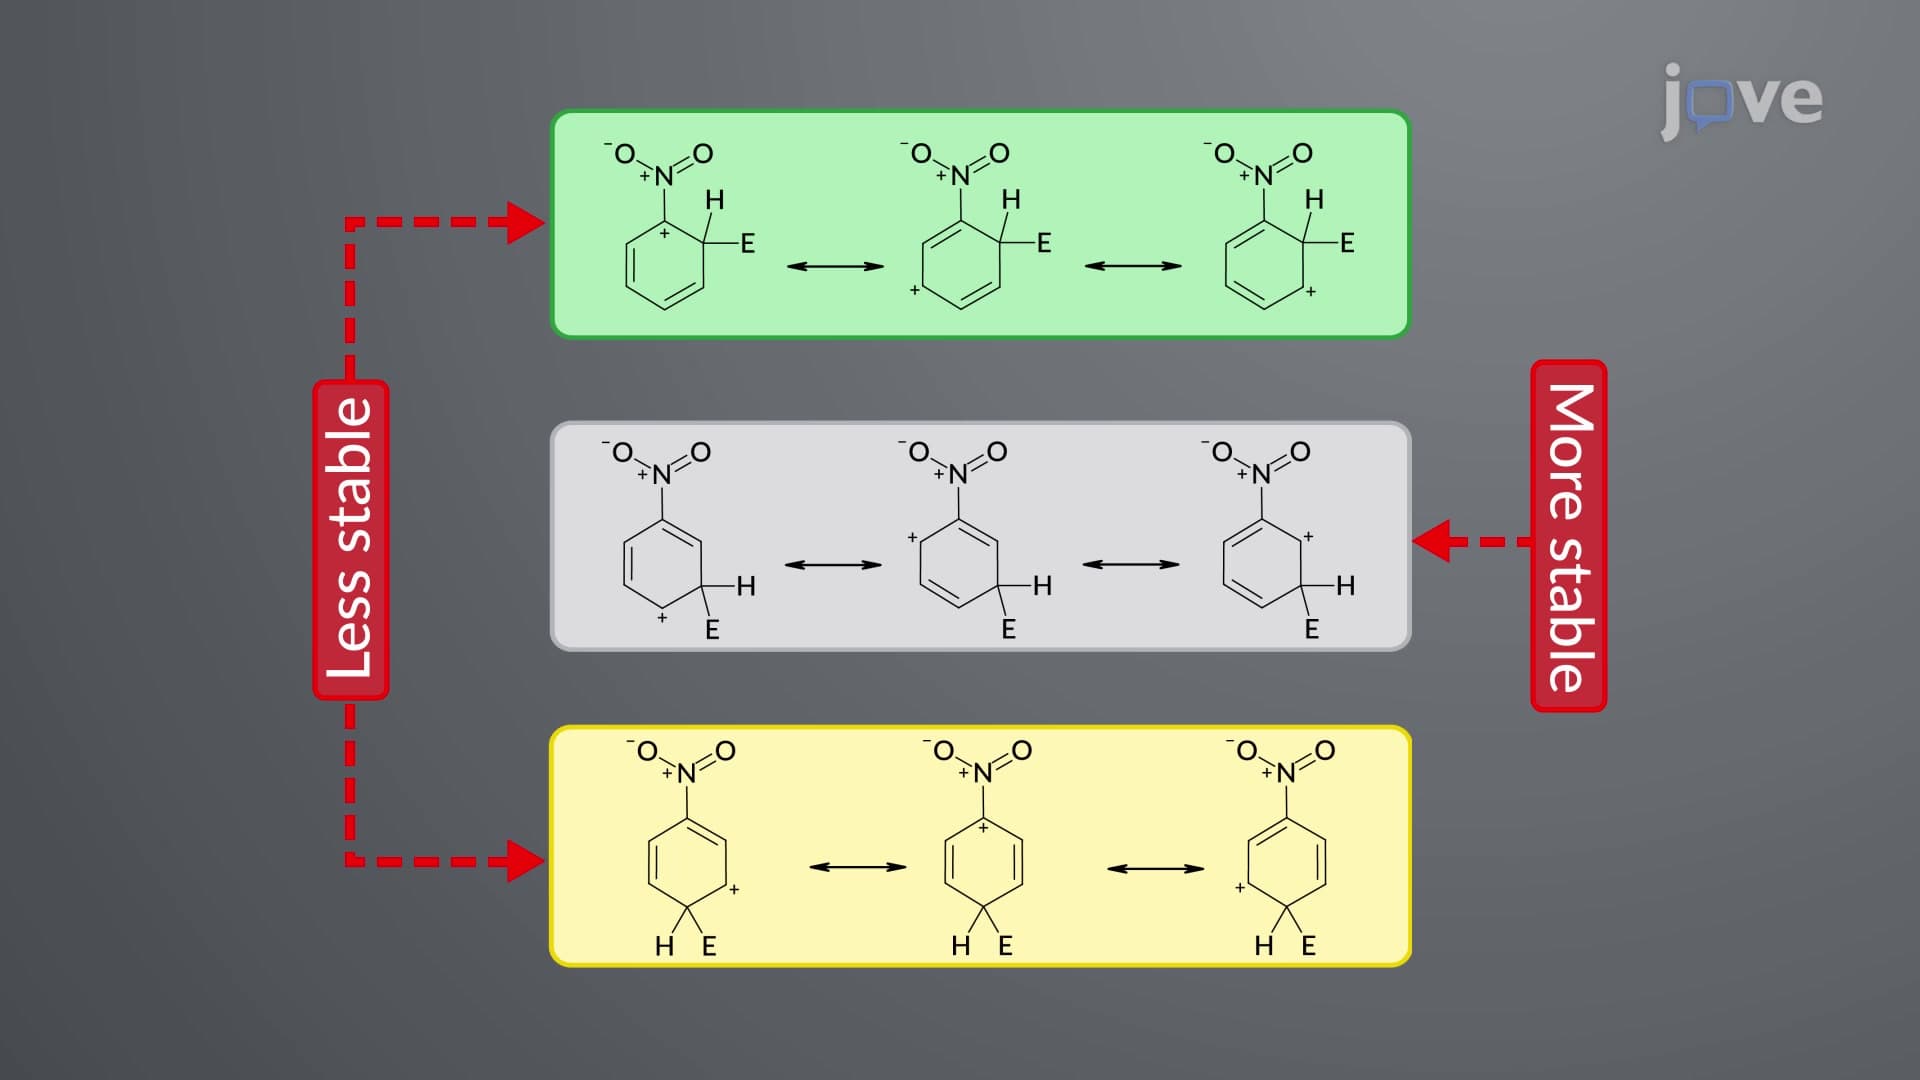
Directing Effect of Substituents: meta-Directing Groups
 01:20
Elevation of Intermediate Points on Vertical Curves
 02:18
Network Covalent Solids
To break or to melt a covalent network solid, covalent bonds must be broken. Because covalent bonds are relatively strong, covalent network solids are typically...