Related Experiment Video
Updated: Feb 5, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Guideline-indicated treatments and diagnostics, GRACE risk score, and survival for non-ST elevation myocardial
Marlous Hall1, Owen J Bebb1,2, Tatandashe B Dondo1
1Leeds Institute of Cardiovascular and Metabolic Medicine, University of Leeds, Worsley Building, Level 11, Clarendon Way, Leeds, UK.

Insights
Guideline-indicated treatments for non-ST-elevation myocardial infarction (NSTEMI) improve survival, especially for high-risk patients. However, optimal care use decreases as patient risk increases.
Area of Science:
- Cardiology
- Clinical Research
- Public Health
Background:
- Non-ST-elevation myocardial infarction (NSTEMI) management aims to improve patient survival.
- The GRACE risk score stratifies NSTEMI patients, guiding treatment intensity.
- Understanding the association between guideline-indicated care and survival is crucial for optimizing NSTEMI outcomes.
Purpose of the Study:
- To determine if guideline-indicated treatments and diagnostics for NSTEMI are associated with improved survival based on the GRACE risk score.
- To assess if this survival benefit persists beyond hospital discharge.
- To investigate the relationship between the level of patient risk and the utilization of optimal care.
Main Methods:
- A national cohort study involving 389,507 NSTEMI patients from 232 hospitals (2003-2013) using the MINAP registry.
- Flexible parametric survival modeling with time-varying covariates was employed to estimate all-cause survival.
- Optimal care was defined as receiving all eligible treatments, with risk stratified by the GRACE risk score.
Main Results:
- Optimal care use was inversely related to GRACE risk score (25.6% low-risk, 18.6% intermediate-risk, 11.5% high-risk).
- At 30 days, optimal care was linked to improved survival in high-risk (aHR 0.66) and intermediate-risk (aHR 0.74) NSTEMI patients.
- This survival benefit persisted long-term (8.4 years) only for high-risk NSTEMI (aHR 0.66), with no association found for low-risk patients.
Conclusions:
- Optimal use of guideline-indicated care for NSTEMI is associated with greater survival gains in higher-risk patients.
- However, the utilization of this optimal care decreases as the GRACE risk score increases.
- These findings highlight a gap in care delivery for high-risk NSTEMI patients despite proven survival benefits.
Aims:
To investigate whether improved survival from non-ST-elevation myocardial infarction (NSTEMI), according to GRACE risk score, was associated with guideline-indicated treatments and diagnostics, and persisted after hospital discharge.
Methods And Results:
National cohort study (n = 389 507 patients, n = 232 hospitals, MINAP registry), 2003-2013. The primary outcome was adjusted all-cause survival estimated using flexible parametric survival modelling with time-varying covariates. Optimal care was defined as the receipt of all eligible treatments and was inversely related to risk status (defined by the GRACE risk score): 25.6% in low, 18.6% in intermediate, and 11.5% in high-risk NSTEMI. At 30 days, the use of optimal care was associated with improved survival among high [adjusted hazard ratio (aHR) -0.66 95% confidence interval (CI) 0.53-0.86, difference in absolute mortality rate (AMR) per 100 patients (AMR/100-0.19 95% CI -0.29 to -0.08)], and intermediate (aHR = 0.74, 95% CI 0.62-0.92; AMR/100 = -0.15, 95% CI -0.23 to -0.08) risk NSTEMI. At the end of follow-up (8.4 years, median 2.3 years), the significant association between the use of all eligible guideline-indicated treatments and improved survival remained only for high-risk NSTEMI (aHR = 0.66, 95% CI 0.50-0.96; AMR/100 = -0.03, 95% CI -0.06 to -0.01). For low-risk NSTEMI, there was no association between the use of optimal care and improved survival at 30 days (aHR = 0.92, 95% CI 0.69-1.38) and at 8.4 years (aHR = 0.71, 95% CI 0.39-3.74).
Conclusion:
Optimal use of guideline-indicated care for NSTEMI was associated with greater survival gains with increasing GRACE risk, but its use decreased with increasing GRACE risk.
Related Concept Videos
 03:12
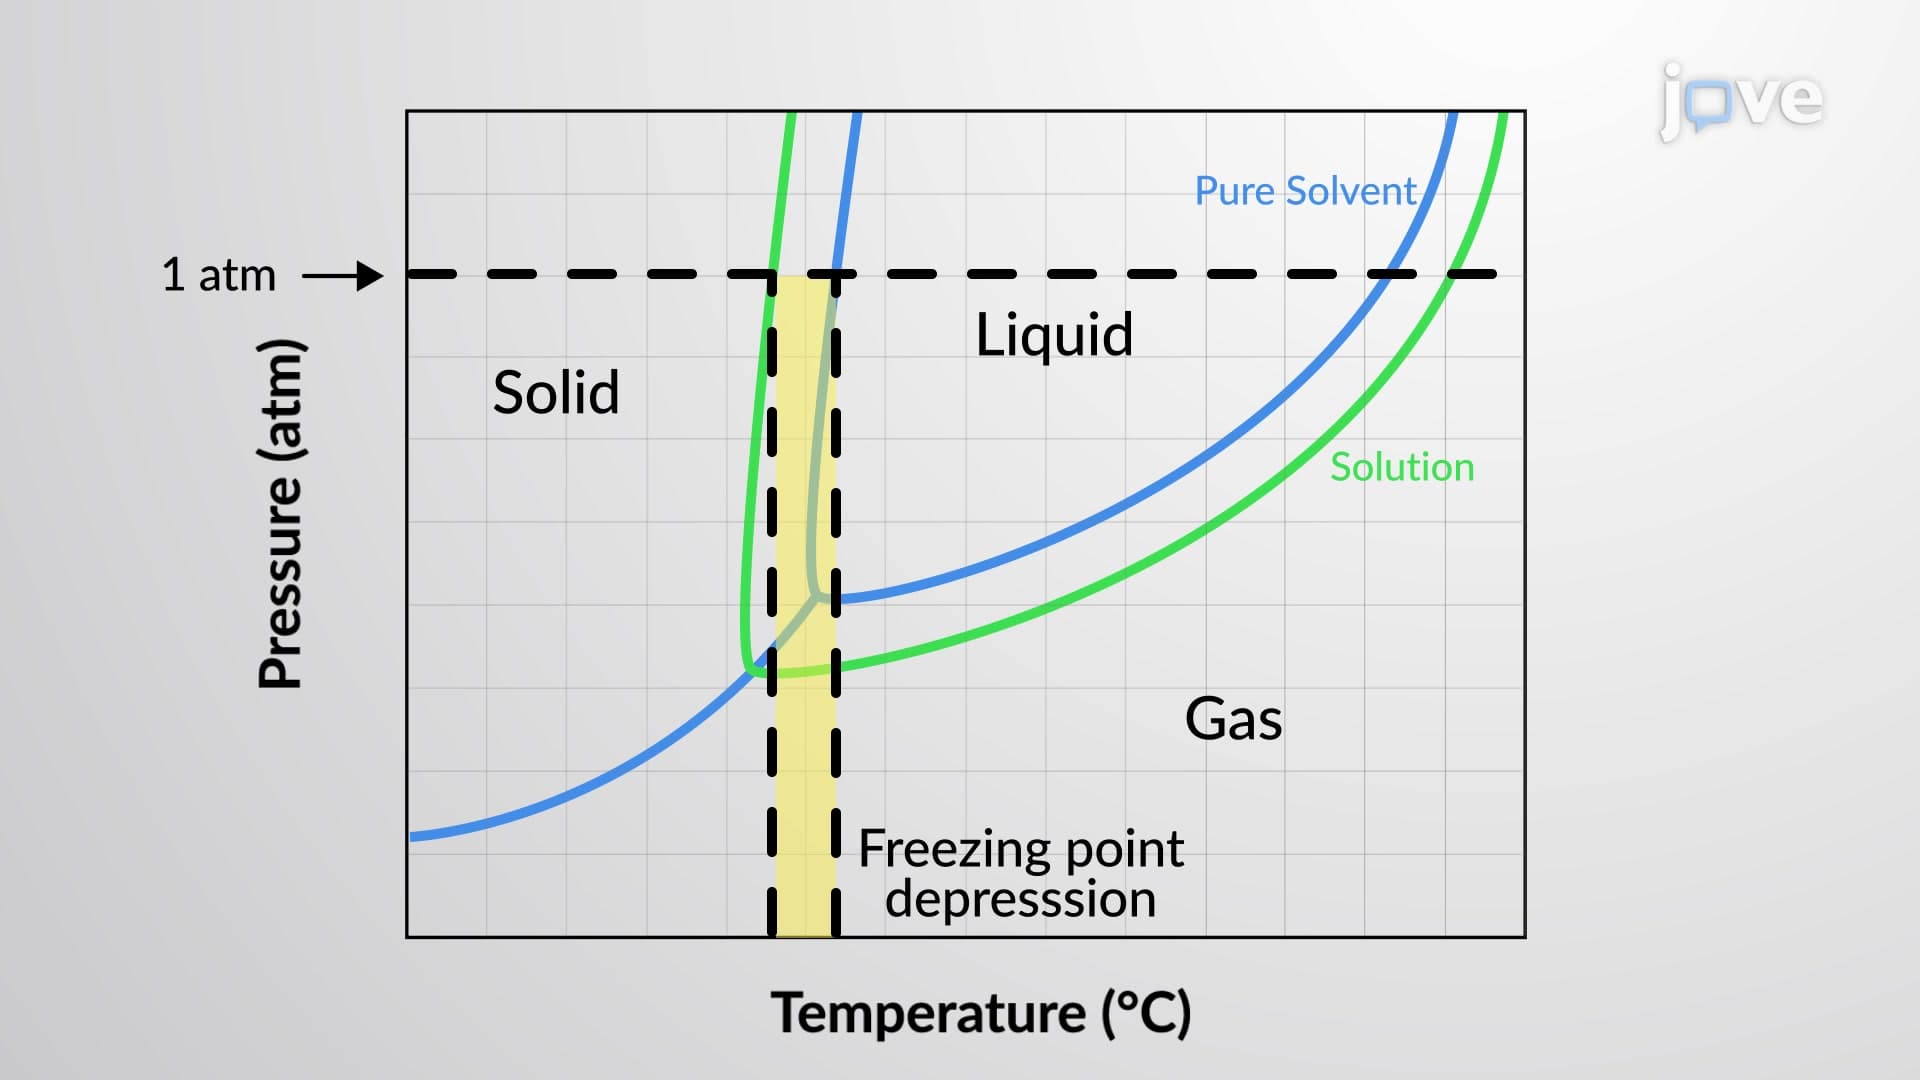
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:06
Introduction to z Scores
z scores...
 01:05
Introduction to z Scores
z scores...
 01:17
z Scores and Area Under the Curve
 01:18
Survival Curves
The Kaplan-Meier estimator is the most common method for constructing survival curves. This...
 01:19
Survival Tree
Building a Survival Tree
Constructing a...