Related Experiment Video
Updated: Feb 5, 2026
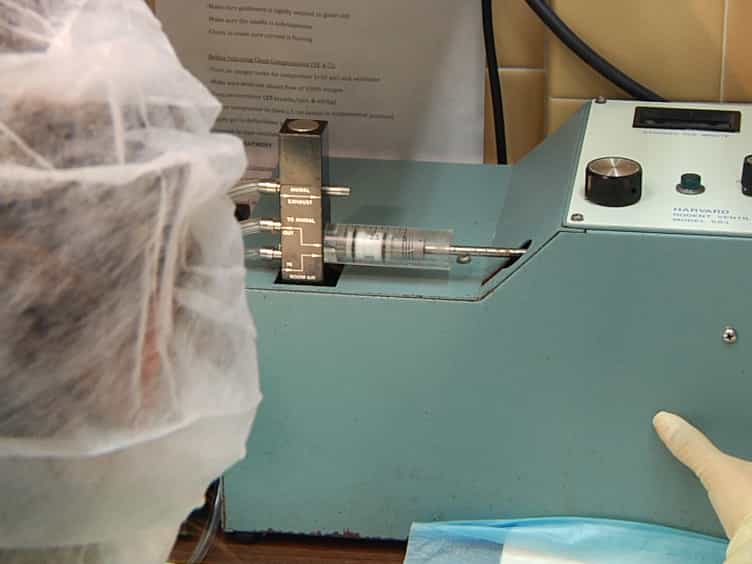
A Rat Model of Ventricular Fibrillation and Resuscitation by Conventional Closed-chest Technique
Published on: April 26, 2015
Chest compression-associated injuries in cardiac arrest patients treated with manual chest compressions versus
Benjamin Ondruschka1, Christina Baier2, Ronny Bayer2
1Institute of Legal Medicine, University of Leipzig, Leipzig, Germany. benjamin.ondruschka@medizin.uni-leipzig.de.

Abstract:
The aim of this autopsy study was to investigate chest-compression associated injuries to the trunk in out-of-hospital and in-hospital non-traumatic cardiac arrest patients treated with automated external chest compression devices (ACCD; all with LUCAS II devices) versus exclusive manual chest compressions (mCC). In this retrospective single-center study, all forensic autopsies between 2011 and 2017 were included. Injuries following cardiopulmonary resuscitation (CPR) in patients treated with mCC or ACCD were investigated and statistically compared using a bivariate logistic regression. In the seven-year period with 4433 autopsies, 614 were analyzed following CPR (mCC vs. ACCD: n = 501 vs. n = 113). The presence of any type of trunk injury was correlated with longer resuscitation intervals (30 ± 15 vs. 44 ± 25 min, p < 0.05). In comparison with mCC, treatment with ACCD led to more frequent skin emphysema (5 vs 0%, p = 0.012), pneumothorax (6 vs. 1%, p = 0.008), lung lesions (19 vs. 4%, p = 0.008), hemopericardium (3 vs 1%, p = 0.025) and liver lesions (10 vs. 1%, p = 0.001), all irrespective of confounding aspects. Higher age and longer CPR durations statistically influenced frequency of sternal and rib fractures (p < 0.001). The mean number of fractured ribs did not vary significantly between the groups (6 ± 3 vs. 7 ± 2, p = 0.09). In this cohort with unsuccessful CPR, chest compression-related injuries were more frequent following ACCD application than in the mCC group, but with only minutely increased odds ratios. The severity of injuries did not differ between the groups, and no iatrogenic injury was declared by the forensic pathologist as being fatal. In the clinical routine after successful return of spontaneous circulation a computed tomography scan for CPR-associated injuries is recommended as soon as possible.


Related Concept Videos
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:23
Behavior of Concrete Under Compressive Load
As the concrete specimen fractures under...
 01:30
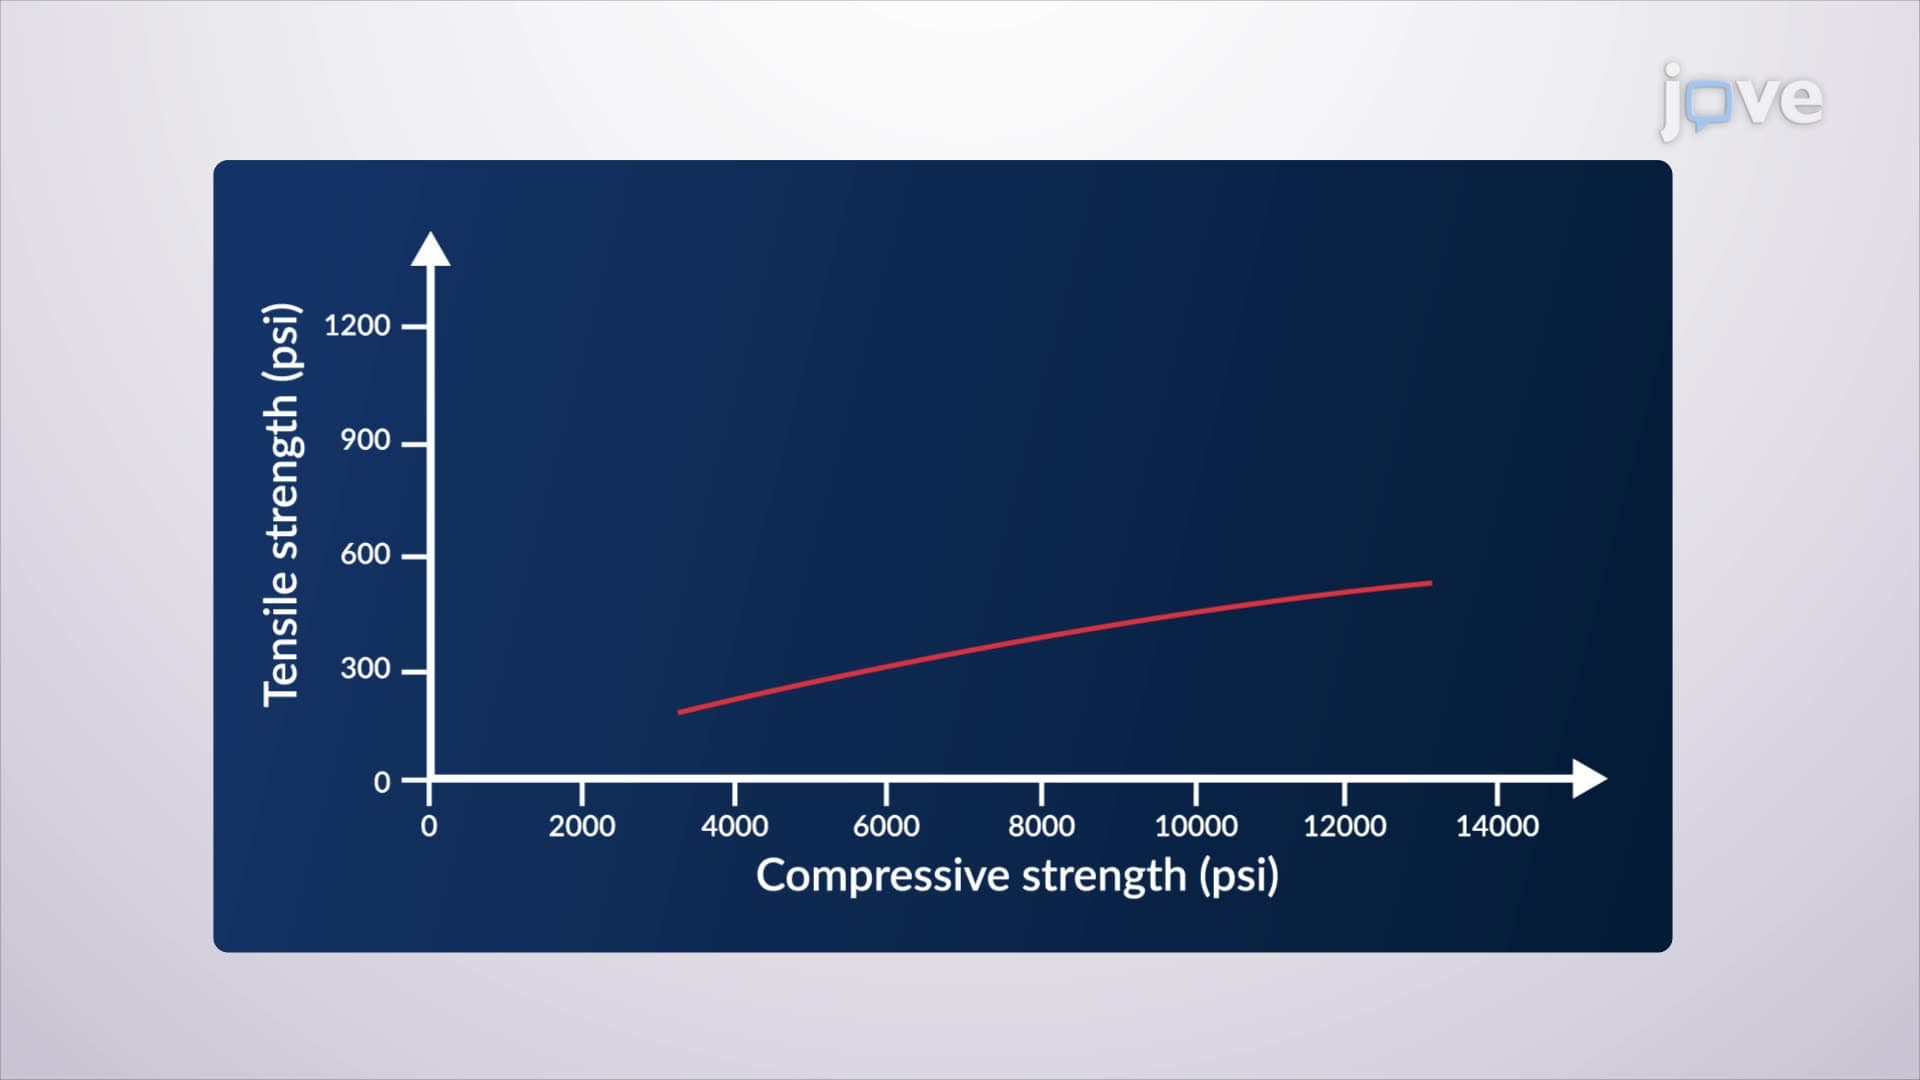
Relation Between Tensile Strength and Compressive Strength of Concrete
 01:27
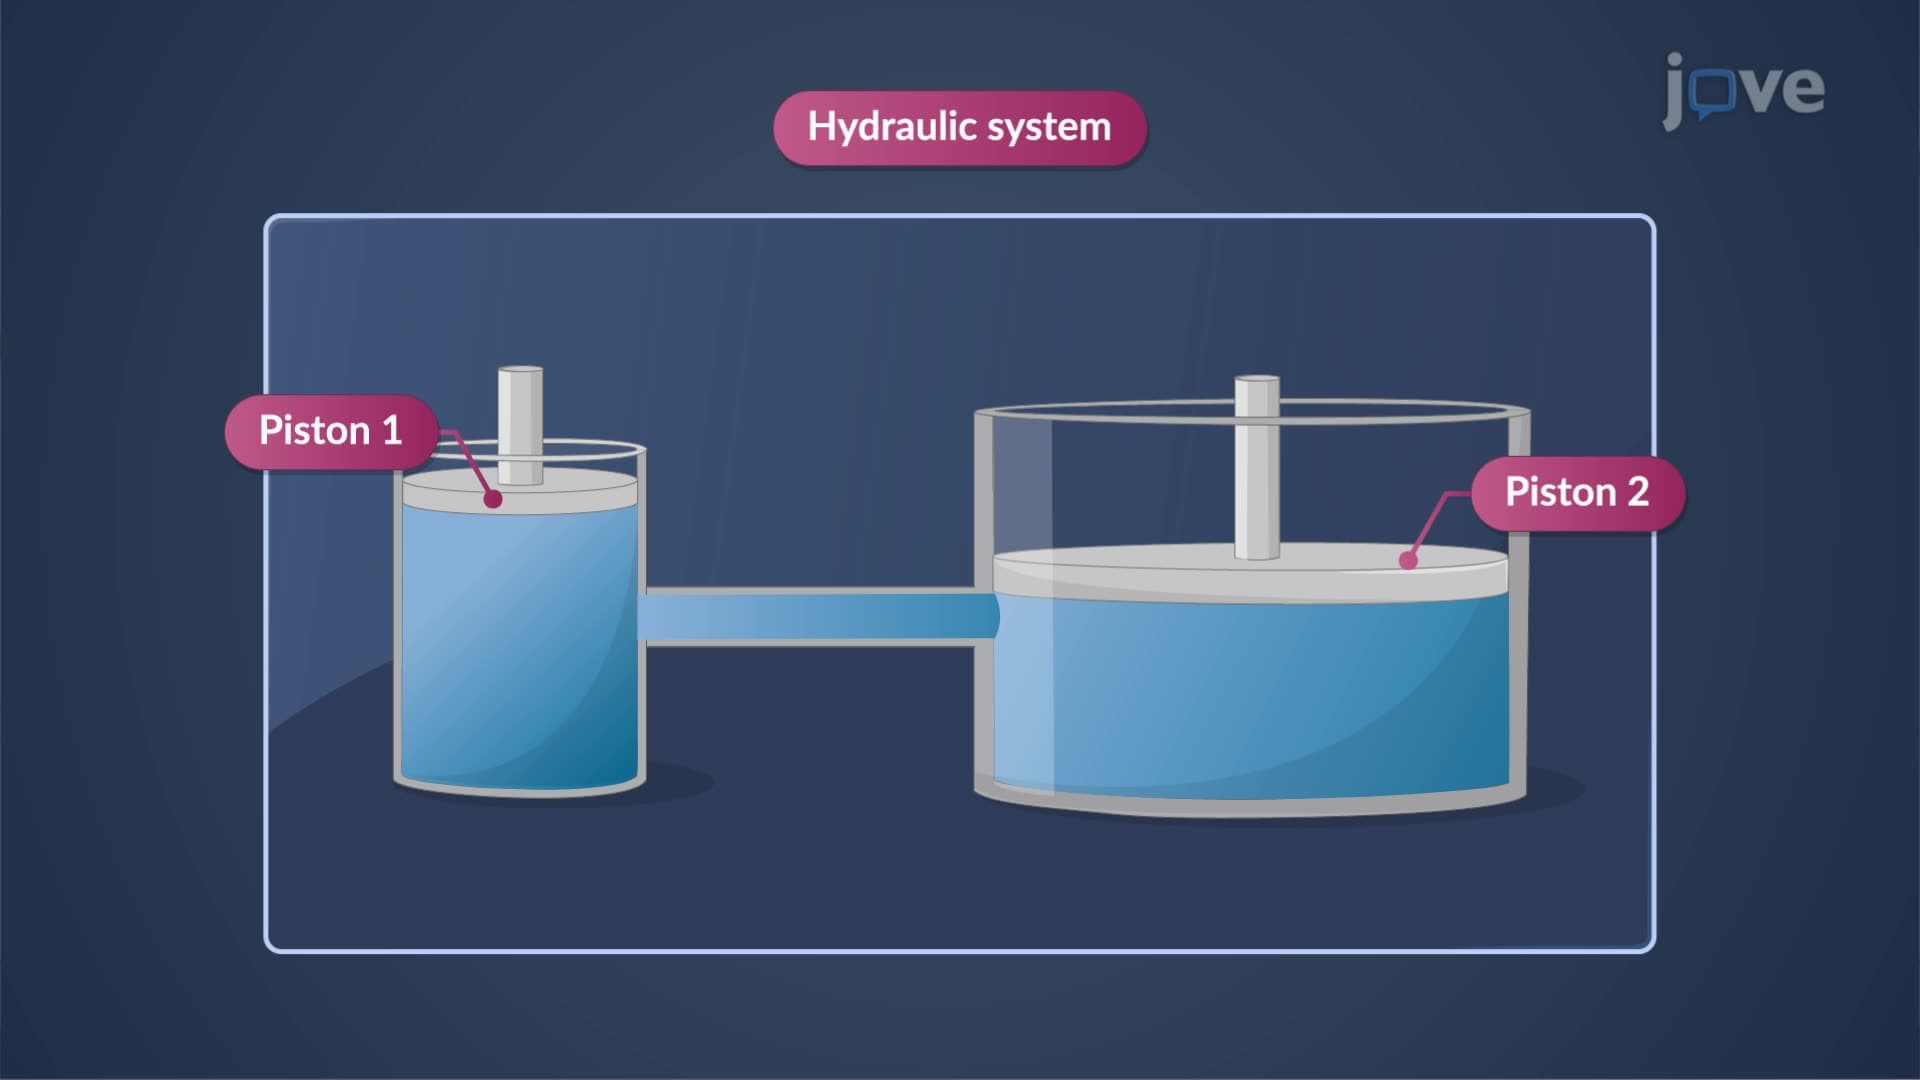
Density, Specific Weight, Specific Gravity and Compressibility of Fluid
Specific weight represents the weight per unit volume and is calculated by multiplying...