Related Experiment Video
Updated: Feb 5, 2026


Genetic Analysis of Hereditary Transthyretin Ala97Ser Related Amyloidosis
Published on: June 9, 2018
Intestinal involvement in amyloidosis is a sequential process
Marjanne den Braber-Ymker1, Sanneke Heijker2, Martin Lammens1,3,4
1Department of Pathology, Radboud University Medical Center, Nijmegen, The Netherlands.

Background:
Gastrointestinal amyloidosis causes dysmotility. A comprehensive histological analysis to explain these symptoms is lacking. Therefore, we systematically examined histological features of intestinal dysmotility in patients with AL and AA amyloidosis, compared to controls.
Methods:
Autopsy tissue material from small bowel and colon was used for histological (semiquantitative) evaluation of the mucosa, blood vessels, muscular layers, enteric nervous system (ENS) and the interstitial cells of Cajal (ICC), using hematoxylin and eosin, periodic acid Schiff, Elastic von Gieson and Congo red staining, and immunohistochemistry with α-smooth muscle actin, HuC/D, S100 and CD117 antibodies, according to guidelines of the Gastro 2009 International Working Group.
Key Results:
Amyloid deposits were present in the vascular walls of all amyloidosis patients. In the mucosa, amyloid was found in 67% of AA patients. The muscular layers were involved in 64% of amyloidosis patients, most prominent in AA patients, associated with the presence of polyglucosan inclusion bodies, but not with either abnormal α-actin patterns or fibrosis. Amyloid in the muscularis propria surrounding the myenteric plexus was found, but not inside the myenteric plexus. These deposits might be related to loss of the ICC network, but there was no association with decreased neuronal or nerve fiber density.
Conclusions & Inferences:
We hypothesize that intestinal dysmotility in amyloidosis patients is a sequential process: amyloid deposition starts in the vasculature, followed by involvement of the muscular layers, ICC loss, and potentially affect the myenteric plexus. This final stage may be accompanied by clinical symptoms of severe intestinal dysmotility.

Related Concept Videos
 01:23
Anatomy of the Intestines
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...
 01:26
Antigens Involved in Adaptive Immunity
Complete Antigens
Complete antigens possess both immunogenicity and...
 01:15
Small Intestine
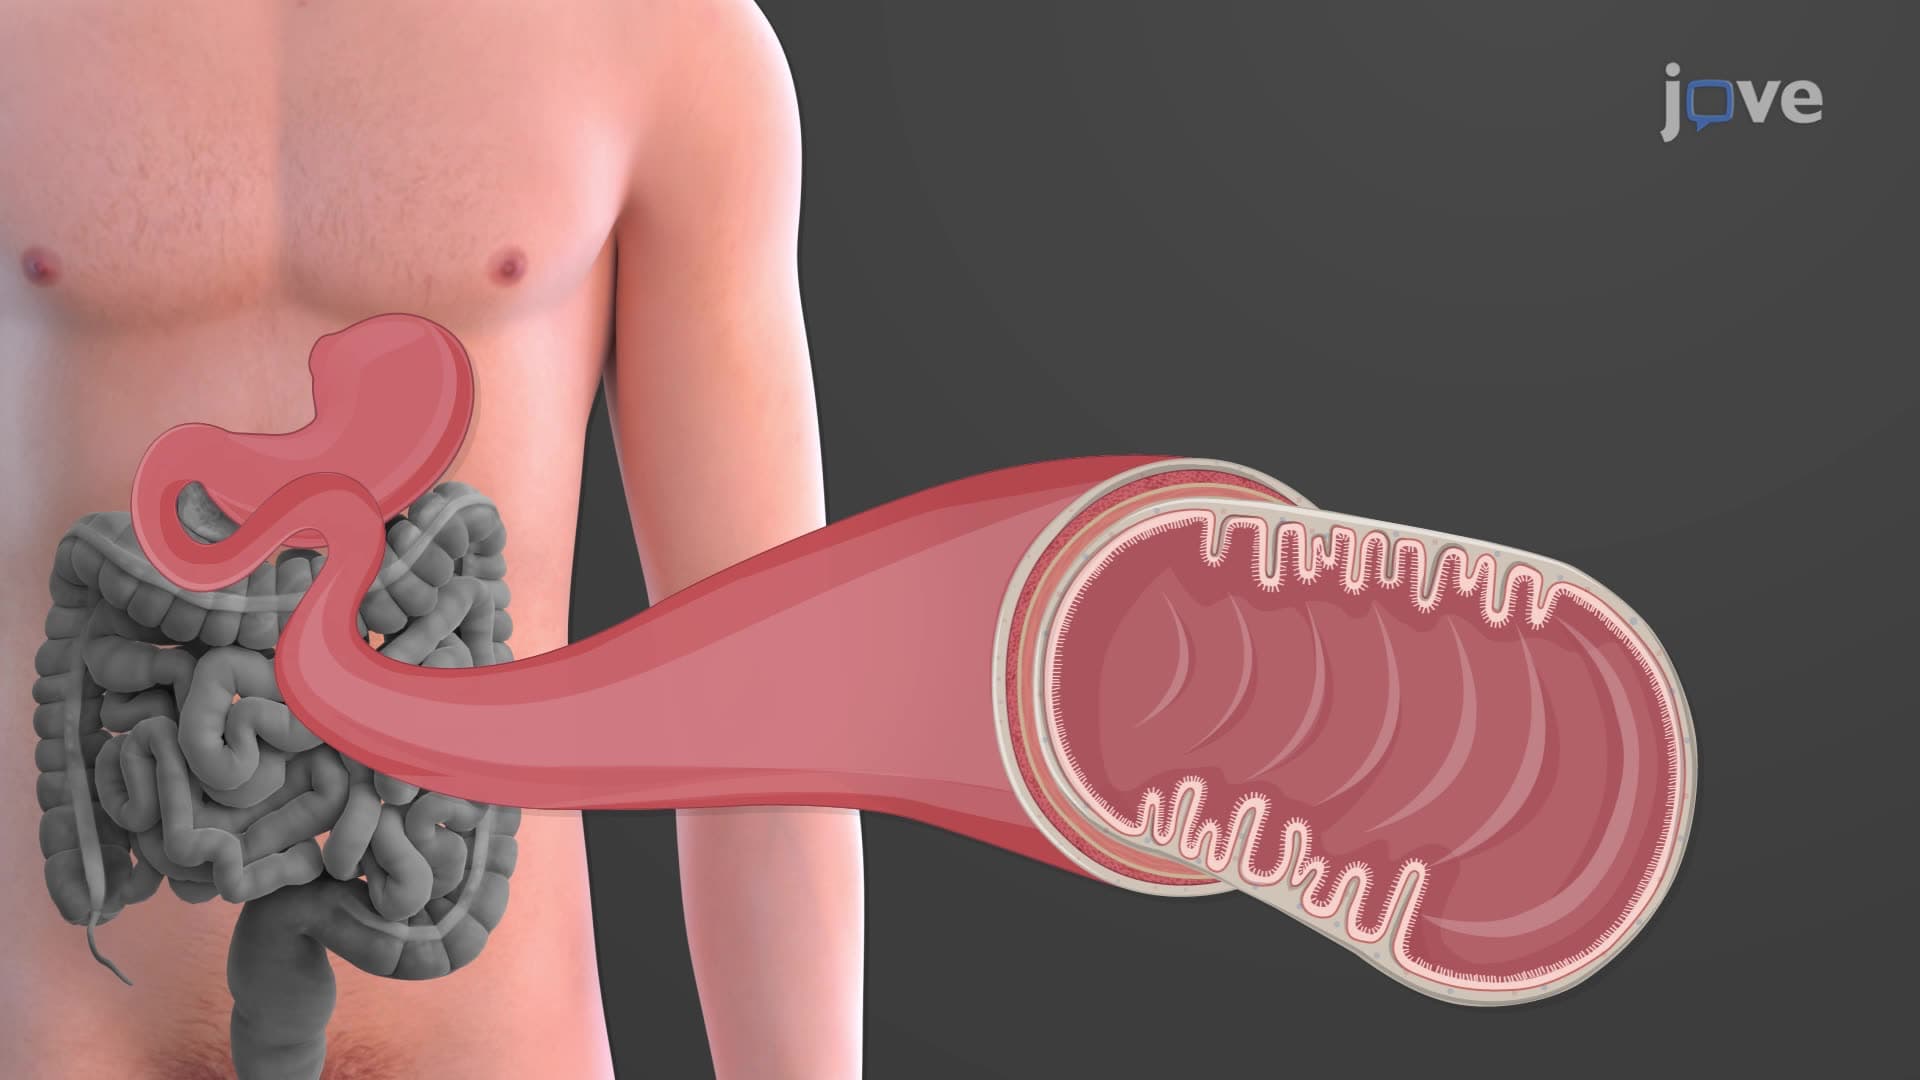
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique...
 01:09
Large Intestine
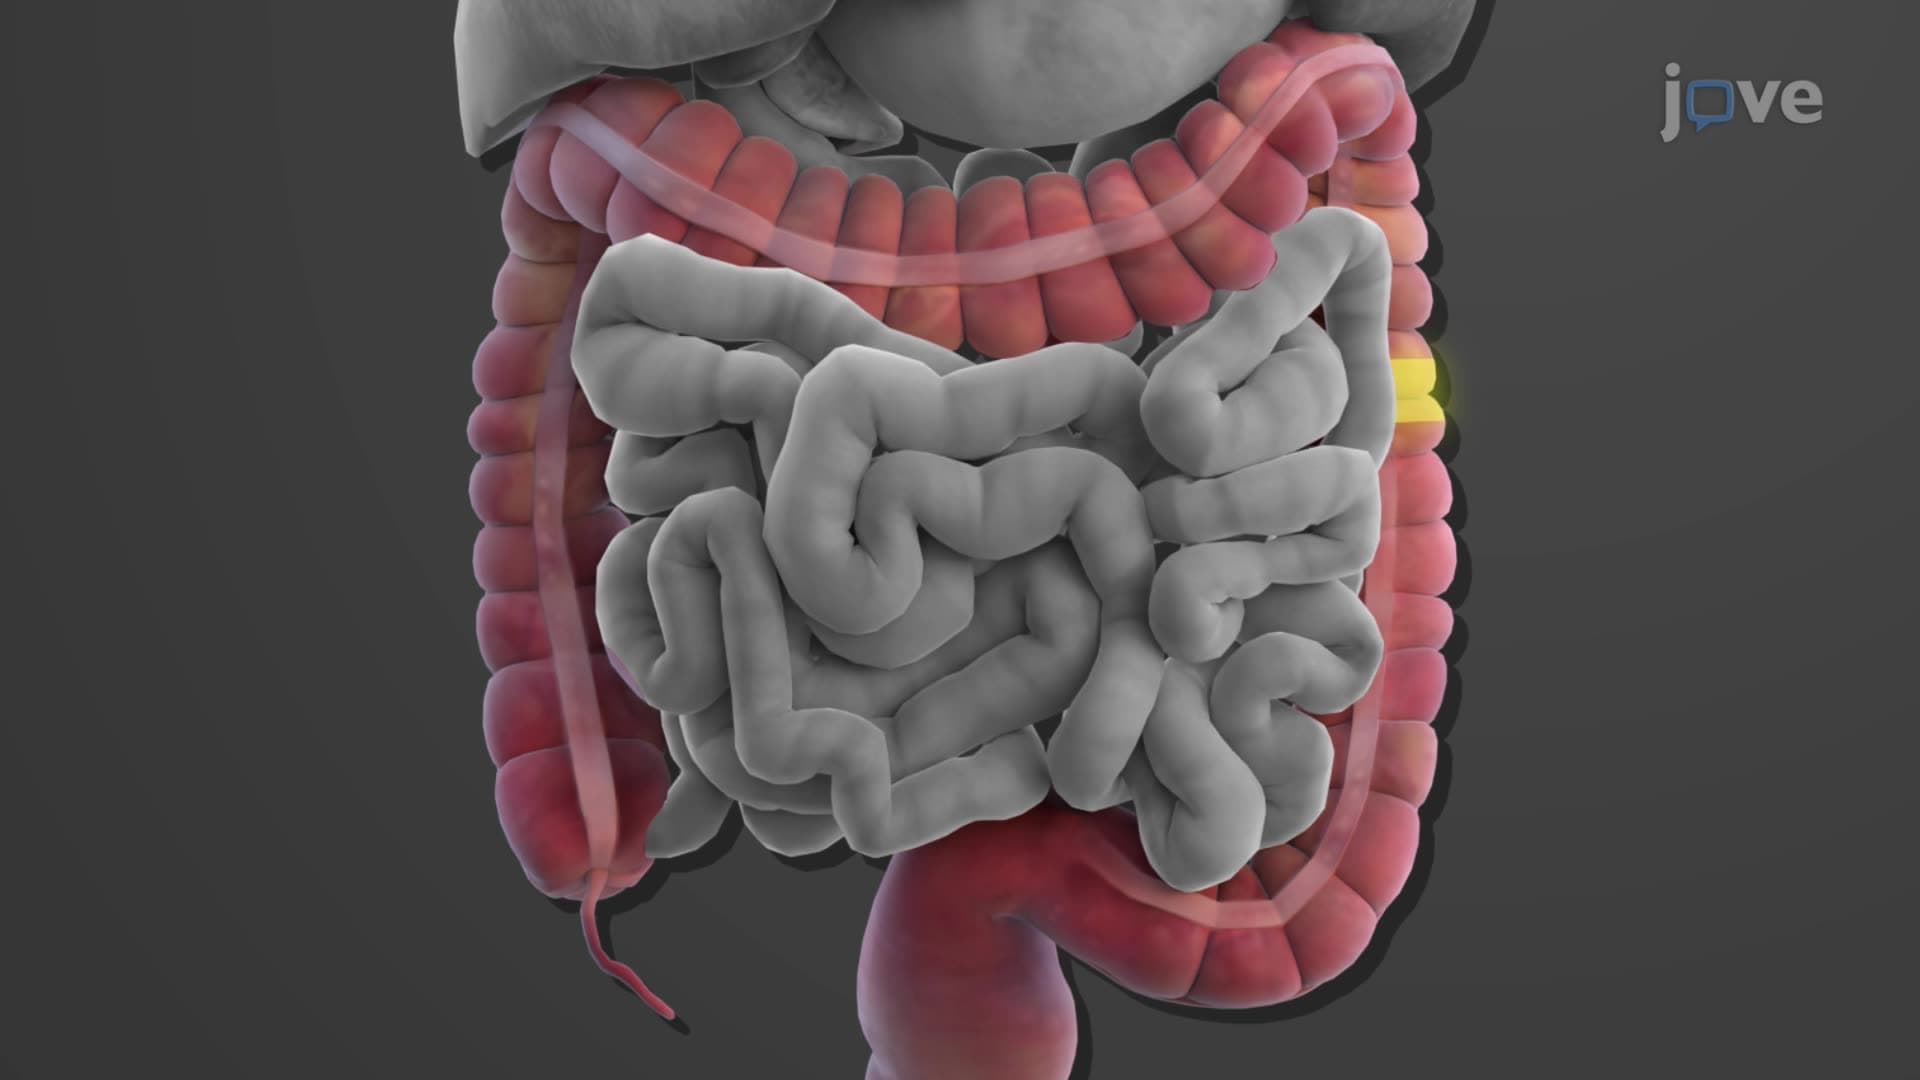
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:26
Histology of the Large Intestine
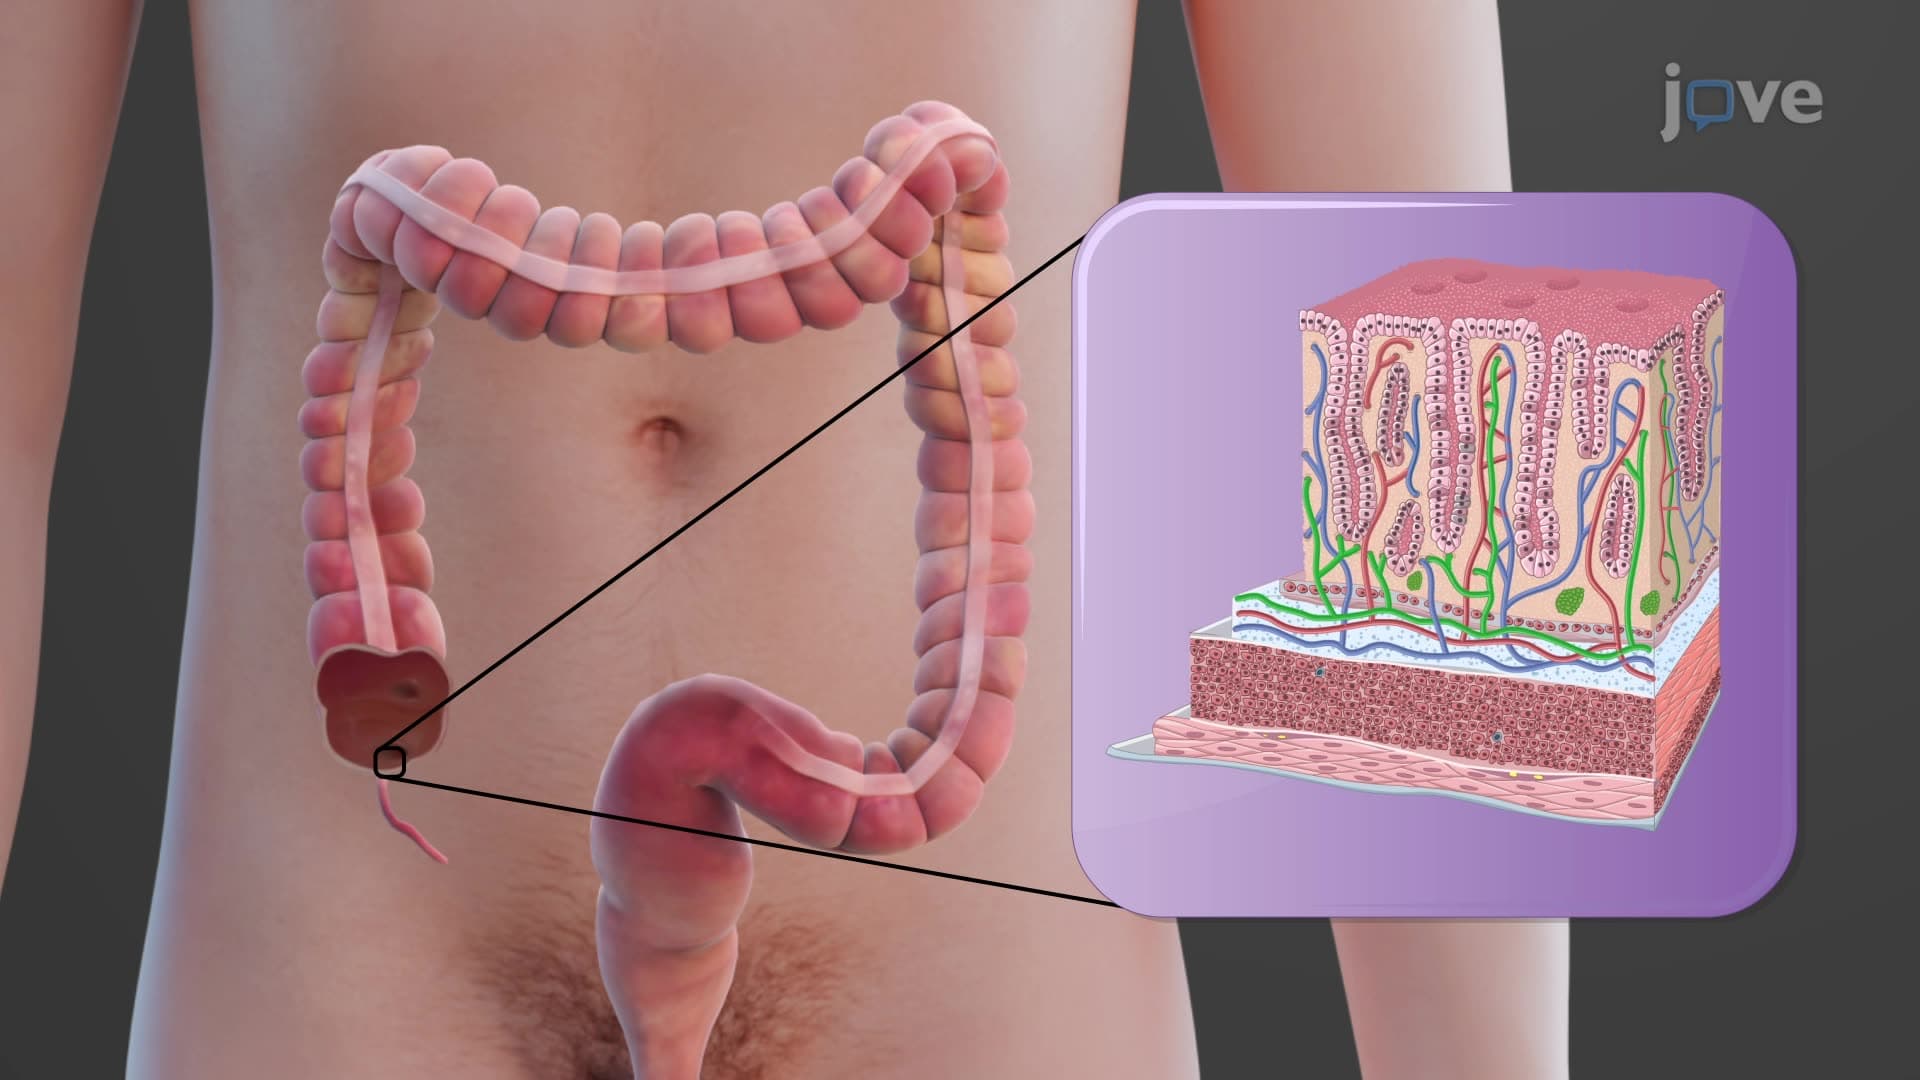
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
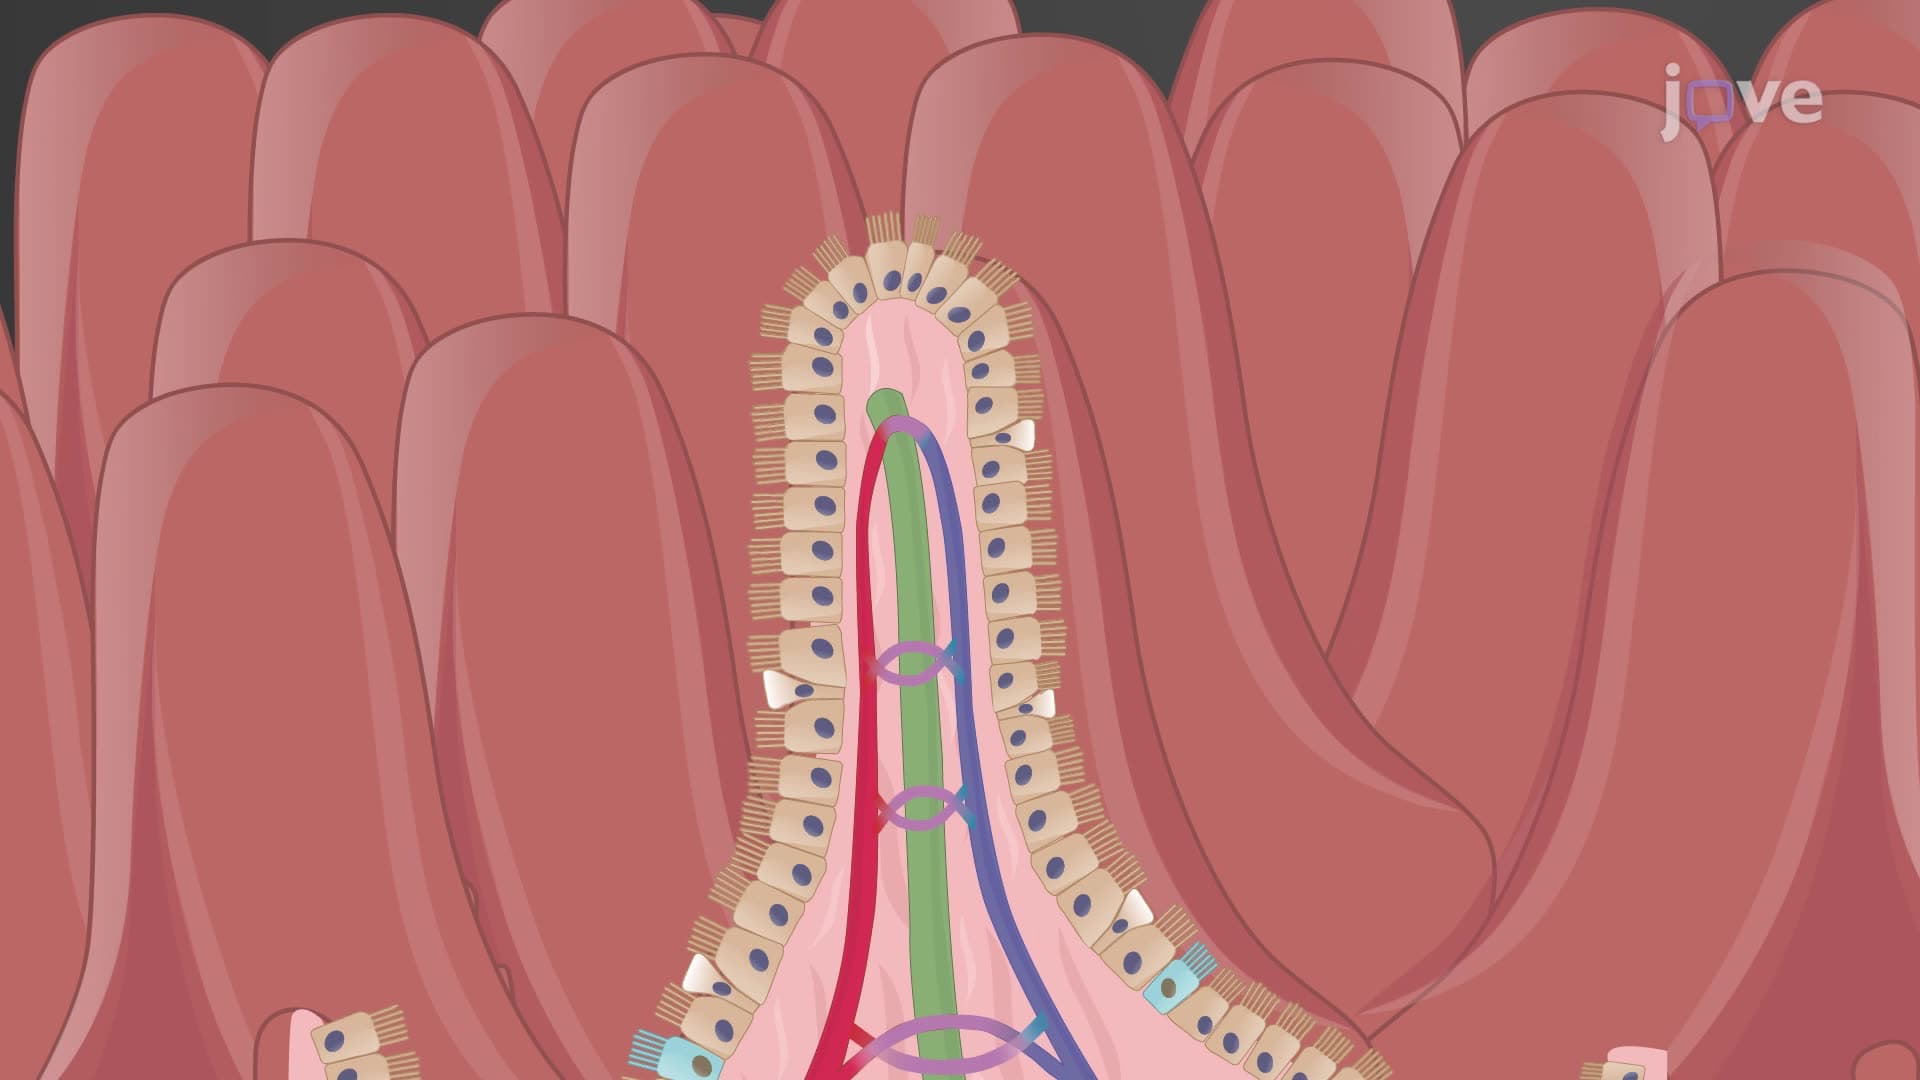 01:27
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...