Related Experiment Video
Updated: Feb 5, 2026
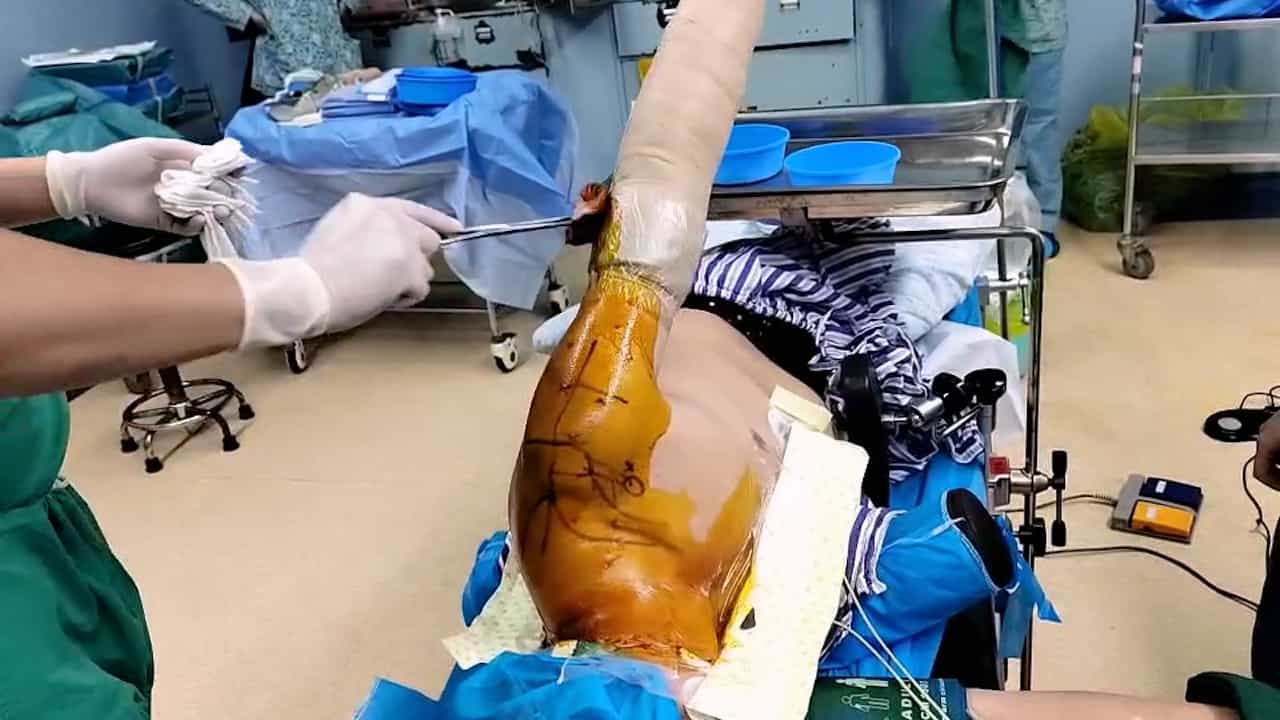

Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025
Arthroscopic Tenodesis of the Long Head of the Biceps Tendon
Yang-Soo Kim1, Jin-Young Jeong2, Hyo-Jin Lee1
1Department of Orthopaedic Surgery, Seoul St. Mary's Hospital, The Catholic University of Korea, Seoul, South Korea.

Abstract:
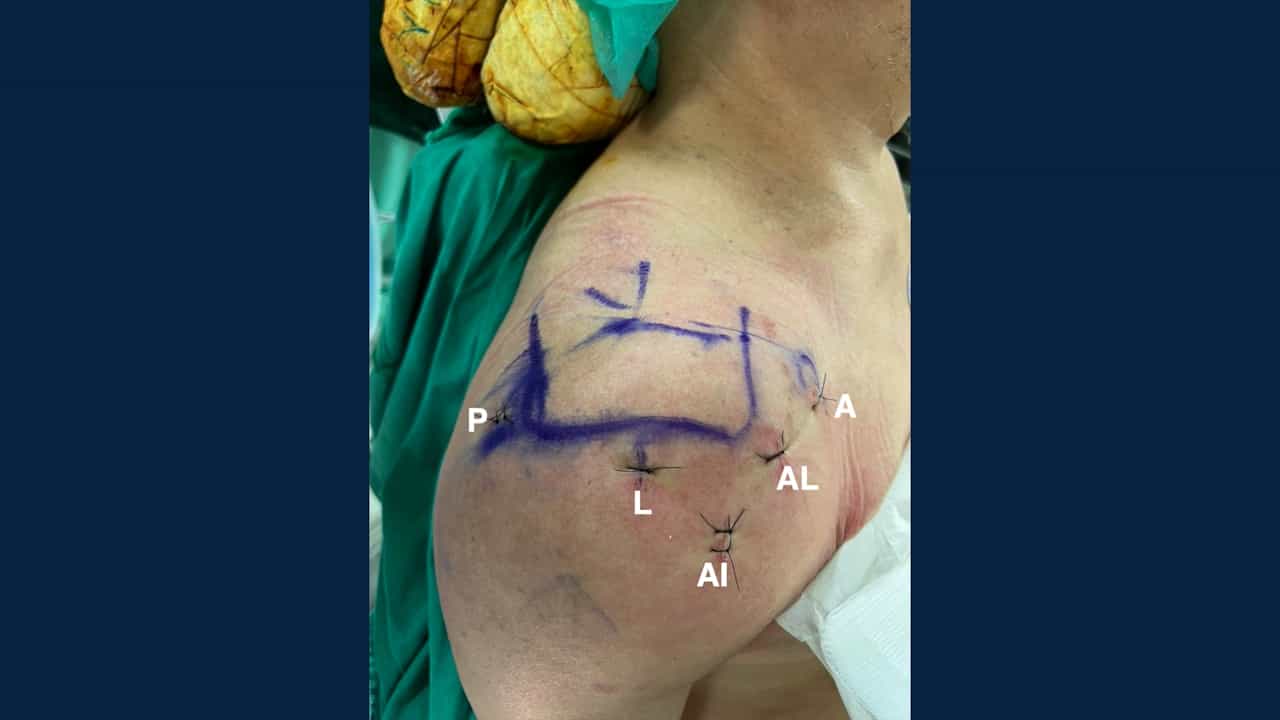
Lesions of the long head of the biceps brachii tendon (LHBT) are a common source of shoulder pain and dysfunction. Although the exact role of the LHBT in shoulder biomechanics is not clearly understood, pathological involvement of this tendon is a well-known pain generator and frequently the clinical presentation consists of both anterior pain and flexion loss. The initial treatment for lesions of the LHBT should be nonoperative, but if that fails or if the LHBT lesion is combined with rotator cuff lesions or other lesions that need to be repaired surgically, surgical intervention is indicated. Tenotomy and tenodesis of the LHBT are 2 classic representative treatments with confirmed results. Tenodesis may be especially beneficial for patients younger than 50 years old or those who perform strenuous labor. The procedure is performed arthroscopically with the following steps. Step 1: A standard posterior viewing portal and an anterior working portal are made. Step 2: After confirmation of the LHBT lesion inside the glenohumeral joint, number-1 polydioxanone (PDS) suture is passed through the tendon before tenotomy is performed just above the superior labrum. Step 3: The tenotomized tendon is pulled out through the anterior portal by gentle traction on the attached PDS suture. A Krackow whip-stitch with nonabsorbable suture is made in the tendon. Step 4: A 7 to 8-mm drill-hole is made in the intertubercular groove of the humeral head just proximal to the insertion of the subscapularis tendon. Step 5: The suture is tightly tied to the distal hole of a 7.0-mm BioComposite SwiveLock Interference Screw (Arthrex). Step 8: The interference screw with the tenotomized end is inserted into the drill-hole. LHBT tenodesis lessens the cosmetic problem of Popeye deformity that is seen after tenotomy. Also, elbow motor power including flexion and supination is preserved.
More Related Videos
Related Concept Videos
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:02
What is the Skeletal System?
 01:42
The Extracellular Matrix
 02:45
Valence Bond Theory