Related Experiment Video
Updated: Feb 5, 2026


A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
Reduced incidence of vein occlusion and postthrombotic syndrome after immediate compression for deep vein thrombosis
Elham E Amin1,2,3, Ingrid M Bistervels4,5, Karina Meijer6
1Department of Biochemistry, Cardiovascular Research Institute Maastricht, Maastricht University, Maastricht, The Netherlands.

Abstract:
Thus far, the association between residual vein occlusion and immediate compression therapy and postthrombotic syndrome is undetermined. Therefore, we investigated whether compression therapy immediately after diagnosis of deep vein thrombosis affects the occurrence of residual vein obstruction (RVO), and whether the presence of RVO is associated with postthrombotic syndrome and recurrent venous thromboembolism. In a prespecified substudy within the IDEAL (individualized duration of elastic compression therapy against long-term duration of therapy for prevention of postthrombotic syndrome) deep vein thrombosis (DVT) study, 592 adult patients from 10 academic and nonacademic centers across The Netherlands, with objectively confirmed proximal DVT of the leg, received no compression or acute compression within 24 hours of diagnosis of DVT with either multilayer bandaging or compression hosiery (pressure, 35 mm Hg). Presence of RVO and recurrent venous thromboembolism was confirmed with compression ultrasonography and incidence of postthrombotic syndrome as a Villalta score of at least 5 at 6 and 24 months. The average time from diagnosis until assessment of RVO was 5.3 (standard deviation, 1.9) months. A significantly lower percentage of patients who did receive compression therapy immediately after DVT had RVO (46.3% vs 66.7%; odds ratio, 0.46; 95% confidence interval, 0.27-0.80; P = .005). Postthrombotic syndrome was less prevalent in patients without RVO (46.0% vs 54.0%; odds ratio, 0.65; 95% confidence interval, 0.46-0.92; P = .013). Recurrent venous thrombosis showed no significant association with RVO. Immediate compression should therefore be offered to all patients with acute DVT of the leg, irrespective of severity of complaints. This study was registered at ClinicalTrials.gov (NCT01429714) and the Dutch Trial registry in November 2010 (NTR2597).

Related Concept Videos
 01:17
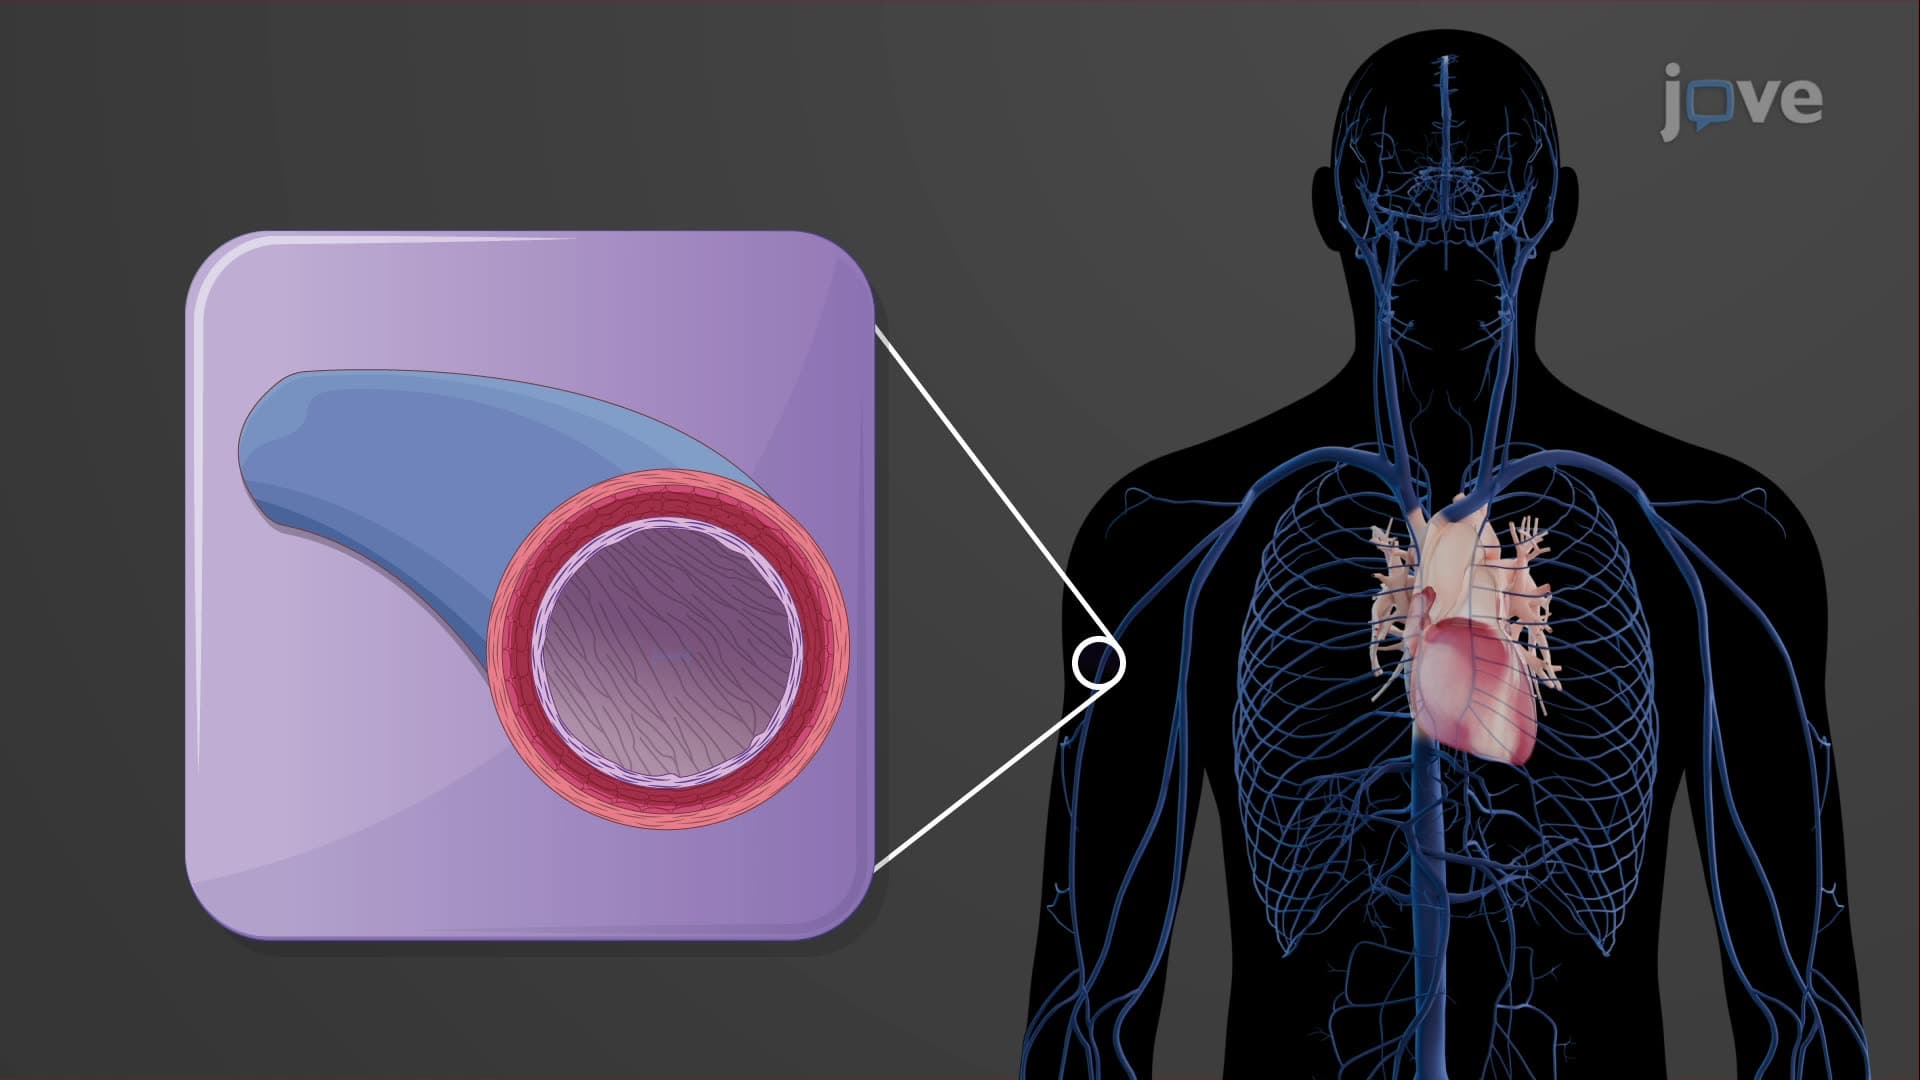
Veins
Structure of Veins:
The structure of veins is specifically designed to assist in the low-pressure transportation of...
 01:19
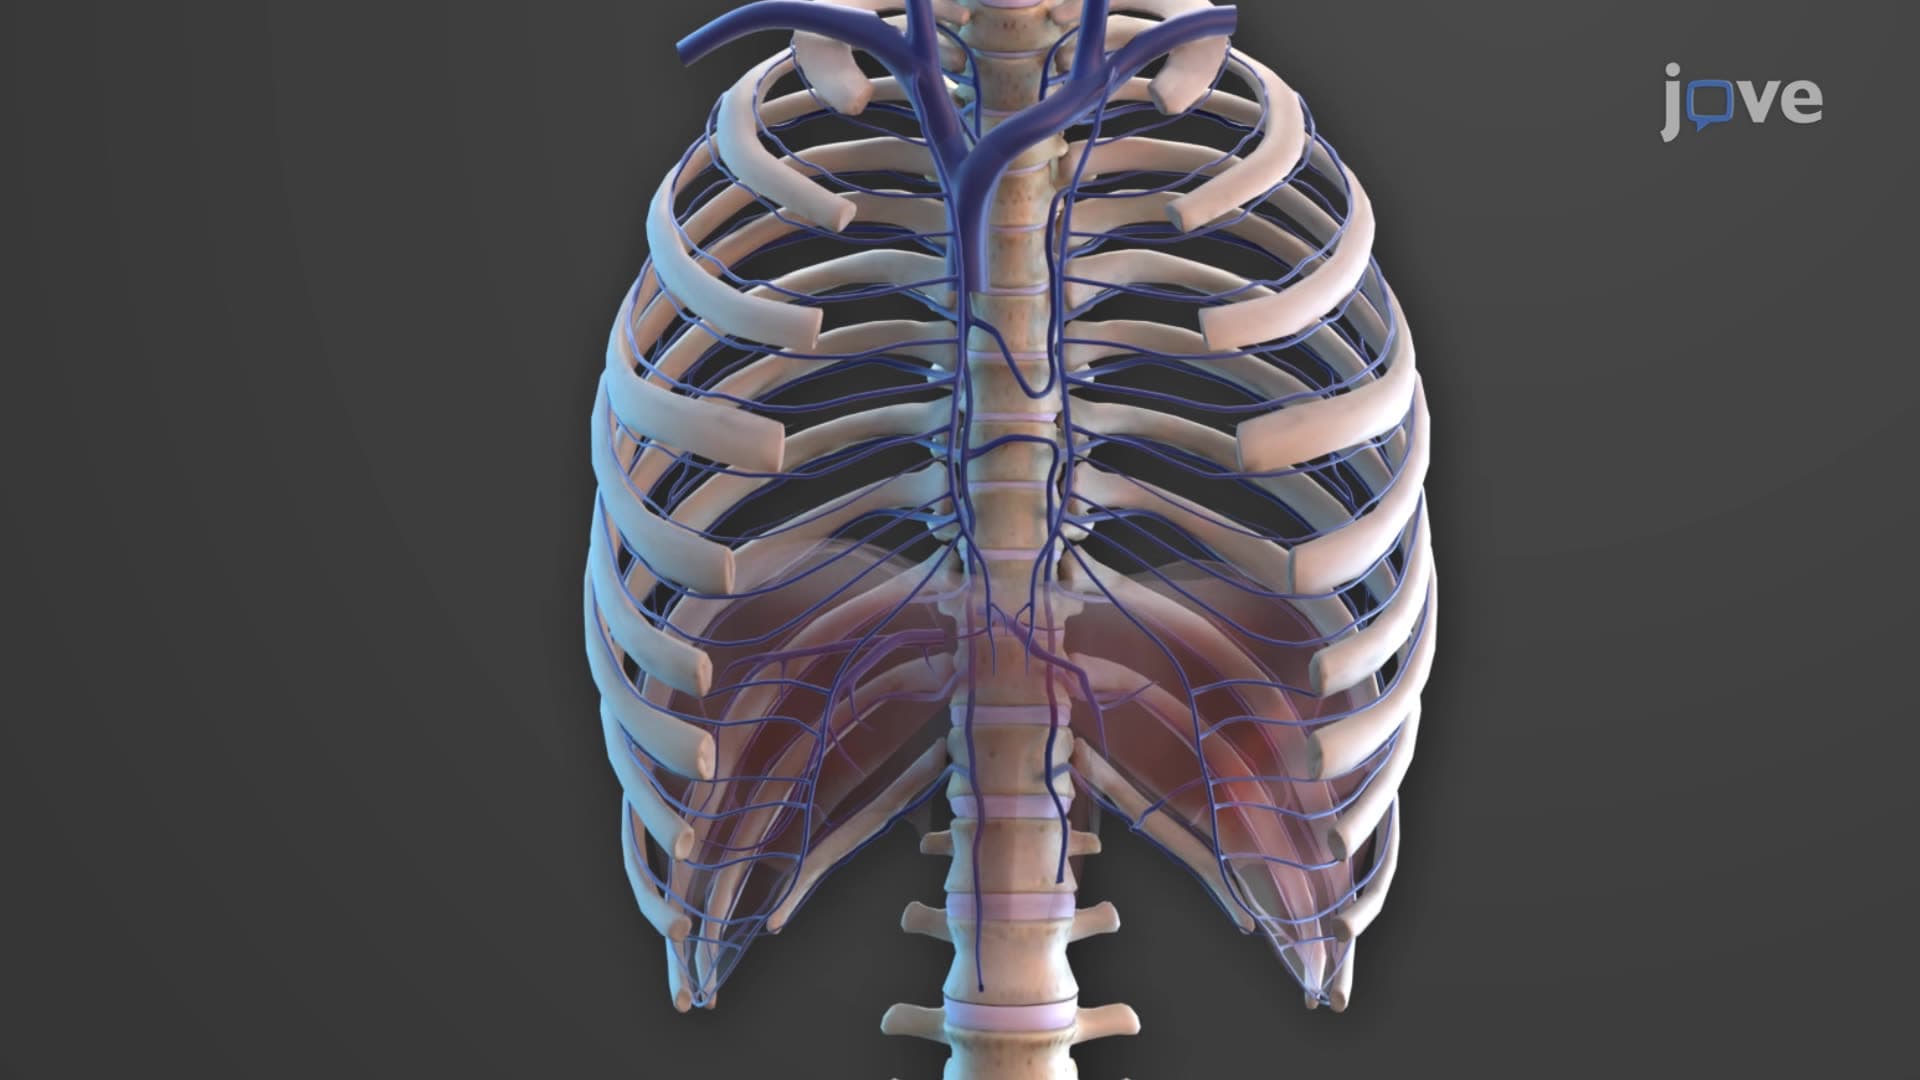
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:15
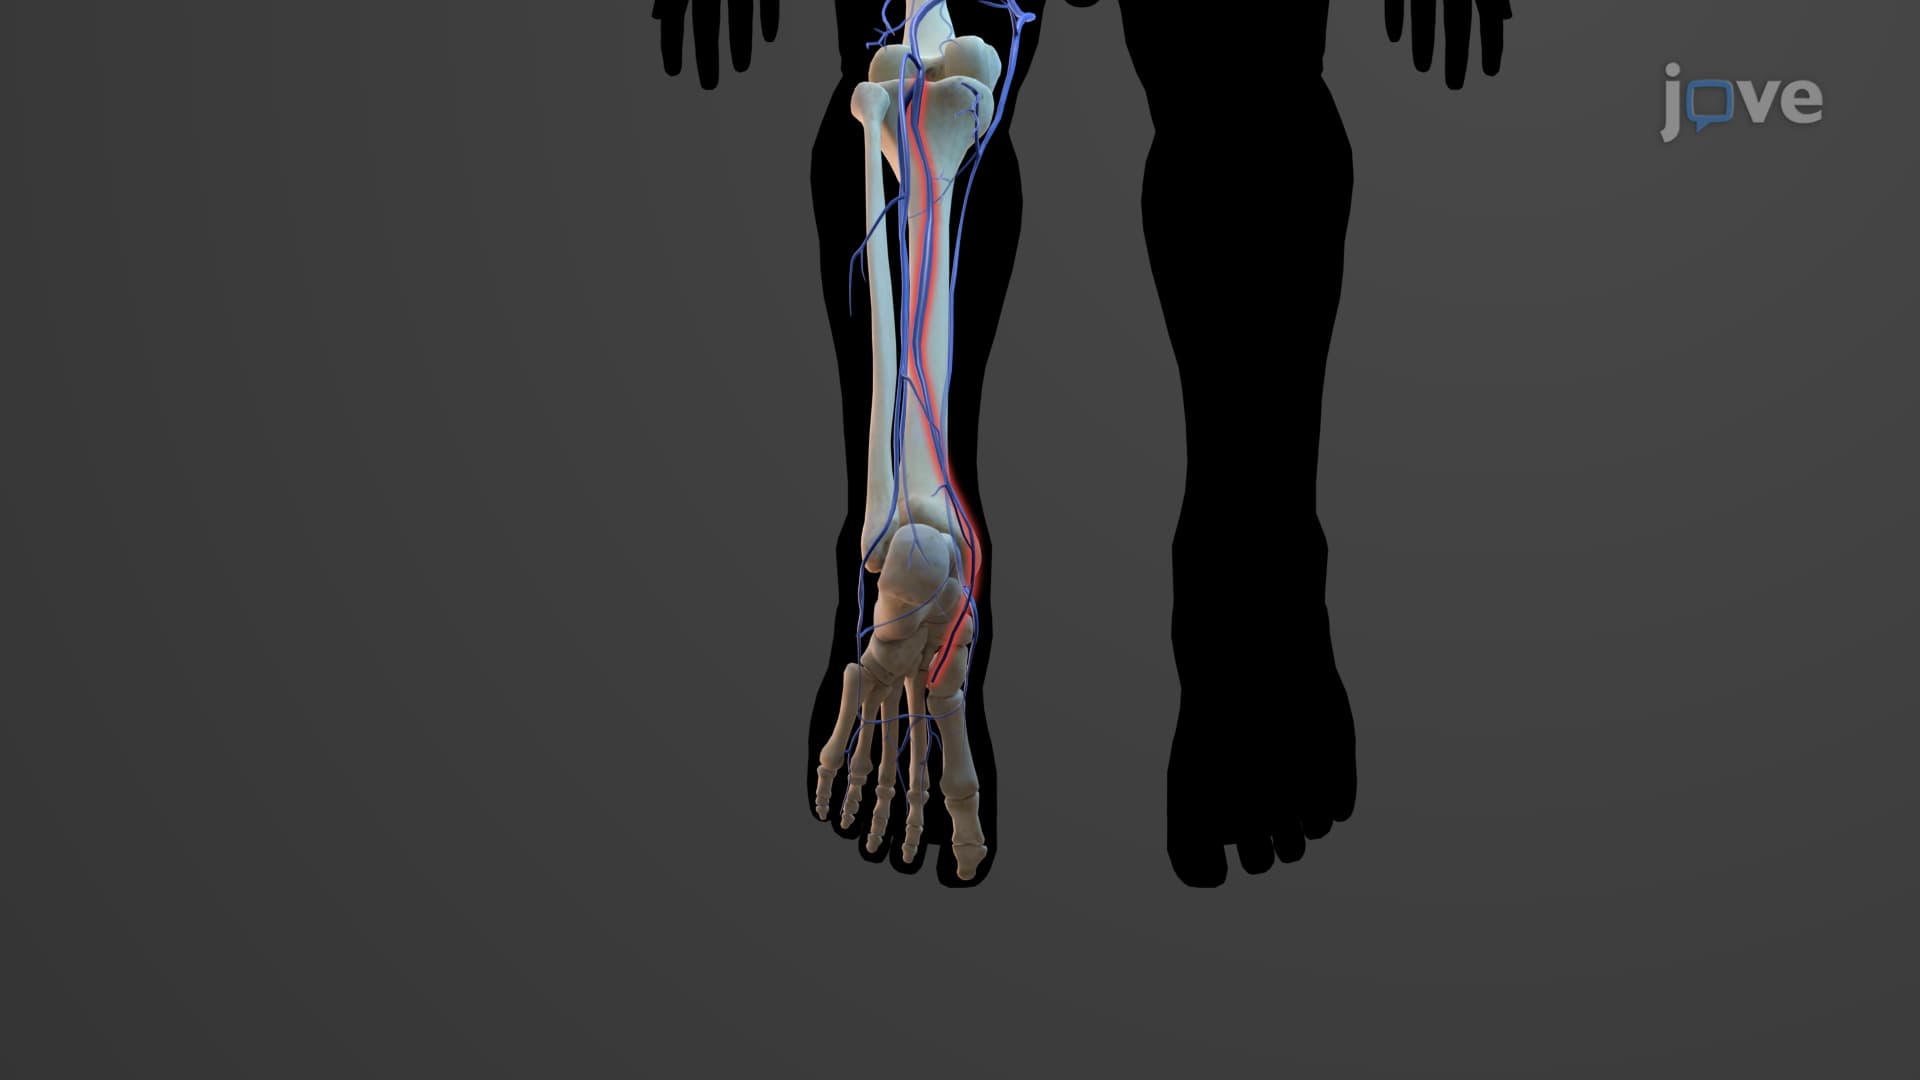
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...
 01:10
Veins as Blood Reservoirs
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...