Related Experiment Video
Updated: Feb 4, 2026
Transcatheter Pulmonary Valve Replacement from Autologous Pericardium with a Self-Expandable Nitinol Stent in an Adult Sheep Model
Published on: June 8, 2022
5-Year Outcomes of Self-Expanding Transcatheter Versus Surgical Aortic Valve Replacement in High-Risk Patients
Thomas G Gleason1, Michael J Reardon2, Jeffrey J Popma3
1Departments of Cardiothoracic Surgery and Cardiology, University of Pittsburgh Medical Center, Pittsburgh, Pennsylvania.

Insights
Transcatheter aortic valve replacement (TAVR) demonstrated similar 5-year survival and stroke rates compared to surgical aortic valve replacement (SAVR) in high-risk patients. Both procedures showed low rates of structural valve deterioration and reintervention.
Area of Science:
- Cardiovascular Medicine
- Interventional Cardiology
- Cardiac Surgery
Background:
- The CoreValve U.S. Pivotal High Risk Trial was the first randomized trial to establish transcatheter aortic valve replacement (TAVR) superiority in 1-year mortality over surgical aortic valve replacement (SAVR) for high-risk patients.
- Mid-term outcomes for TAVR versus SAVR in this population were previously less defined.
Purpose of the Study:
- To compare the safety, performance, and durability of TAVR versus SAVR at a mid-term 5-year follow-up.
- To evaluate long-term clinical and valve-related outcomes in high-risk patients undergoing aortic valve replacement.
Main Methods:
- A randomized controlled trial comparing TAVR with a self-expanding bioprosthesis to SAVR in high-risk surgical patients.
- Follow-up was conducted for 5 years, with outcomes assessed using Valve Academic Research Consortium I (VARC-1) definitions.
- Severe structural valve deterioration was defined by specific hemodynamic criteria (mean gradient ≥40 mm Hg or change ≥20 mm Hg) or new severe aortic regurgitation.
Main Results:
- At 5 years, all-cause mortality was similar between TAVR (55.3%) and SAVR (55.4%).
- Major stroke rates were comparable: 12.3% for TAVR and 13.2% for SAVR.
- Freedom from severe structural valve deterioration was high for both TAVR (99.2%) and SAVR (98.3%), with significantly lower rates of valve reintervention for TAVR (97.0%) compared to SAVR (98.9%).
- Permanent pacemaker implantation was more frequent after TAVR (33.0%) than SAVR (19.8%).
Conclusions:
- Transcatheter aortic valve replacement (TAVR) and surgical aortic valve replacement (SAVR) show similar mid-term survival and stroke rates in high-risk patients.
- Severe structural valve deterioration and the need for valve reintervention are infrequent with both TAVR and SAVR at 5 years.
- The findings support TAVR as a viable option for high-risk patients needing aortic valve replacement, with considerations for pacemaker implantation rates.
Background:
The CoreValve U.S. Pivotal High Risk Trial was the first randomized trial to show superior 1-year mortality of transcatheter aortic valve replacement (TAVR) compared with surgical aortic valve replacement (SAVR) among high operative mortality-risk patients.
Objectives:
The authors sought to compare TAVR to SAVR for mid-term 5-year outcomes of safety, performance, and durability.
Methods:
Surgical high-risk patients were randomized (1:1) to TAVR with the self-expanding bioprosthesis or SAVR. VARC-1 (Valve Academic Research Consortium I) definitions were applied. Severe hemodynamic structural valve deterioration was defined as a mean gradient ≥40 mm Hg or a change in gradient ≥20 mm Hg or new severe aortic regurgitation. Five-year follow-up was planned.
Results:
A total of 797 patients were randomized at 45 U.S. centers, of whom 750 underwent an attempted implant (TAVR = 391, SAVR = 359). The overall mean age was 83 years, and the STS score was 7.4%. All-cause mortality rates at 5 years were 55.3% for TAVR and 55.4% for SAVR. Subgroup analysis showed no differences in mortality. Major stroke rates were 12.3% for TAVR and 13.2% for SAVR. Mean aortic valve gradients were 7.1 ± 3.6 mm Hg for TAVR and 10.9 ± 5.7 mm Hg for SAVR. No clinically significant valve thrombosis was observed. Freedom from severe SVD was 99.2% for TAVR and 98.3% for SAVR (p = 0.32), and freedom from valve reintervention was 97.0% for TAVR and 98.9% for SAVR (p = 0.04). A permanent pacemaker was implanted in 33.0% of TAVR and 19.8% of SAVR patients at 5 years.
Conclusions:
This study shows similar mid-term survival and stroke rates in high-risk patients following TAVR or SAVR. Severe structural valve deterioration and valve reinterventions were uncommon. (Safety and Efficacy Study of the Medtronic CoreValve® System in the Treatment of Symptomatic Severe Aortic Stenosis in High Risk and Very High Risk Subjects Who Need Aortic Valve Replacement; NCT01240902).


Related Concept Videos
 01:04
5-Number Summary
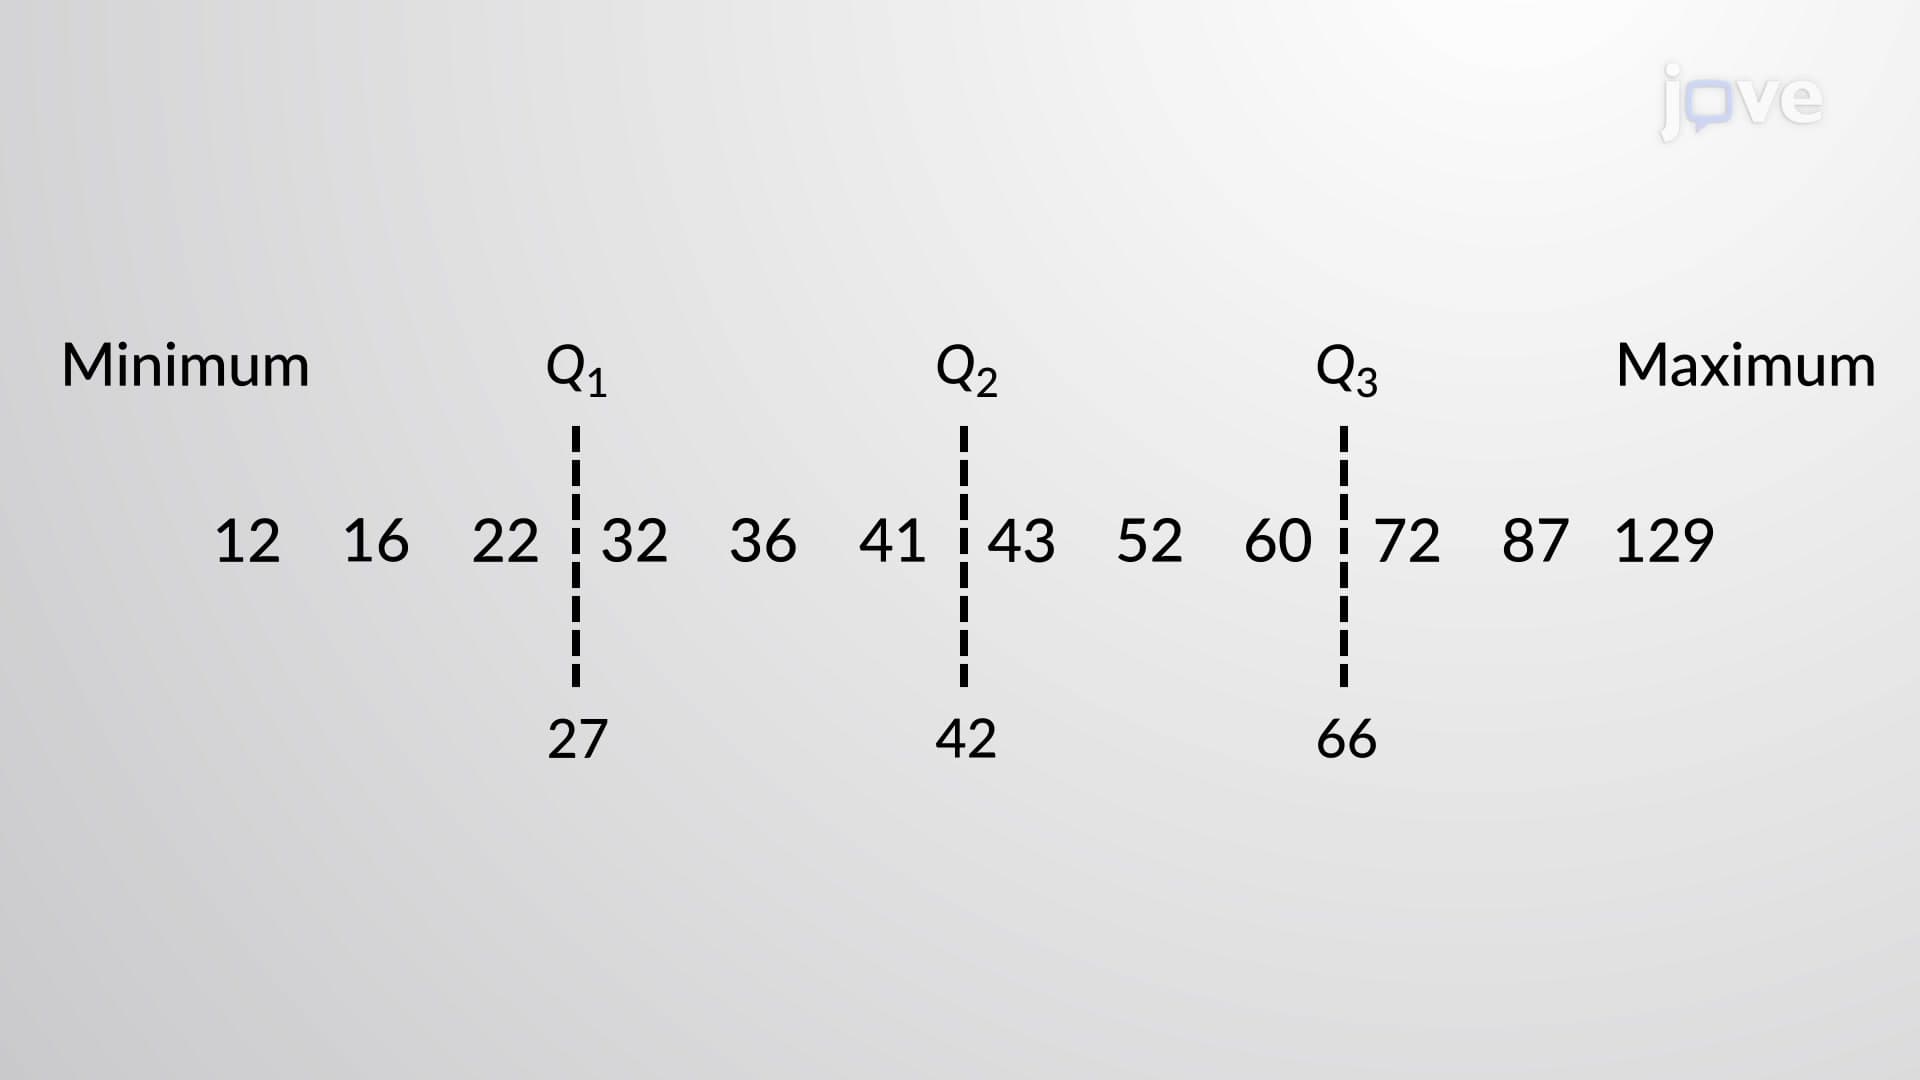
In a box plot, the minimum and maximum data values represent the lower and upper whiskers in the graph, and the median is designated as the center of the box in the chart. The first quartile and third...
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...
 02:24
Predicting Reaction Outcomes
 01:12
Relative Risk
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 01:30
Continuous Renal Replacement Therapy