Related Experiment Video
Updated: Feb 4, 2026


Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
The Virtual Hospitalist: A Single-Site Implementation Bringing Hospitalist Coverage to Critical Access Hospitals
Ethan F Kuperman1, Eric L Linson2, Kate Klefstad3
1University of Iowa Carver College of Medicine, Iowa City, Iowa, USA. ethan-kuperman@uiowa.edu.

Background:
On-site hospitalist care can improve patient care, but it is economically infeasible for small critical access hospitals (CAHs). A telemedicine "virtual hospitalist" may expand CAH capabilities at a fractional cost of an on"site provider.
Objective:
To evaluate the impact of a virtual hospitalist on transfers from a CAH to outside hospitals.
Design, Setting, Patients:
A 6-month pilot program providing "virtual hospitalist" coverage to patients at a CAH in rural Iowa.
Measurements:
The primary outcome was the rate of outside transfers from the CAH Emergency Department (ED). The secondary outcomes included transfer from either the ED or the inpatient wards, daily census, length of stay, transfers after admission, virtual hospitalist time commitment, and patient and staff satisfaction. The preceding 24-week baseline was compared with 24 weeks after implementation, excluding a 2-week transition period.
Results:
At baseline, there were 947 ED visits and 176 combined inpatient and observation encounters, compared to 930 and 176 after implementation, respectively. Outside transfers from the ED decreased from 16.6% to 10.5% (157/947 to 98/930, P < .001), and transfers at any time decreased from 17.3% to 11.9% (164/947 to 111/930, P < .001). Daily census, length of stay, and transfers after admission were unchanged. Time commitment for a virtual hospitalist was 35 minutes per patient per day. The intervention was well received by the CAH staff and patients.
Conclusions:
The virtual hospitalist model increased the percentage of ED patients who could safely receive their care locally. A single virtual hospitalist may be able to cover multiple CAHs simultaneously.
Funding:
Development of this project was funded through the University of Iowa Hospitalist group and the Signal Center for Health Innovations at UI Health Ventures. Virtual hospitalist clinical time was paid for by the CAH on a fractional basis of a traditional hospitalist based on projected patient volumes through analysis of baseline data. Patients were not directly billed for virtual hospitalist service but were charged for the services provided by CAH providers.


Related Concept Videos
 00:59
Hospitals-II
Nurses that work in...
 01:28
Hospitals-I
 01:20
Virtual Work
In static equilibrium, a body can experience an imaginary or virtual movement, such as displacement or rotation. The virtual work done by a force is equal to the dot product of force and virtual displacement in the direction of the force. When it comes to virtually rotating a...
 01:15
Nursing Implementation
The five steps to implementing effective nursing care include reassessing the patient, reviewing and revising the existing nursing care plan, organizing the resources and care delivery, anticipating and preventing complications, and implementing nursing interventions.
 01:16
Critical Region, Critical Values and Significance Level
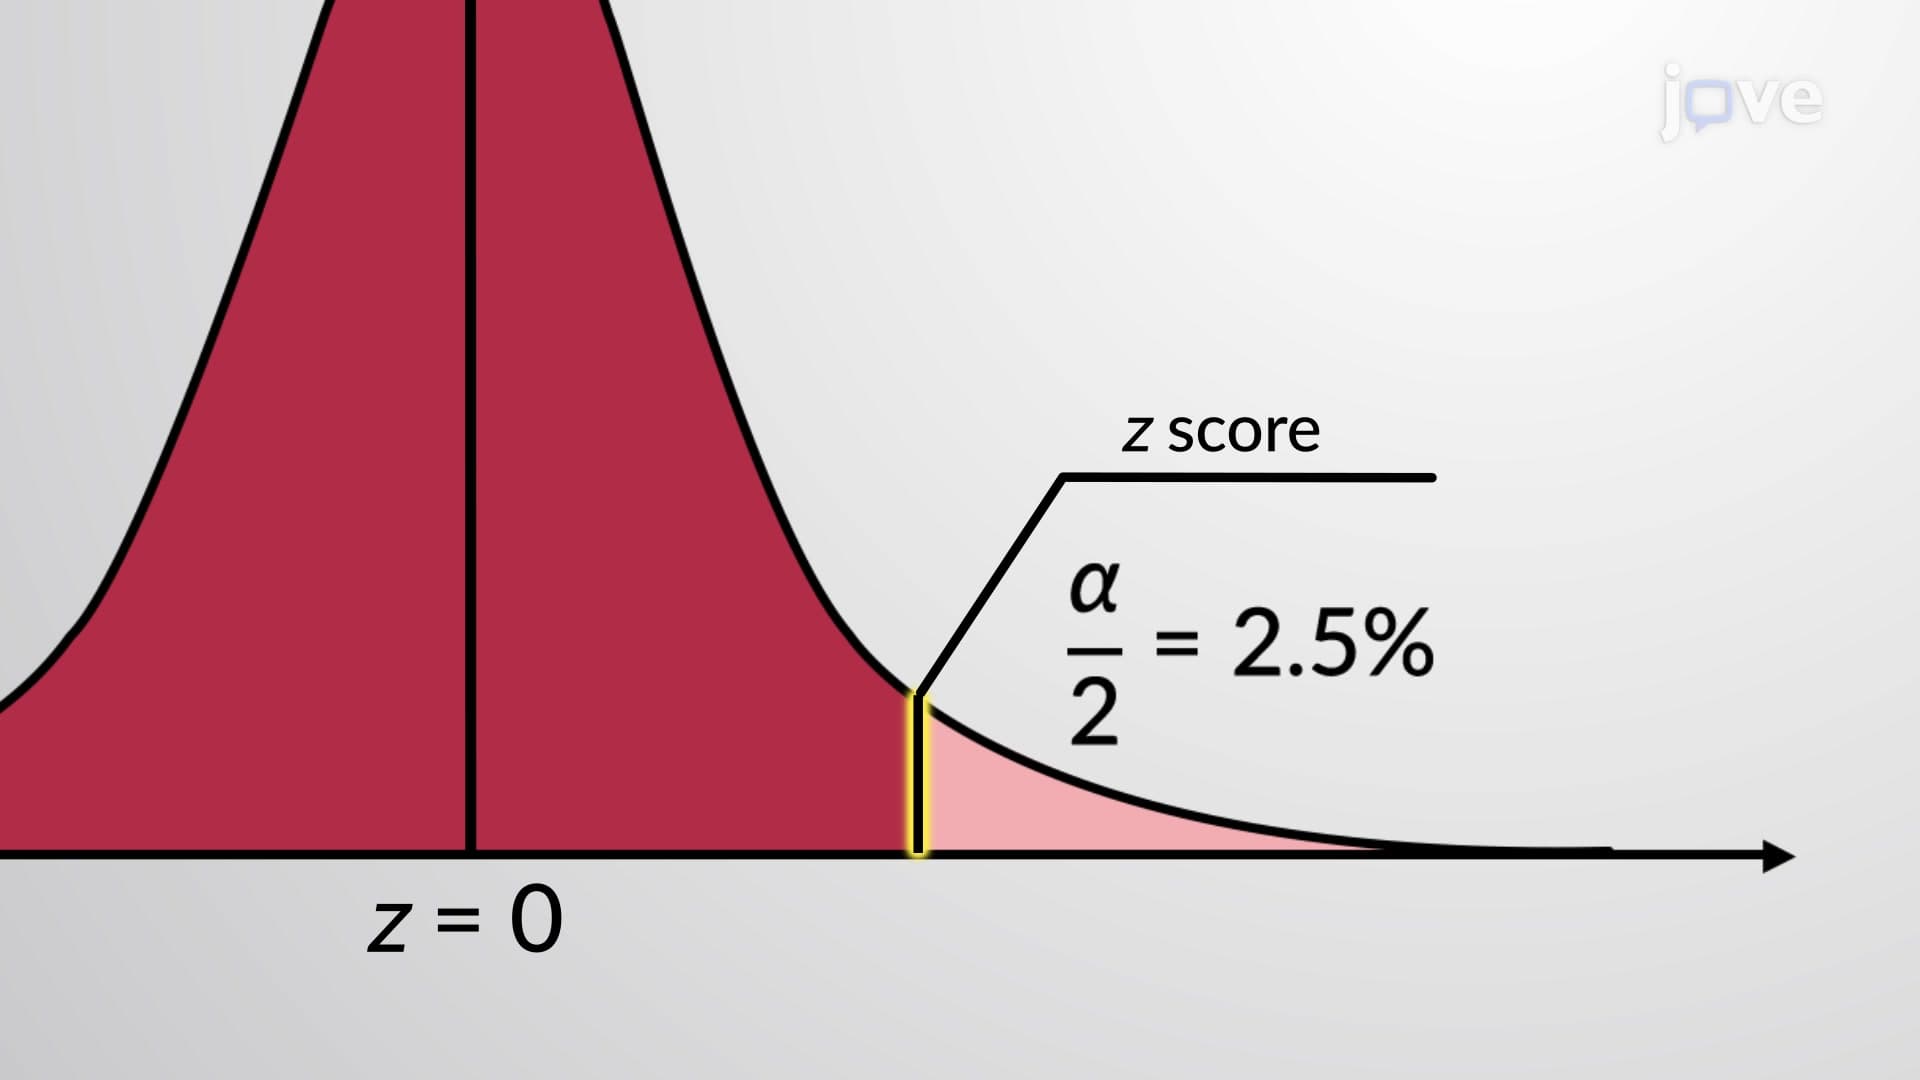
In hypothesis testing, a sample statistic is converted to a test statistic using z, t, or chi-square distribution. A critical region is an area under the curve in probability distributions demarcated by the critical value. When the test statistic falls in this region, it suggests that the null hypothesis must be rejected. As this region contains all those values of the...
 01:31
Critical Values