Related Experiment Video
Updated: Feb 4, 2026

Mechanical Ventilation Boot Camp Curriculum
Published on: March 12, 2018
Estimation of the diaphragm neuromuscular efficiency index in mechanically ventilated critically ill patients
Diana Jansen1, Annemijn H Jonkman2, Lisanne Roesthuis3
1Department of Anesthesiology, Radboud University Medical Center, Nijmegen, The Netherlands.

Background:
Diaphragm dysfunction develops frequently in ventilated intensive care unit (ICU) patients. Both disuse atrophy (ventilator over-assist) and high respiratory muscle effort (ventilator under-assist) seem to be involved. A strong rationale exists to monitor diaphragm effort and titrate support to maintain respiratory muscle activity within physiological limits. Diaphragm electromyography is used to quantify breathing effort and has been correlated with transdiaphragmatic pressure and esophageal pressure. The neuromuscular efficiency index (NME) can be used to estimate inspiratory effort, however its repeatability has not been investigated yet. Our goal is to evaluate NME repeatability during an end-expiratory occlusion (NMEoccl) and its use to estimate the pressure generated by the inspiratory muscles (Pmus).
Methods:
This is a prospective cohort study, performed in a medical-surgical ICU. A total of 31 adult patients were included, all ventilated in neurally adjusted ventilator assist (NAVA) mode with an electrical activity of the diaphragm (EAdi) catheter in situ. At four time points within 72 h five repeated end-expiratory occlusion maneuvers were performed. NMEoccl was calculated by delta airway pressure (ΔPaw)/ΔEAdi and was used to estimate Pmus. The repeatability coefficient (RC) was calculated to investigate the NMEoccl variability.
Results:
A total number of 459 maneuvers were obtained. At time T = 0 mean NMEoccl was 1.22 ± 0.86 cmH2O/μV with a RC of 82.6%. This implies that when NMEoccl is 1.22 cmH2O/μV, it is expected with a probability of 95% that the subsequent measured NMEoccl will be between 2.22 and 0.22 cmH2O/μV. Additional EAdi waveform analysis to correct for non-physiological appearing waveforms, did not improve NMEoccl variability. Selecting three out of five occlusions with the lowest variability reduced the RC to 29.8%.
Conclusions:
Repeated measurements of NMEoccl exhibit high variability, limiting the ability of a single NMEoccl maneuver to estimate neuromuscular efficiency and therefore the pressure generated by the inspiratory muscles based on EAdi.

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:14
Mechanical Efficiency of Real Machines
However, in reality, no machine can be truly ideal, and all of them experience some...
 01:17
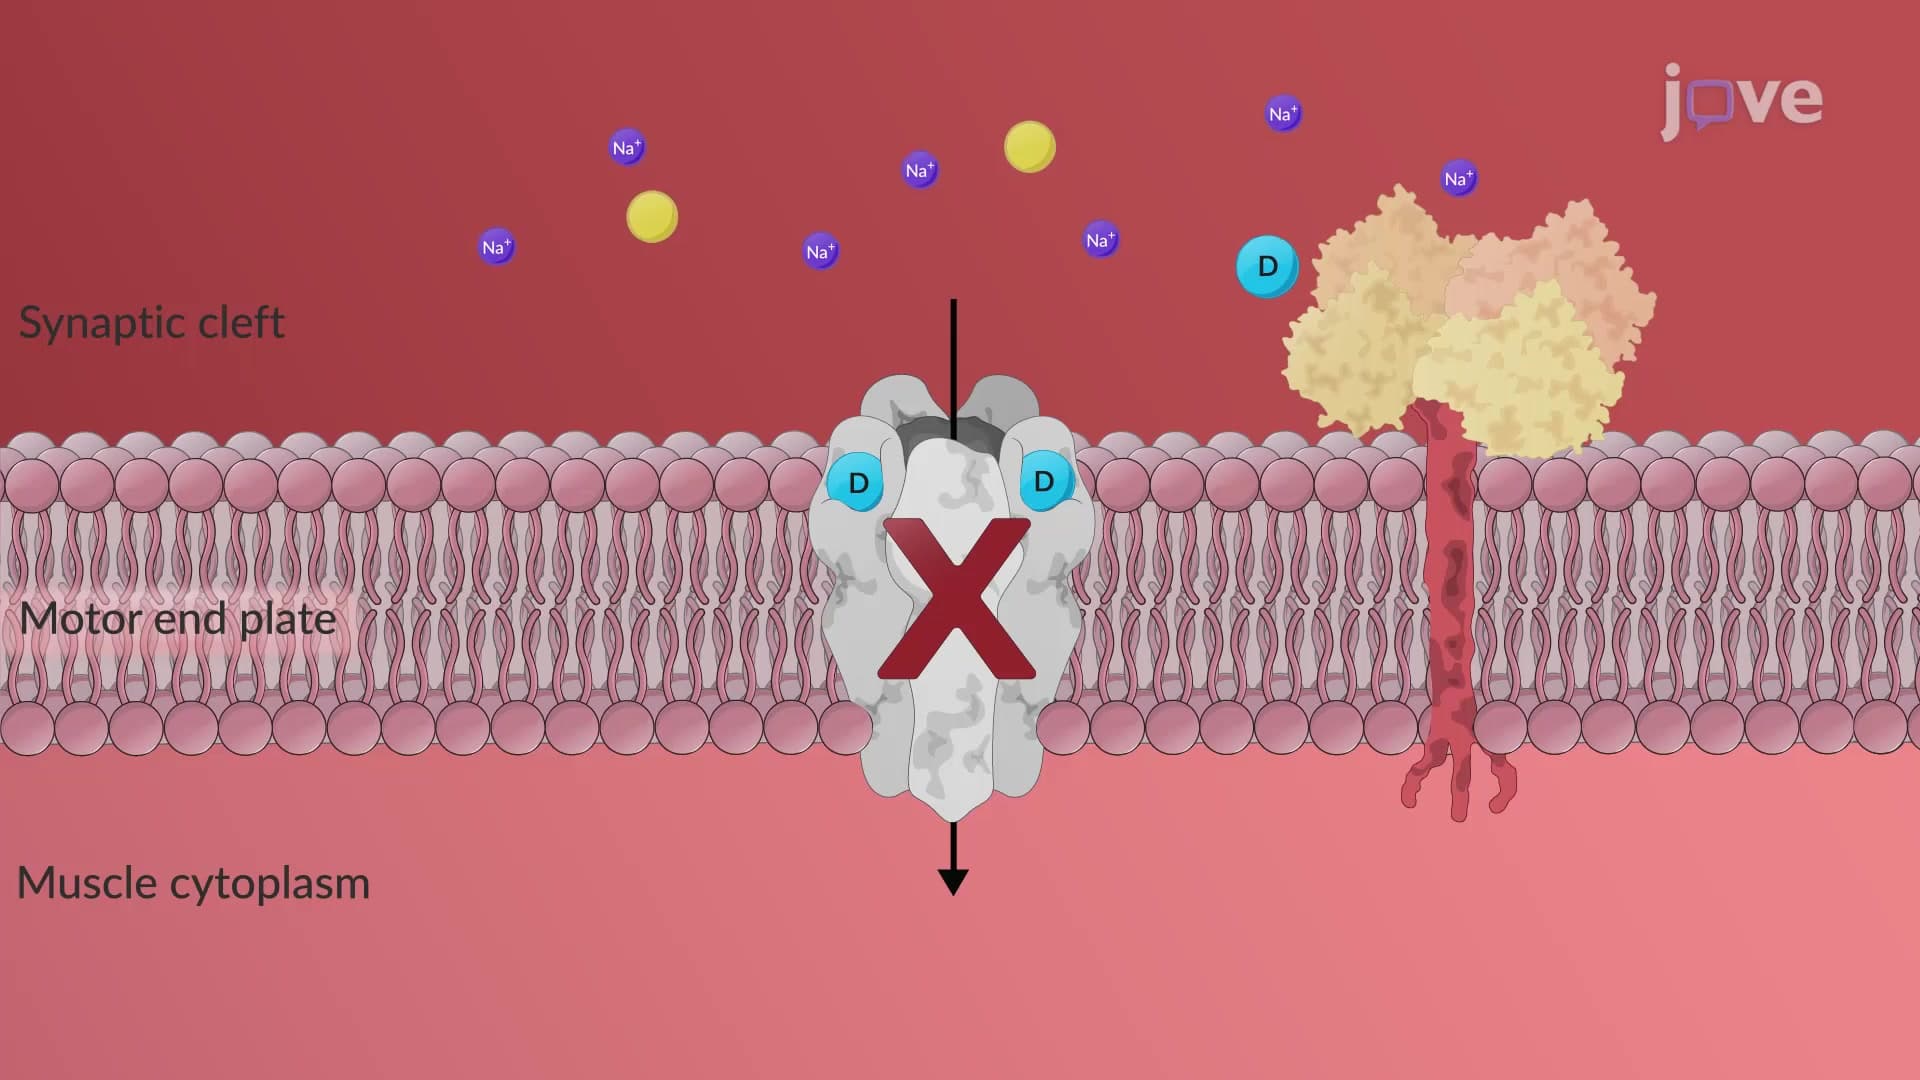
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:16
Critical Region, Critical Values and Significance Level
In hypothesis testing, a sample statistic is converted to a test statistic using z, t, or chi-square distribution. A critical region is an area under the curve in probability distributions demarcated by the critical value. When the test statistic falls in this region, it suggests that the null hypothesis must be rejected. As this region contains all those values of the...