Related Experiment Video
Updated: Feb 4, 2026


A Personalized 3D-Printed Model for Preoperative Evaluation in Thyroid Surgery
Published on: February 17, 2023
The Effect of Preoperative Anemia on Patients Undergoing Cardiac Surgery: A Propensity-Matched Analysis
Habib Jabagi1, Munir Boodhwani1, Diem T Tran2
1Divisions of Cardiac Surgery, University of Ottawa Heart Institute, Ottawa, Ontario, Canada.

It is unknown if anemia in the absence of transfusions is an independent risk factor for adverse outcomes in cardiac surgery, and if correction to higher hemoglobin targets impacts these outcomes. This is a retrospective review of 3848 cardiac surgery patients. Propensity matching was completed using 41 covariates. Intraoperative Anemia Analysis matched patients with or without anemia who did not receive intraoperative transfusions (n = 392/group), while Intraoperative Transfusion Analysis matched anemic patients treated conventionally with intraoperative transfusions to end cardiopulmonary bypass hemoglobin greater or less than 95 g/L (n = 261/group). Outcomes of death, renal failure, and 2 composite outcomes were assessed using paired analysis techniques. Study composite 1 consisted of prolonged ventilation, renal failure, myocardial infarction, stroke, or deep sternal wound infection, while composite 2 was the TRICS-III composite. In the Intraoperative Anemia Analysis, anemia was associated with mortality (P = 0.034), stroke (P = 0.021), renal failure (P = 0.015), and a significant increase in the composite measure (control 8.7% vs anemia 16.1%, P = 0.002). These findings were unchanged in patients who did not receive any postoperative transfusions. The Intraoperative Transfusion Analysis showed no difference in mortality or the composite outcome between groups. There was a significant increase in low cardiac output in the lower threshold group (P = 0.001). There were no differences in outcomes between those who did and did not receive postoperative transfusions (P > 0.05). Preoperative anemia in the absence of transfusions is a risk factor for morbidity and mortality after cardiac surgery, and there is no evidence that transfusion to higher end cardiopulmonary bypass hemoglobin levels impacted this risk.
It is unknown if anemia in the absence of transfusions is an independent risk factor for adverse outcomes in cardiac surgery, and if correction to higher hemoglobin targets impacts these outcomes. This is a retrospective review of 3848 cardiac surgery patients. Propensity matching was completed using 41 covariates. Intraoperative Anemia Analysis matched patients with or without anemia who did not receive intraoperative transfusions (n = 392/group), while Intraoperative Transfusion Analysis matched anemic patients treated conventionally with intraoperative transfusions to end cardiopulmonary bypass hemoglobin greater or less than 95 g/L (n = 261/group). Outcomes of death, renal failure, and 2 composite outcomes were assessed using paired analysis techniques. Study composite 1 consisted of prolonged ventilation, renal failure, myocardial infarction, stroke, or deep sternal wound infection, while composite 2 was the TRICS-III composite. In the Intraoperative Anemia Analysis, anemia was associated with mortality (P = 0.034), stroke (P = 0.021), renal failure (P = 0.015), and a significant increase in the composite measure (control 8.7% vs anemia 16.1%, P = 0.002). These findings were unchanged in patients who did not receive any postoperative transfusions. The Intraoperative Transfusion Analysis showed no difference in mortality or the composite outcome between groups. There was a significant increase in low cardiac output in the lower threshold group (P = 0.001). There were no differences in outcomes between those who did and did not receive postoperative transfusions (P > 0.05). Preoperative anemia in the absence of transfusions is a risk factor for morbidity and mortality after cardiac surgery, and there is no evidence that transfusion to higher end cardiopulmonary bypass hemoglobin levels impacted this risk.
More Related Videos
 07:14
A Quantitative Sensory Testing Paradigm to Obtain Measures of Pain Processing in Patients Undergoing Breast Cancer Surgery
Published on: January 18, 2018
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Related Concept Videos
 01:17
Sign Test for Matched Pairs
To conduct the sign test, we first calculate the differences in...
 01:09
Wilcoxon Signed-Ranks Test for Matched Pairs
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
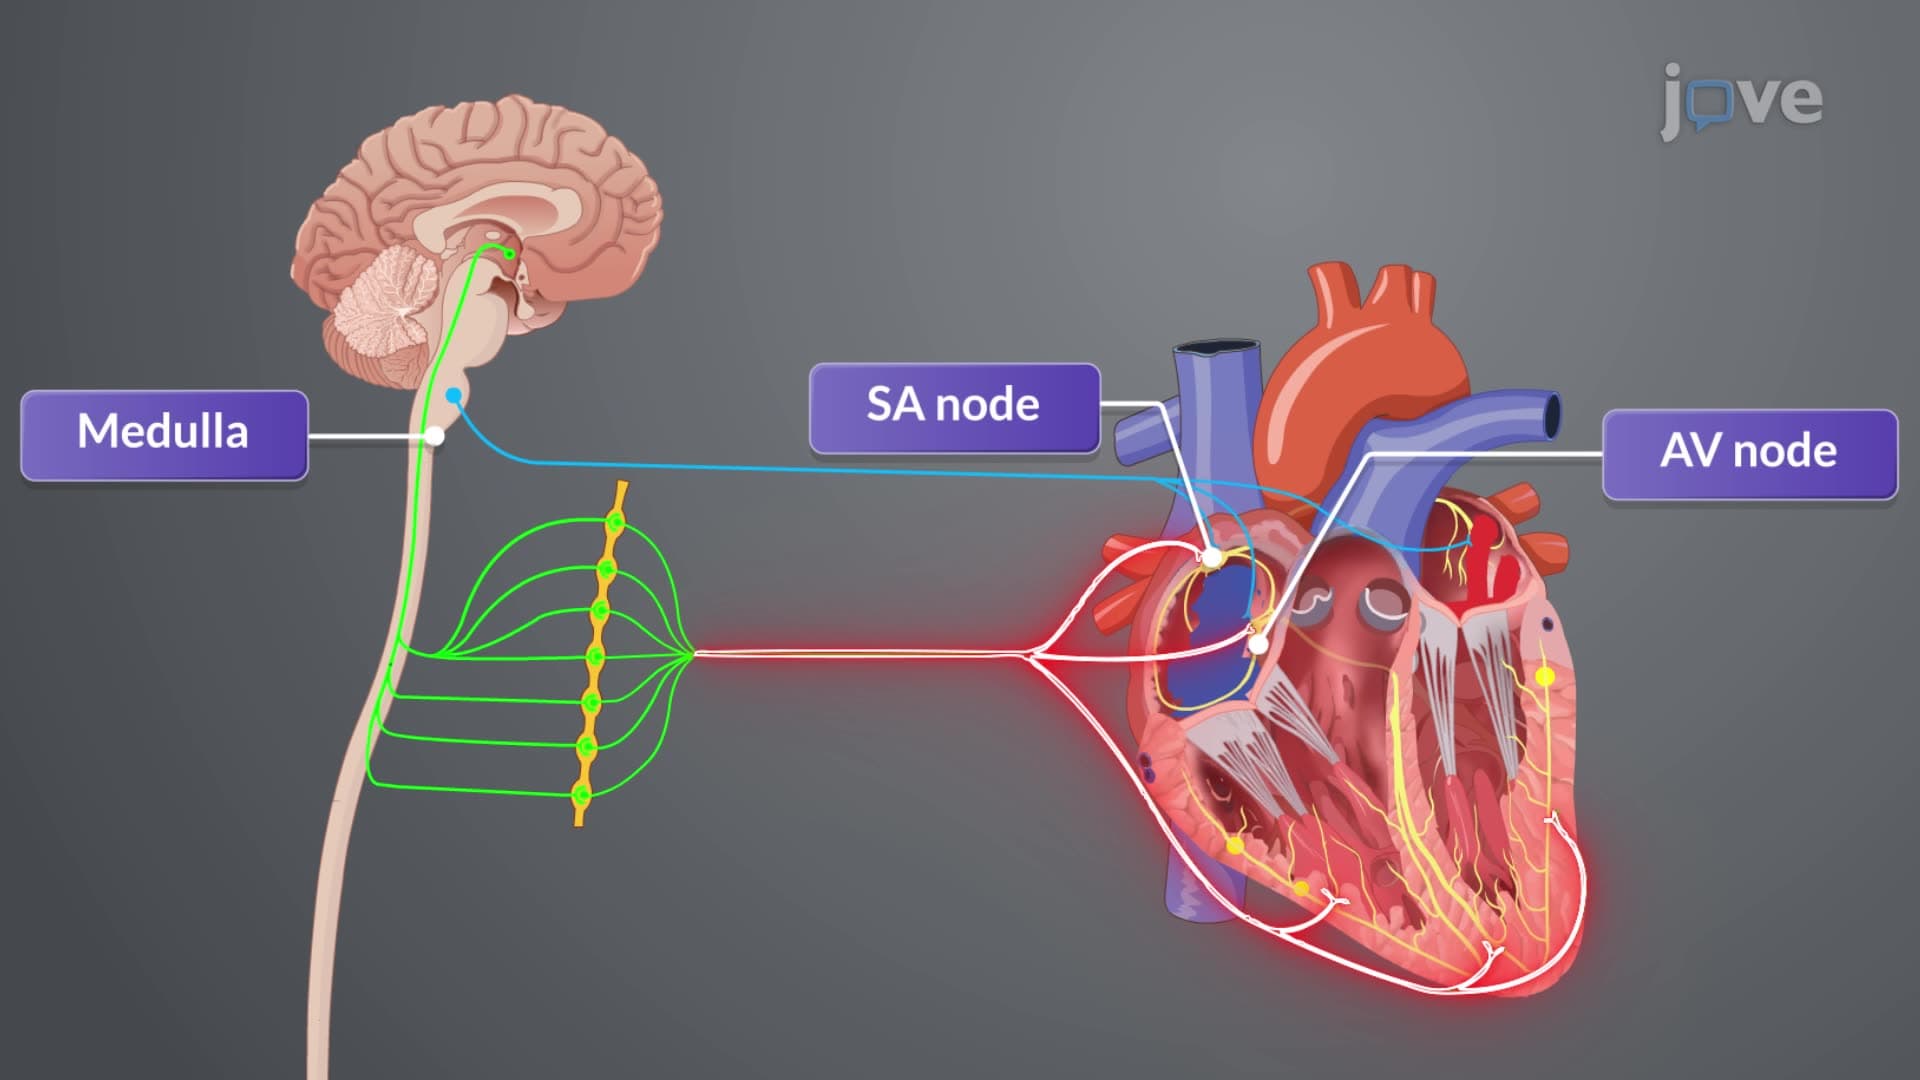
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and...
 01:29
Cardiac Cycle
During the cardiac cycle, blood flow through the heart is regulated entirely by changing pressure gradients. This sequence of events begins with the heart in a state of total relaxation, known as mid-to-late diastole, during which blood passively flows from...