Related Experiment Video
Updated: Feb 4, 2026


Local Anesthetic Thoracoscopy for Undiagnosed Pleural Effusion
Published on: November 10, 2023
In patients with unilateral pleural effusion, restricted lung inflation is the principal predictor of increased
Luke A Garske1,2, Kuhan Kunarajah3, Paul V Zimmerman2,3
1Institute of Health and Biomedical Innovation, Queensland University of Technology, Brisbane, Queensland, Australia.

Background And Objective:
The mechanism of dyspnoea associated with pleural effusion is uncertain. A cohort of patients requiring thoracoscopy for unilateral exudative effusion were investigated for associations between dyspnoea and suggested predictors: impaired ipsilateral diaphragm movement, effusion volume and restricted lung inflation.
Methods:
Baseline Dyspnoea Index, respiratory function, and ultrasound assessment of ipsilateral diaphragm movement were assessed prior to thoracoscopy, when effusion volume was measured. Transitional Dyspnoea Index (change from baseline) was assessed 4 and 8 weeks after thoracoscopy. Pearson product moment assessed bivariate correlations and a general linear model examined how well total lung capacity (measuring restricted lung inflation), effusion volume and impaired diaphragm movement predicted Baseline Dyspnoea Index. Un-paired t tests compared the groups with normal and impaired diaphragm movement.
Results:
19 patients were studied (14 malignant etiology). Total lung capacity was associated with Baseline Dyspnoea Index (r = 0.68, P = 0.003). Effusion volume (r = -0.138, P = 0.60) and diaphragm movement (P = 0.09) were not associated with Baseline Dyspnoea Index. Effusion volume was larger with impaired diaphragm movement compared to normal diaphragm movement (2.16 ±SD 0.95 vs.1.16 ±0.92 L, P = 0.009). Total lung capacity was lower with impaired diaphragm movement compared to normal diaphragm movement (65.4 ±10.3 vs 78.2 ±8.6% predicted, P = 0.011). The optimal general linear model to predict Baseline Dyspnoea Index used total lung capacity alone (adjusted R2 = 0.42, P = 0.003). In nine participants with controlled effusion, baseline effusion volume (r = 0.775, P = 0.014) and total lung capacity (r = -0.690, P = 0.040) were associated with Transitional Dyspnoea Index.
Conclusions:
Restricted lung inflation was the principal predictor of increased dyspnoea prior to thoracoscopic drainage of effusion, with no independent additional association with either effusion volume or impaired ipsilateral diaphragm movement. Restricted lung inflation may be an important determinant of the dyspnoea associated with pleural effusion.


Related Concept Videos
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's...
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 03:48
Behavior of Gas Molecules: Molecular Diffusion, Mean Free Path, and Effusion
 01:11
Principal Stresses in a Beam
Analyzing principal stresses is crucial, especially in...
 01:47
Lung Capacity
 01:14
Principal Moments of Area
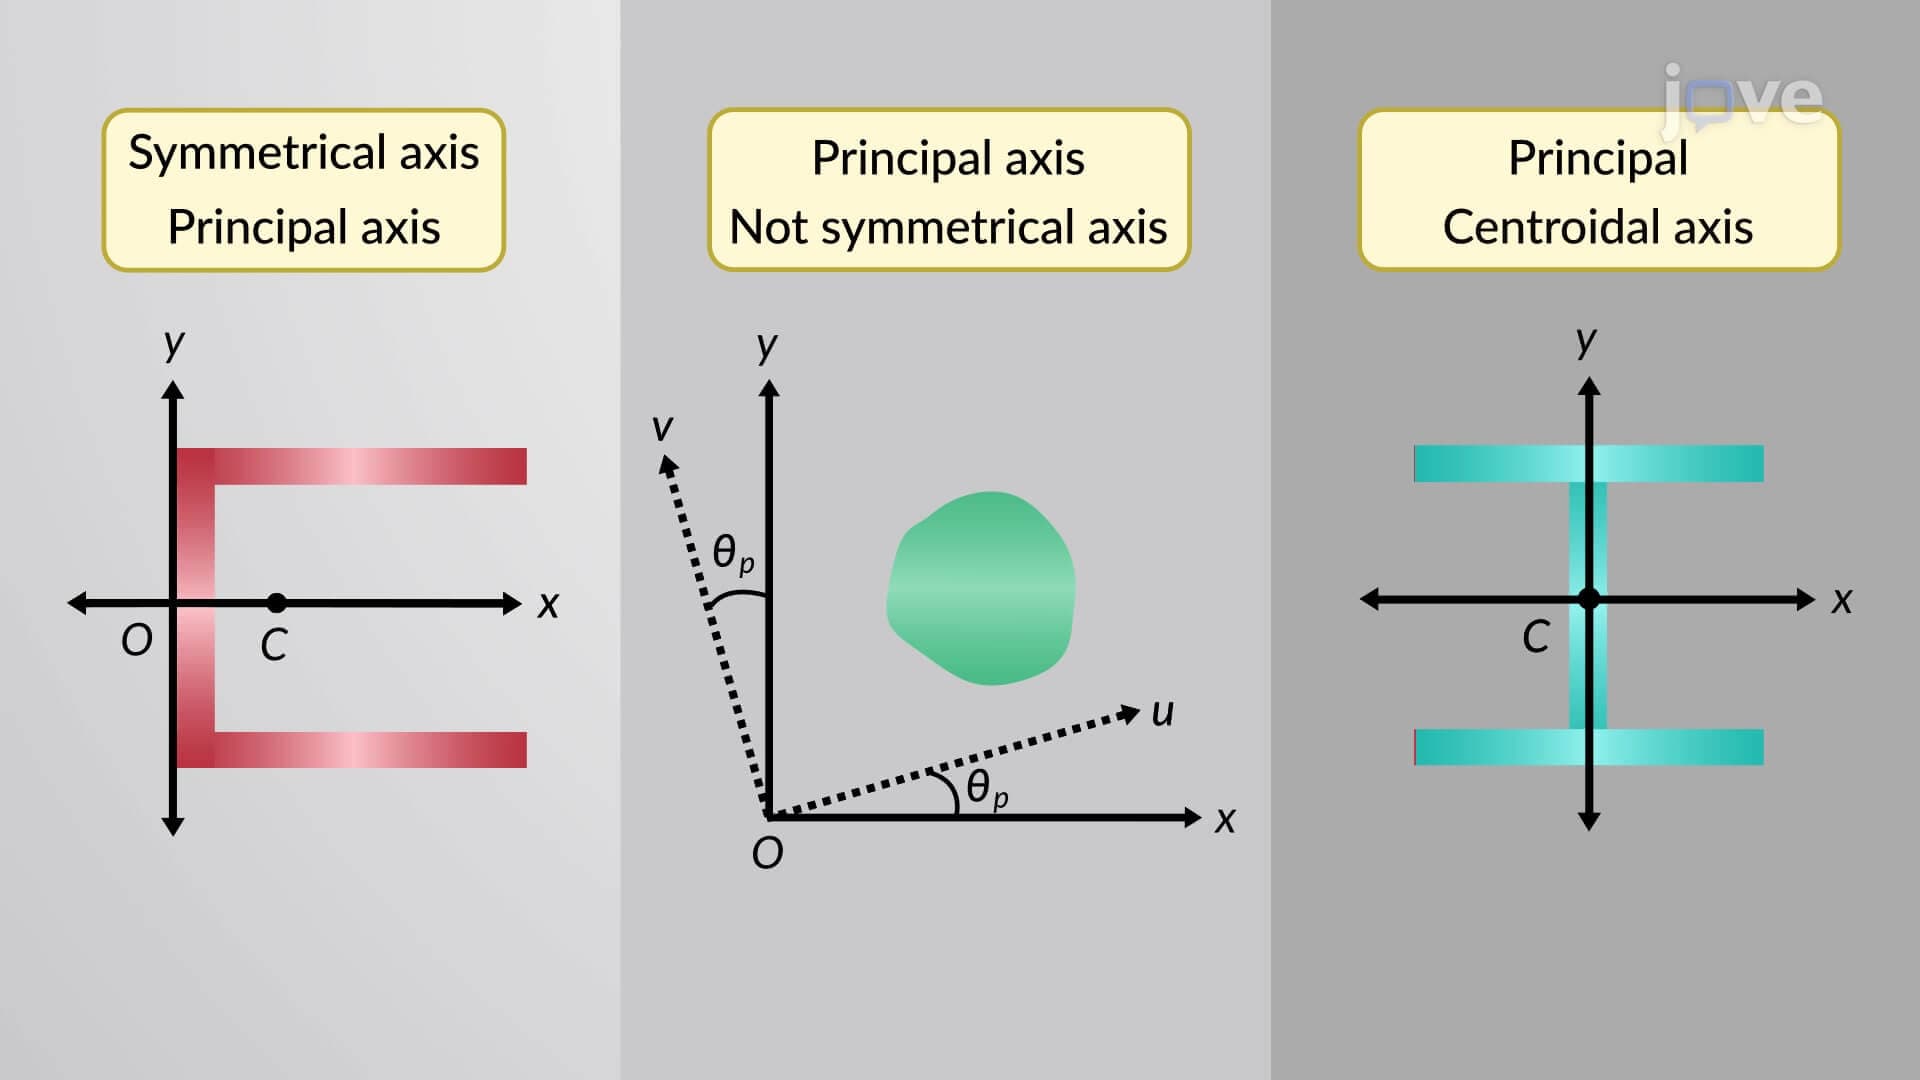
The principal moment of inertia axes are the...