Related Experiment Video
Updated: Feb 4, 2026
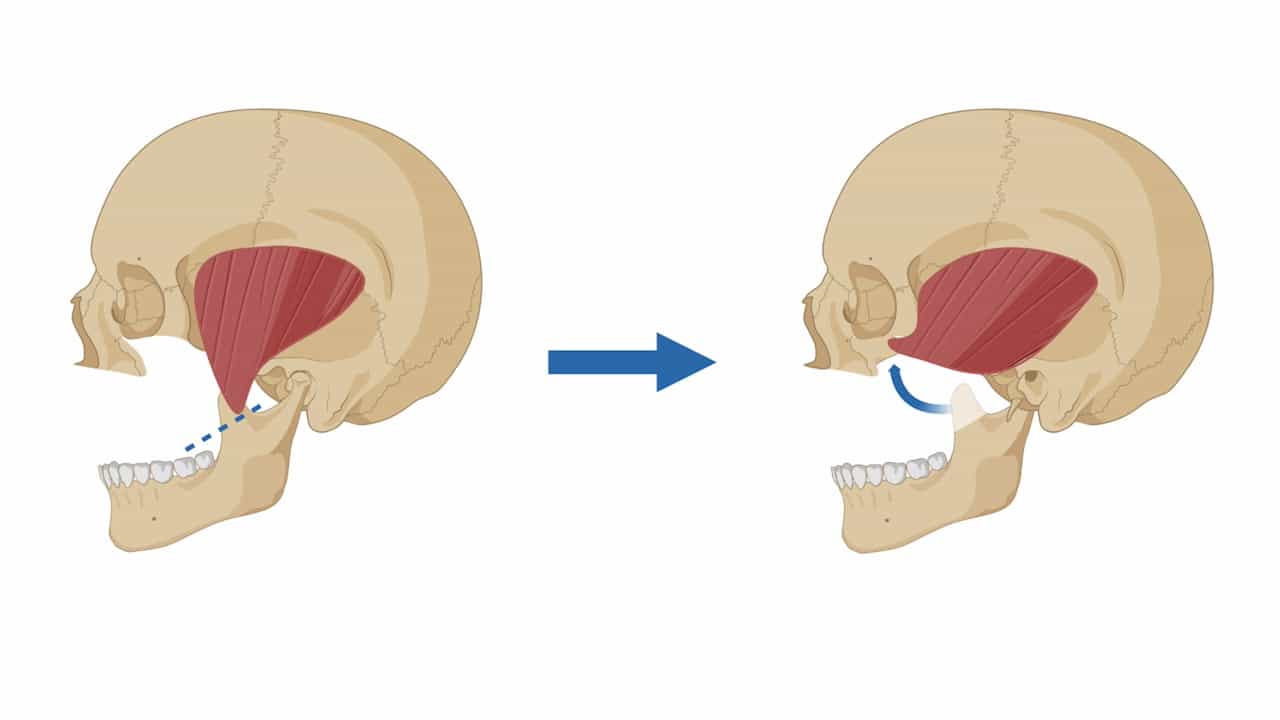
Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
[Clinical management of 110 cases of polypropylene mesh and sling exposure after reconstructive pelvic floor surgery]
1Department of Obstetrics and Gynecology, First Affiliated Hospital of PLA General Hospital, Beijing 100048, China.

Abstract:
Objective: To explore the clinical management and outcomes of polypropylene mesh and sling exposure after reconstructive pelvic surgery (RPS) . Methods: A total of 110 cases of mesh and sling exposure after RPS were analyzed, who admitted between Jan. 2002 and Oct. 2017 in First Affiliated Hospital of PLA General Hospital, in which 3 cases were referred from other hospitals. Mesh and sling exposures were identified in the outpatient clinic and categorized and managed according to International Continence Society and International Urogynecology Association (ICS-IUGA) classification about category, time and site (CTS) of mesh complication. Outpatient management included observation, topical estrogen use and mesh removal. Management in hospital included surgical removal of exposed mesh and repair of the resulting defects under the anesthesia. Seventy-four cases were managed in the outpatient setting, and 36 cases required inpatient management. Follow-up was consecutively performed from 1 month to 10 years. Objective outcome included the surgeon's assessment of the healing state of the vaginal mucosa. Subjective outcome was evaluated with patient global impression of improvement questionnaire (PGI-I) . Results: One hundred and ten patients with mesh exposure were classified according to the different RPS underwent. There were 95 cases from transvaginal mesh surgery, 5 cases from anti-stress urinary incontinence sling surgery, and 10 cases from sacrocolpopxy. The outpatient group healed at an average of (3.0±1.8) months. Of the 36 patients who required inpatient management, 21 cases healed completely at an average of 7 days after one surgery. The remaining 8 cases required either two or three times surgeries or conservative management. In the outpatient group, the PGI-I scale very much better was found in 65 cases (87.8%) and much better in 9 cases (12.2%) . In the inpatient surgery group, the scale was very much better in 30 cases (83.3%) , and much better in 6 cases (16.7%) . Conclusions: Among patients with mesh exposure after mesh-augmented RPS, 2/3 of patients with a CTS classification 1-3 could be managed in the office, and remaining 1/3 with CTS classification 4-6 need operation under anesthesia in hospital. If the mesh and sling exposure could be scientifically classified, according to the size, site and accompany symptoms, as well as pain, most of the mesh complications after explosure could be resolved. Using the pelvic floor repair and polypropylene mesh sling, the majority of the patients could get a better outcome, without affecting the effect of the original operation.
Related Concept Videos
 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...