Related Experiment Video
Updated: Feb 4, 2026


Tumor Engraftment in a Xenograft Mouse Model of Human Mantle Cell Lymphoma
Published on: March 30, 2018
Perforation of the small intestine caused by enteropathy-associated T cell lymphoma
Selva Kabul1, Nesrin Uğraş1, Ömer Yerci1
1Department of Surgical Pathology, Uludağ University School of Medicine, Bursa, Turkey.

Abstract:
Enteropathy-associated T cell lymphoma is a rare lymphoma specific to the gastrointestinal system, arising from intraepithelial T lymphocytes, that is often associated with celiac disease. We report a 53-year-old female patient with no previous disease who presented with severe abdominal pain. Physical examination revealed diffuse abdominal tenderness and abdominal guarding and the patient underwent emergency surgery with a diagnosis of acute abdomen. During the operation, a 20-cm mass was found located on Treitz ligament, invading the duodenum and pancreatic head and perforating the jejunum. Histologically, medium-sized monomorphic atypical lymphocyte infiltration with dark nucleus and narrow cytoplasm was seen in the layers of mucosa, submucosa, muscular wall, and serosa of the duodenum. The final pathological diagnosis was "enteropathy-associated T cell lymphoma type 2" based on immunohistochemical and serological findings. Based on the World Health Organization 2008 criteria, enteropathy-associated T cell lymphoma has two subtypes. Type 1 enteropathy-associated T cell lymphoma is associated with celiac disease and has HLA DQ2 and HLA DQ8 genotype. Enteropathy-associated T cell lymphoma 2 enteropathy-associated T cell lymphoma seldom occurs and is not associated with celiac disease.


Related Concept Videos
 01:23
Anatomy of the Intestines
Small Intestines
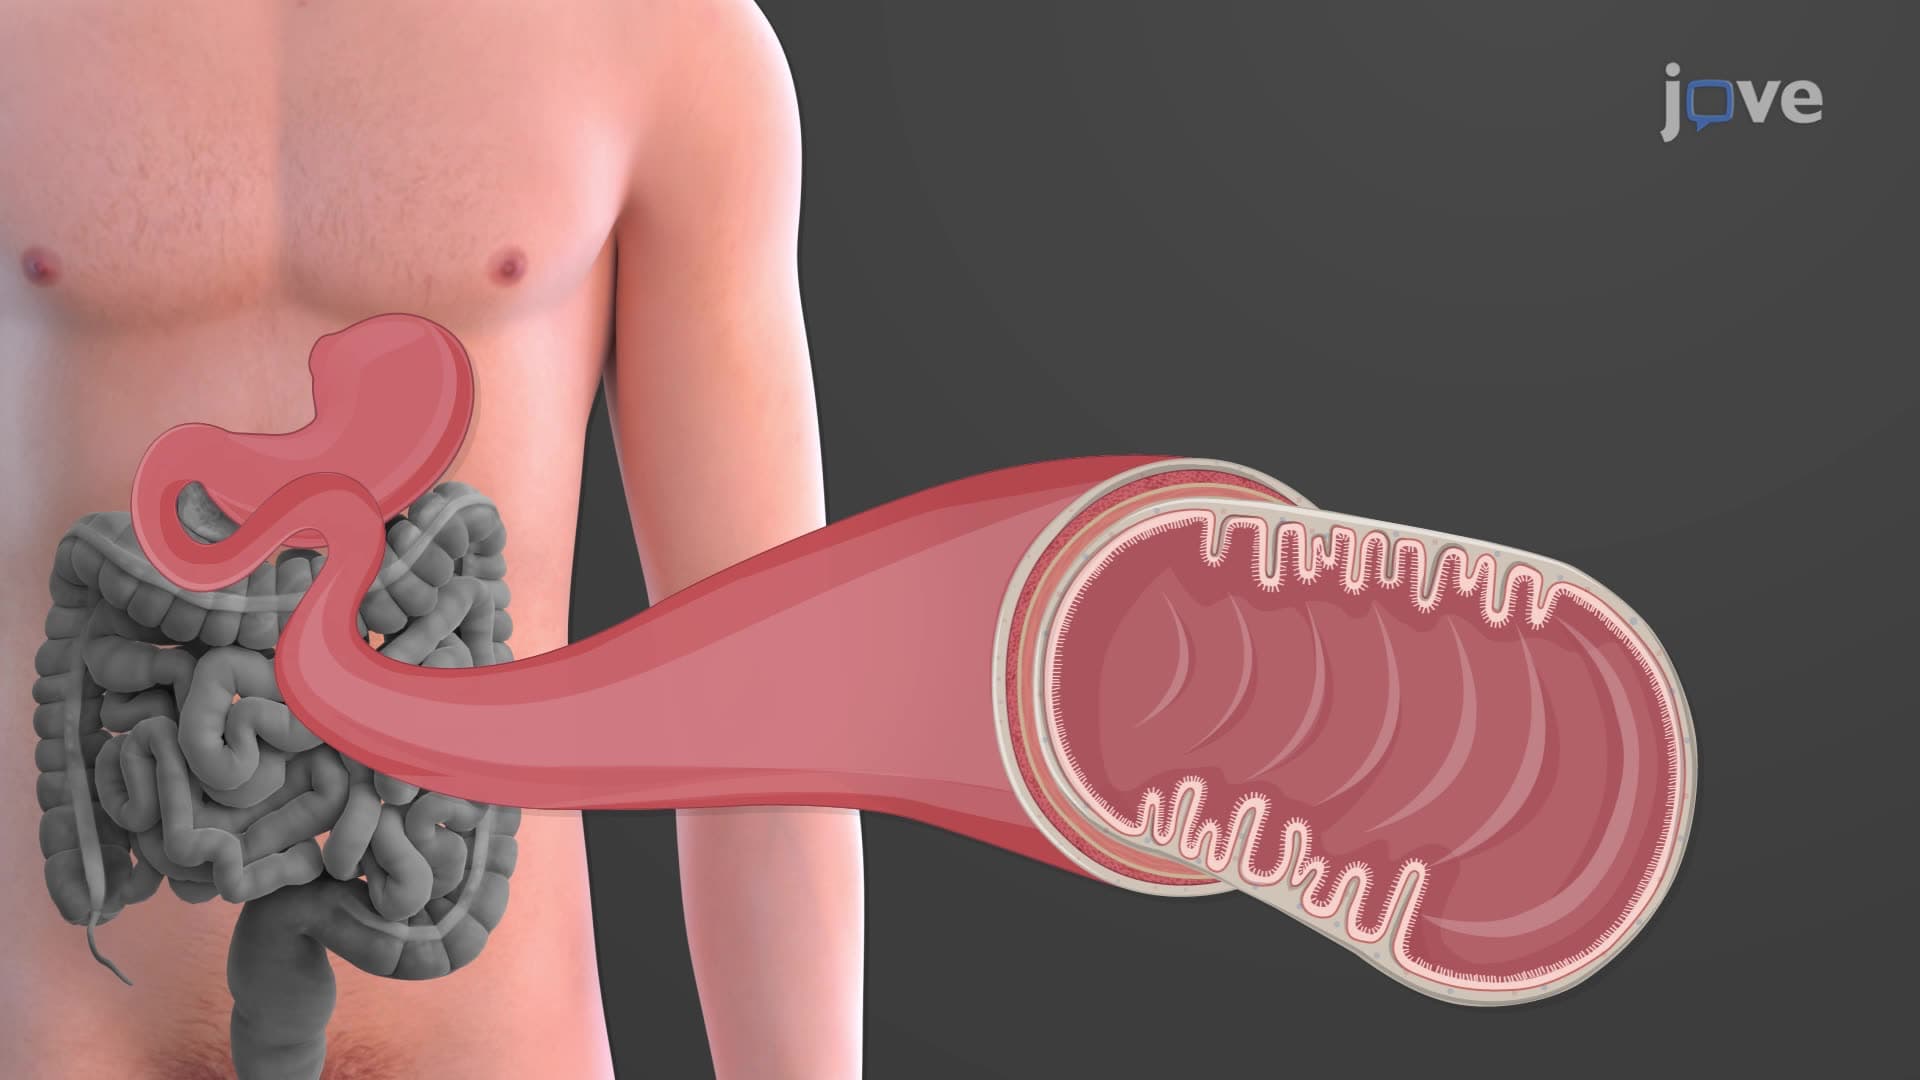
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:23
Renewal of Intestinal Stem Cells
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:15
Small Intestine
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique...
 01:09
Large Intestine
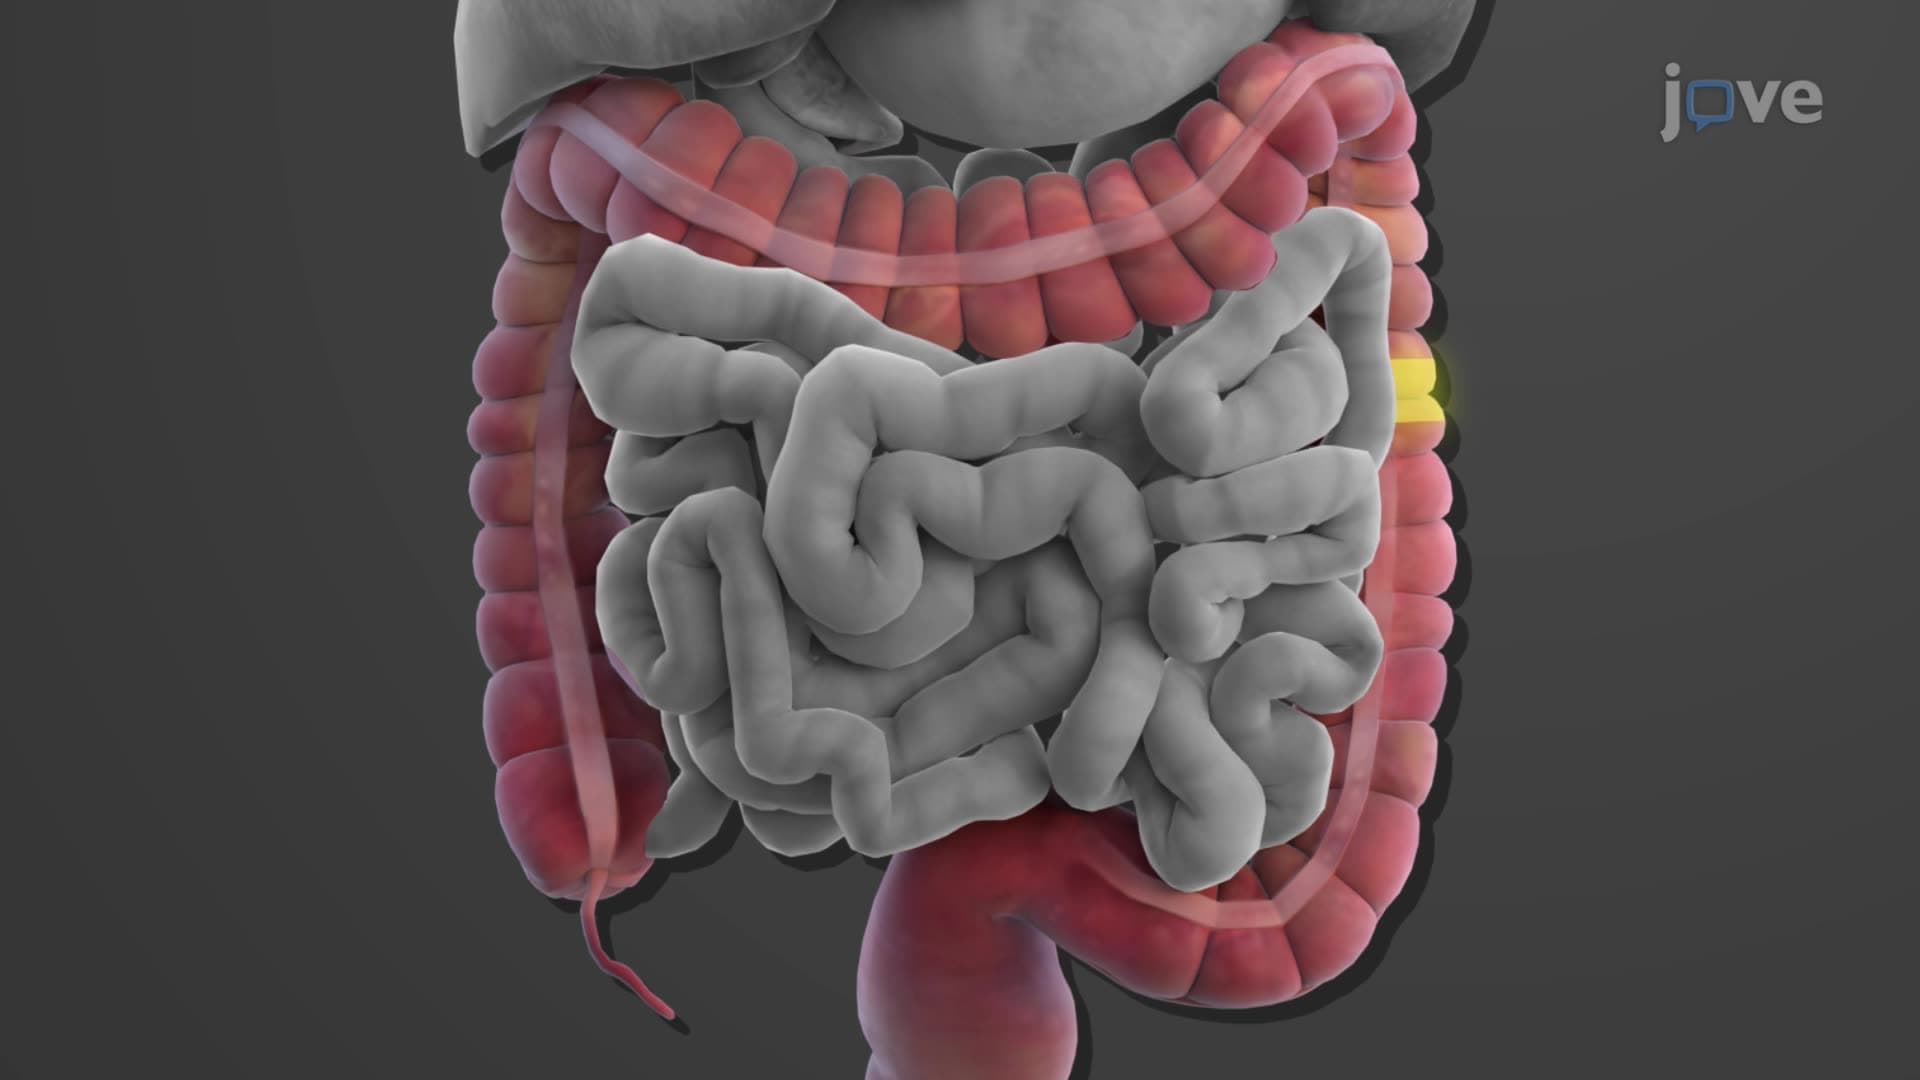
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...