Related Experiment Video
Updated: Feb 4, 2026
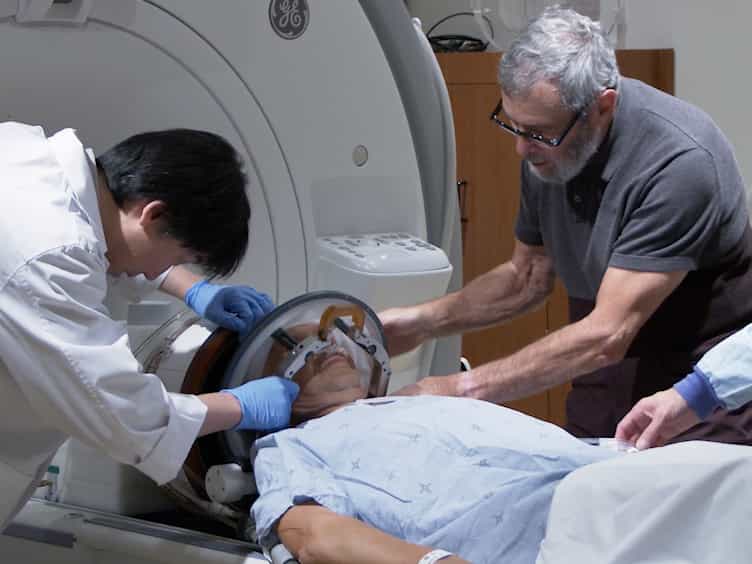

MRI-guided Focused Ultrasound Thalamotomy for Patients with Medically-refractory Essential Tremor
Published on: December 13, 2017
Refractory spontaneous hypoglycaemia: a diagnostic conundrum
Seong Keat Cheah1, David Halsall2, Peter Barker3
1Endocrinology Department, Hinchingbrooke Hospital, North West Anglia NHS Foundation Trust, Huntingdon, UK.

Abstract:
A frail 79-year-old lady with dementia presented with a 2-year history of frequent falls. Recurrent hypoglycaemic episodes were diagnosed and treated with continuous glucose infusion in multiple hospital admissions. Hypoadrenalism and hypothyroidism were ruled out. Whilst hypoglycaemic (blood glucose 1.6 mmol/L), both plasma C-peptide and proinsulin concentrations, were inappropriately elevated at 4210 pmol/L (174–960) and >200 pmol/L (0–7) respectively with plasma insulin suppressed at 12 pmol/L (0–180). Whilst reported cases of proinsulinoma are typically pancreatic in origin, radiological investigations of the pancreas in this patient did not identify abnormalities. Unexpectedly contrast CT identified a heterogeneously enhancing mass (6.6 cm) at the lower pole of the left kidney consistent with renal cell carcinoma. Non-islet cell tumour-induced hypoglycaemia has been associated with renal malignancy; however, a serum IGF2:IGF1 ratio measured at <10 effectively excludes this diagnosis. Concomitantly on the CT, extensive peripherally enhancing heterogeneous mass lesions in the liver were identified, the largest measuring 12 cm. A palliative approach was taken due to multiple comorbidities. On post-mortem, the kidney lesion was confirmed as clear cell renal carcinoma, whilst the liver lesions were identified as proinsulin-secreting neuroendocrine tumours. In conclusion, the diagnosis of proinsulinoma can be missed if plasma proinsulin concentration is not measured at the time of hypoglycaemia. In this case, the plasma insulin:C-peptide ratio was too high to be accounted for by the faster relative clearance of insulin and was due to proinsulin cross-reactivity in the C-peptide assay. In addition, the concomitant malignancy proved to be a challenging red herring. Learning points: •• Even in non-diabetics, hypoglycaemia needs to be excluded in a setting of frequent falls. Insulin- or proinsulinsecreting tumours are potentially curable causes. •• Whilst investigating spontaneous hypoglycaemia, if plasma insulin concentration is appropriate for the hypoglycaemia, it is prudent to check proinsulin concentrations during the hypoglycaemic episode. •• Proinsulin cross-reacts variably with C-peptide and insulin assays; the effect is method dependent. In this case, the discrepancy between the insulin and C-peptide concentrations was too great to be accounted for by the faster relative clearance of insulin, raising the suspicion of assay interference. The C-peptide assay in question (Diasorin liaison) has been shown to be 100% cross reactive with proinsulin based on spiking studies with a proinsulin reference preparation. •• Whilst reported cases of proinsulinoma and 99% of insulinomas are of pancreatic origin, conventional imaging studies (CT, MRI or ultrasound) fail to detect neuroendocrine tumours <1 cm in 50% of cases. •• The concomitant renal mass identified radiologically proved to be a red herring. •• In view of the rarity of proinsulinoma, no conclusive association with renal cell carcinoma can be established.


Related Concept Videos
 02:21
Spontaneity
 01:30
Spontaneous and Induced Mutations
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:19
Pericarditis II: Clinical Features and Diagnostic Tests