Related Experiment Video
Updated: Feb 4, 2026

Isolation of Exosomes from the Plasma of HIV-1 Positive Individuals
Published on: January 5, 2016
Lamivudine monotherapy as a holding regimen for HIV-positive children
Gabriela Patten1, Jonathan Bernheimer2, Lee Fairlie3
1Centre for Infectious Disease Epidemiology & Research, University of Cape Town, Cape Town, South Africa.

Insights
Lamivudine monotherapy (LM) in HIV-positive children on combination antiretroviral therapy (cART) often leads to immune decline. Restricted use is advised, especially for children with low CD4 counts, due to limited treatment options.
Area of Science:
- Pediatric infectious diseases
- HIV/AIDS management
- Pharmacological outcomes in children
Background:
- Resource-limited settings often use lamivudine monotherapy (LM) for HIV-positive children failing combination antiretroviral therapy (cART).
- LM is employed to mitigate drug resistance and manage adherence issues or restricted access to second- or third-line regimens.
- This study investigates the characteristics and outcomes of children managed with LM.
Purpose of the Study:
- To characterize children initiated on lamivudine monotherapy (LM) for HIV treatment failure.
- To evaluate the immunologic and virologic outcomes of children on LM and after resuming combination antiretroviral therapy (cART).
Main Methods:
- Analysis of data from 5 IeDEA-SA cohorts, including 228 children under 16 years at cART start.
- Assessment of immunologic outcomes (CD4 counts) during LM (for >90 days) and after resuming cART.
- Evaluation of virologic outcomes (viral load) after resuming cART.
Main Results:
- Children on LM experienced a median CD4 count decline of 46.5 cells/μL over 6 months, with 46% dropping below 500 cells/μL.
- 8% experienced WHO stage 3 or 4 events, and 3 deaths occurred during LM.
- Upon resuming cART, children gained an average of 15.65 CD4 cells/μL per month, with 66.6% achieving viral suppression (<1000 copies/mL) within 6 months.
Conclusions:
- Lamivudine monotherapy (LM) is associated with significant immune decline in HIV-positive children.
- LM should be avoided in children with low CD4 counts but may be a necessary option when treatment alternatives are limited.
- Improved treatment options and adherence strategies are crucial for managing children with virologic failure on cART.
Background:
In resource-limited settings holding regimens, such as lamivudine monotherapy (LM), are used to manage HIV-positive children failing combination antiretroviral therapy (cART) to mitigate the risk of drug resistance developing, whilst adherence barriers are addressed or when access to second- or third-line regimens is restricted. We aimed to investigate characteristics of children placed on LM and their outcomes.
Methods:
We describe the characteristics of children (age <16 years at cART start) from 5 IeDEA-SA cohorts with a record of LM during their treatment history. Among those on LM for >90 days we describe their immunologic outcomes on LM and their immunologic and virologic outcomes after resuming cART.
Findings:
We included 228 children in our study. At LM start their median age was 12.0 years (IQR 7.3-14.6), duration on cART was 3.6 years (IQR 2.0-5.9) and median CD4 count was 605.5 cells/μL (IQR 427-901). Whilst 110 (48%) had no prior protease inhibitor (PI)-exposure, of the 69 with recorded PI-exposure, 9 (13%) patients had documented resistance to all PIs. After 6 months on LM, 70% (94/135) experienced a drop in CD4, with a predicted average CD4 decline of 46.5 cells/μL (95% CI 37.7-55.4). Whilst on LM, 46% experienced a drop in CD4 to <500 cells/μL, 18 (8%) experienced WHO stage 3 or 4 events, and 3 children died. On resumption of cART the average gain in CD4 was 15.65 cells/uL per month and 66.6% (95% CI 59.3-73.7) achieved viral suppression (viral load <1000) at 6 months after resuming cART.
Interpretation:
Most patients experienced immune decline on LM. Its use should be avoided in those with low CD4 counts, but restricted use may be necessary when treatment options are limited. Managing children with virologic failure will continue to be challenging until more treatment options and better adherence strategies are available.
More Related Videos

Related Concept Videos
 01:15
Drug Dosage Regimen: Overview
Typically, the starting dose and dosing interval are guided by the manufacturer's recommendations based on clinical trials conducted during and after drug...
 01:24
Dosage Regimen: Individualization
 02:32
Position-effect Variegation
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:25
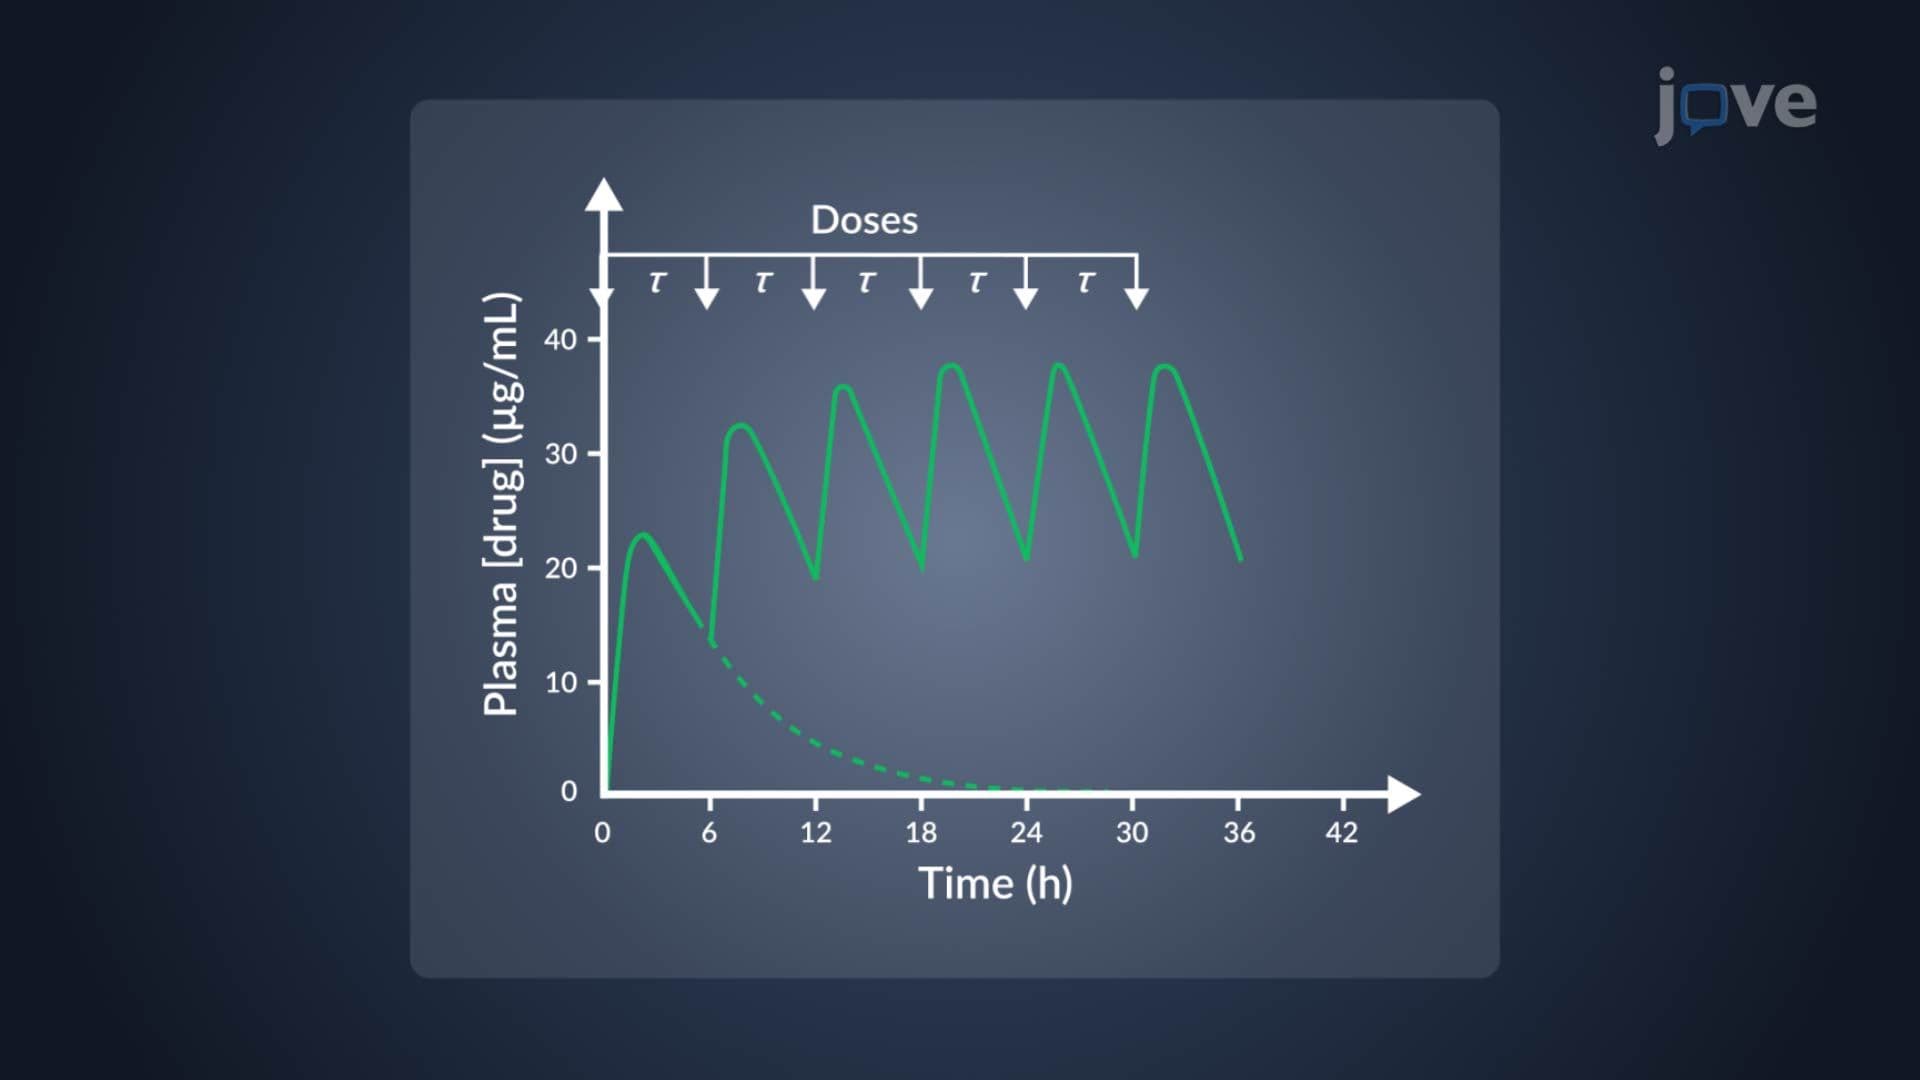
Dosage Regimen: Multiple Oral Dosage
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...