Related Experiment Video
Updated: Feb 3, 2026

Novel and Innovative Hybrid Technique for Type A Aortic Dissection
Published on: March 28, 2025
Wide Dissection and Intercostal Vessel Division Allows for Repair of Hypoplastic Aortic Arch Through Thoracotomy
Néstor F Sandoval1, Catalina Vargas Acevedo2, Juan Bernardo Umaña3
11 Congenital Heart Disease Institute, Fundación Cardioinfantil, Instituto de Cardiología, Bogotá, Colombia.

Insights
A modified surgical technique for coarctation of the aorta with a hypoplastic aortic arch, performed via thoracotomy, showed comparable outcomes to standard repair. This approach achieved successful repair without increasing adverse events, including paraplegia.
Area of Science:
- Cardiovascular Surgery
- Pediatric Cardiology
- Thoracic Surgery
Background:
- Coarctation of the aorta with a hypoplastic aortic arch presents a surgical challenge with controversial treatment approaches.
- Posterior left lateral thoracotomy is a surgical approach evaluated for these complex cases.
Purpose of the Study:
- To evaluate the outcomes of surgical repair for coarctation of the aorta (CoA) with and without a hypoplastic aortic arch (HA).
- To assess the efficacy of a modified extended end-to-end anastomosis technique in patients with CoA and HA.
Main Methods:
- Retrospective analysis of 143 patients with coarctation of the aorta who underwent surgical repair between 2009 and 2017.
- Comparison of outcomes between patients with and without a hypoplastic aortic arch, focusing on survival, reintervention, and recoarctation rates.
- Evaluation of postoperative complications, including renal failure, neurologic events, sepsis, and length of hospital stay.
Main Results:
- A modified technique involving wide aortic dissection and mobilization was used in 29 patients with hypoplastic aortic arch.
- No statistically significant differences were observed in postoperative complications, survival, freedom from reintervention, or freedom from recoarctation between groups.
- One postoperative mortality occurred in each group, both linked to noncardiac comorbidities.
Conclusions:
- A modified extended end-to-end anastomosis technique facilitates successful repair of coarctation of the aorta with a hypoplastic aortic arch via thoracotomy.
- This surgical modification can be performed without an increased risk of paraplegia or other adverse outcomes.
Background:
The approach to coarctation of the aorta with hypoplastic aortic arch is controversial. We evaluated the outcomes in patients with coarctation of the aorta with or without hypoplastic aortic arch operated through a posterior left lateral thoracotomy.
Methods:
A retrospective cohort of patients with aortic coarctation, who underwent repair between January 2009 and October 2017, was analyzed. Preoperative, postoperative, and echocardiographic characteristics were reviewed. Statistical analysis examined survival, freedom from reintervention, and freedom from recoarctation.
Results:
In nine years, 389 patients who underwent surgical treatment for coarctation of the aorta were identified; after exclusion criteria and complete echocardiographic reports, 143 patients were analyzed, of which 29 patients had hypoplastic aortic arch. The modification in the extended end-to-end anastomosis technique was a wide dissection and mobilization of the descending aorta that was achieved due to the ligation and division of 3 to 5 intercostal vessels. In both groups, patients were close to one month of age and had a median weight of 3.6 and 3.4 kg for hypoplastic and nonhypoplastic arch, respectively. In postoperative events, there was no statistically significant difference between the groups ( P = .57 for renal failure, P = .057 for transient, nonpermanent neurologic events, P = .496 for sepsis), as for intensive care unit ( P = .502) and total in-hospital stay ( P = .929). There was one case of postoperative mortality in each group and both were associated with noncardiac comorbidities. Regarding survival (log-rank = 0.060), freedom from reintervention (log-rank = 0.073), and freedom from recoarctation (log-rank = 0.568), there was no statistically significant difference between the groups.
Conclusion:
We believe that it is the modified technique that allowed greater mobilization of the aorta and successful repair of hypoplastic arch through thoracotomy, without an increase in paraplegia or other adverse outcomes.
More Related Videos


Related Concept Videos
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:36
Mismatch Repair
 02:25
Overview of DNA Repair
Chemically...
 01:26
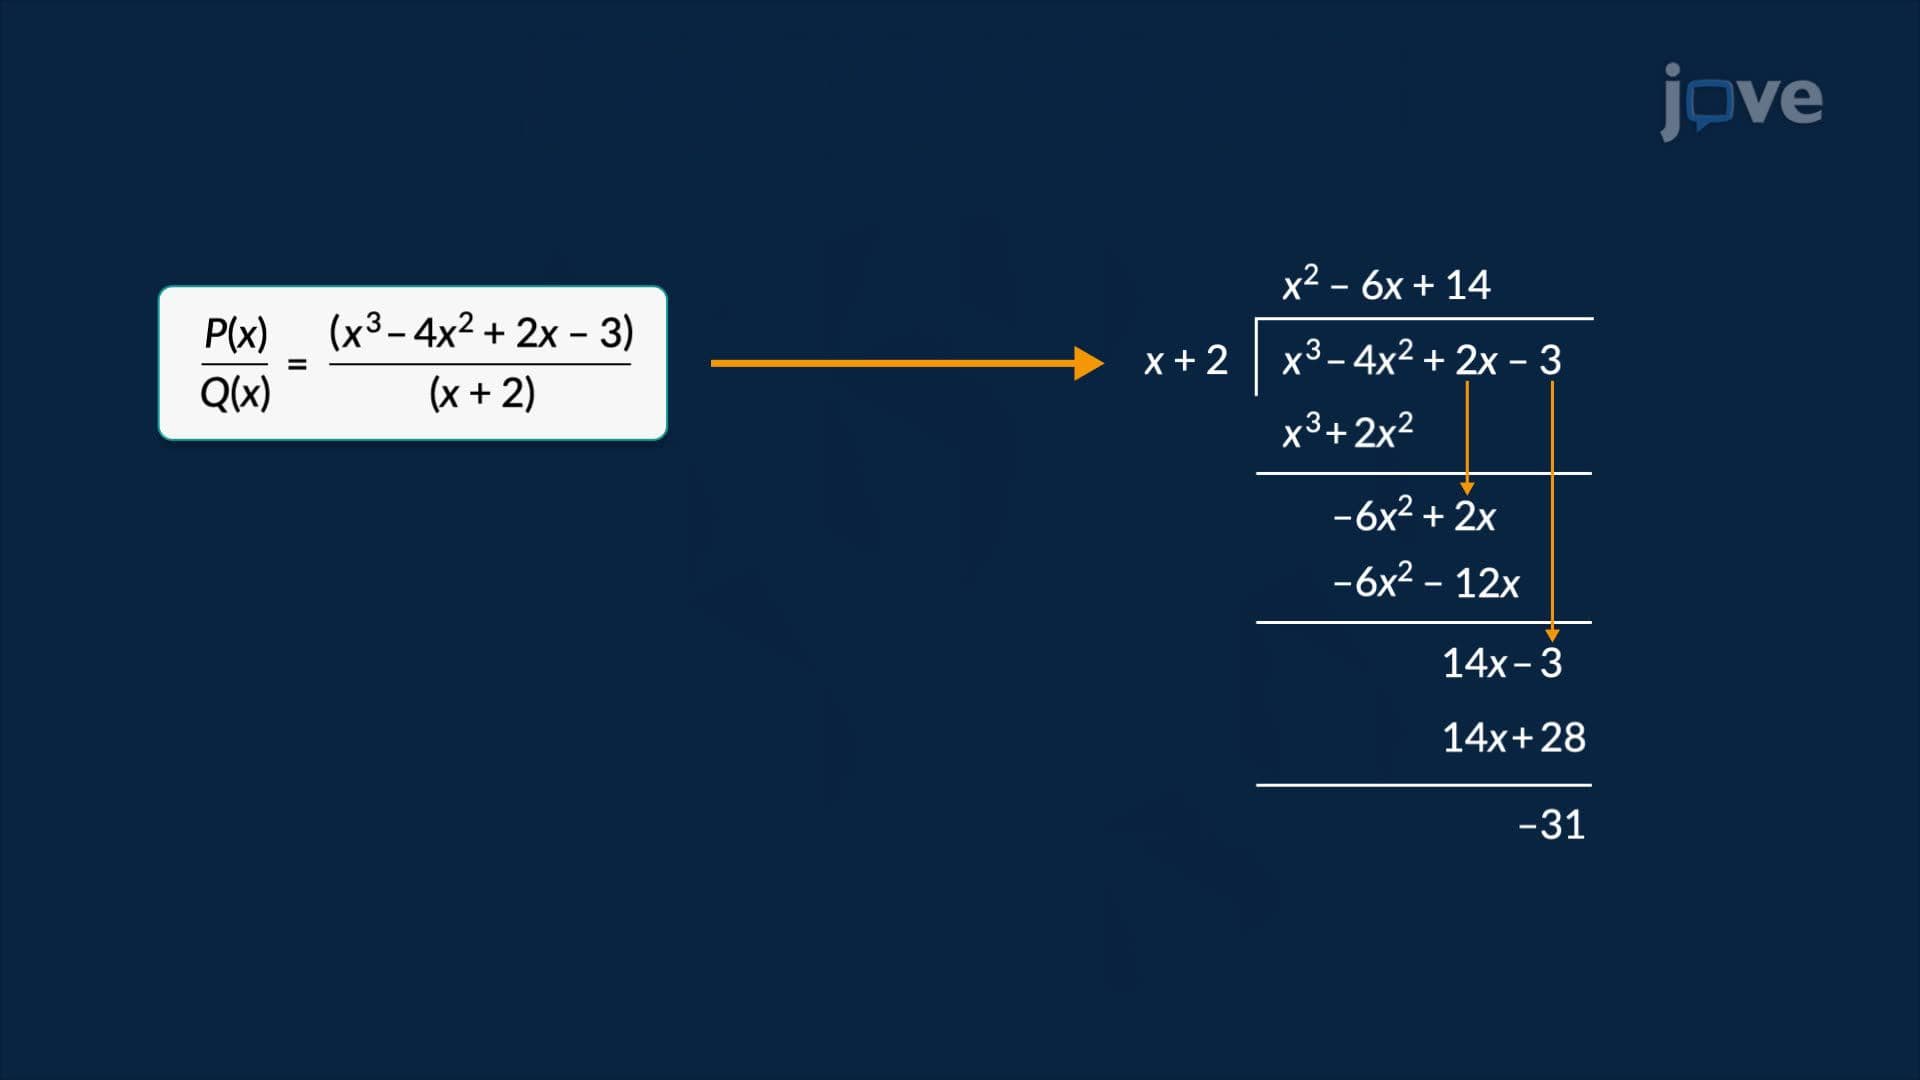
Long Division of Polynomials
 01:54
Base Excision Repair
The first step of...
 01:08
Nucleotide Excision Repair