Related Experiment Video
Updated: Feb 3, 2026
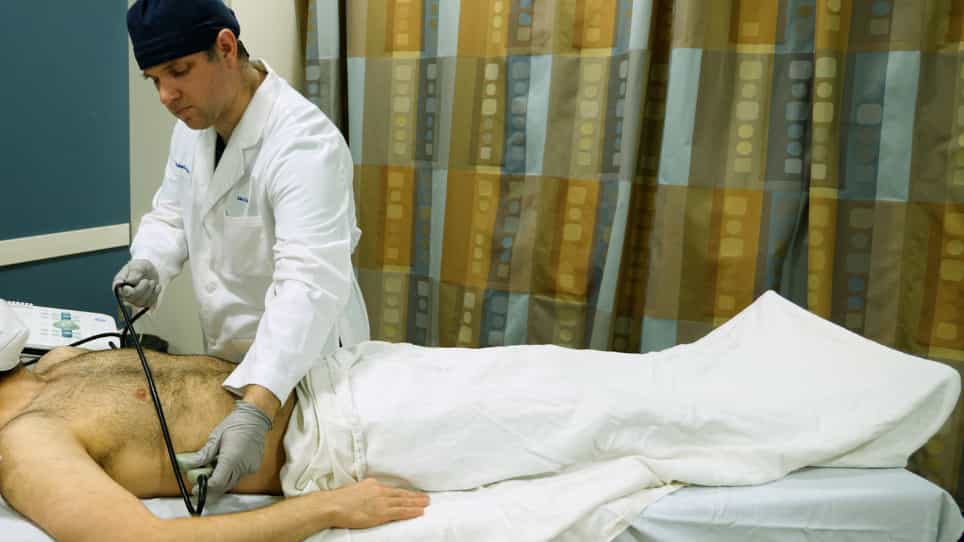

Focused Assessment with Sonography for Trauma FAST Exam: Image Acquisition
Published on: September 22, 2023
Association of System-Level Factors With Secondary Overtriage in Trauma Patients
Priti P Parikh1, Pratik Parikh1,2, Logan Mamer2
1Department of Surgery, Wright State University, Dayton, Ohio.

Importance:
Studies show that secondary overtriage (SO) contributes significantly to the economic burden of injured patients; thus, the association of SO with use of the trauma system has been examined. However, the association of the underlying trauma system design with such overtriage has yet to be evaluated.
Objectives:
To evaluate whether the distribution of trauma centers in a statewide trauma system is associated with SO and to identify clinical and demographic factors that may lead to SO.
Design, Setting, And Participants:
A retrospective cohort study was performed using 2008-2012 data from the Ohio Trauma and Emergency Medical Services registries. All patients taken to level III or nontrauma centers from the scene of the injury with an Injury Severity Score less than 15 and discharged alive were included. Among these patients, those with SO were identified as those who were subsequently transferred to a level I or II trauma center, had no surgical intervention, and were discharged alive within 48 hours of admission. The SO group was analyzed descriptively. Multiple logistic regression was used to identify system-level factors associated with SO. Statistical analysis was performed from August 1, 2017, to January 31, 2018.
Main Outcomes And Measures:
The primary outcome was the occurrence of SO.
Results:
Of 34 494 trauma patients able to be matched in the 2 registries, 7881 (22.9%) met the inclusion criteria, of whom 965 (12.2%) had SO. The median age in the SO group was 40 years (interquartile range, 26-55 years), with 299 women and 666 men. After adjusting for age, sex, comorbidities, injury type, and insurance status, the study found that system-level factors (number of level I or II trauma centers in the region [>1]) were significantly associated with SO (adjusted odds ratio, 1.98; 95% CI, 1.64-2.38; P < .001; area under the curve, 0.89). The reasons for choice of destination by emergency medical services (specifically, choosing the closest facility: adjusted odds ratio, 1.65; 95% CI, 1.37-1.98; P < .001) and use of a field trauma triage protocol (adjusted odds ratio, 2.21; 95% CI, 1.70-2.87; P < .001), significantly increased the likelihood of SO.
Conclusions And Relevance:
This study's findings suggest that the distribution of major trauma centers in the region is significantly associated with SO. Subsequent investigation to identify the optimal number and distribution of trauma centers may therefore be critical. Specific outreach and collaboration of level III trauma centers and nontrauma centers with level I and II trauma centers, along with the use of telemedicine, may provide further guidance to level III trauma centers and nontrauma centers on when to transfer injured patients.
Related Concept Videos
 01:29
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...
 01:55
Secondary Active Transport
 01:11
Secondary Healthcare System
 03:02
Primary and Secondary Growth in Roots and Shoots
 01:31
Factors Affecting Renal Clearance: Drug's Physicochemical Properties and Plasma Levels
One important factor is the drug's molecular size. The kidneys readily excrete smaller molecules below 300 Daltons (Da). On the other hand, molecules weighing between 300 and 500 Da are excreted through both urine and bile. Larger molecules above 500 Da tend to be excreted...
 01:25
Secondary Distribution
In residential areas, 120/240 V single-phase, three-wire service is commonly used for lighting, outlets, and large appliances. Urban areas with high-density loads...