Related Experiment Video
Updated: Feb 3, 2026
Multifocal Electroretinograms
Published on: December 4, 2011
Should Ki67 immunohistochemistry be performed on all lesions in multifocal small intestinal neuroendocrine tumours?
Numbereye Numbere1, Aaron R Huber1, Chanjuan Shi2
1Department of Pathology and Laboratory Medicine, University of Rochester Medical Center, Rochester, NY, USA.

Aims:
Well-differentiated small intestinal neuroendocrine tumours (SI-NETs) are often multifocal, and this has been suggested to impart worse disease-free survival. Practice guidelines have not been established for World Health Organisation (WHO) grading of multiple primary lesions.
Methods And Results:
We identified 68 patients with ileal/jejunal SI-NET for a combined total of 207 primary lesions. Each case was evaluated for patient age and sex; size of all tumours; presence of lymph node metastases, mesenteric tumour deposits or distant metastases; and disease-specific outcome. Ki67 staining was performed on all 207 primary lesions. The relationship between multifocality and clinicopathological factors was compared using Fisher's exact test. Outcome was tested using Cox proportional hazard regression. Forty-two patients had unifocal disease, and 26 had multifocal disease (median five lesions, range = 2-32). Most tumours were WHO grade 1 (201 of 207, 97%). Of the five patients with grades 2/3 tumours, three patients had unifocal disease, one patient had two subcentimetre grade 2 lesions (including the largest) and eight subcentimetre grade 1 lesions, and one patient had one 1.6-cm grade 3 lesion and one subcentimetre grade 1 lesion. There was a positive correlation between tumour size and Ki67 index (coefficient 0.28; 95% confidence interval 0.05-0.52, P = 0.017). There was no significant association between multifocality and nodal metastases, mesenteric tumour deposits, distant metastases or disease-specific survival.
Conclusions:
In patients with multifocal SI-NET, unless a particular lesion has a high mitotic rate, only staining the largest lesion for Ki67 should serve to grade almost all cases accurately. Multifocality does not appear to significantly impact patient survival.

Related Concept Videos
 01:23
Anatomy of the Intestines
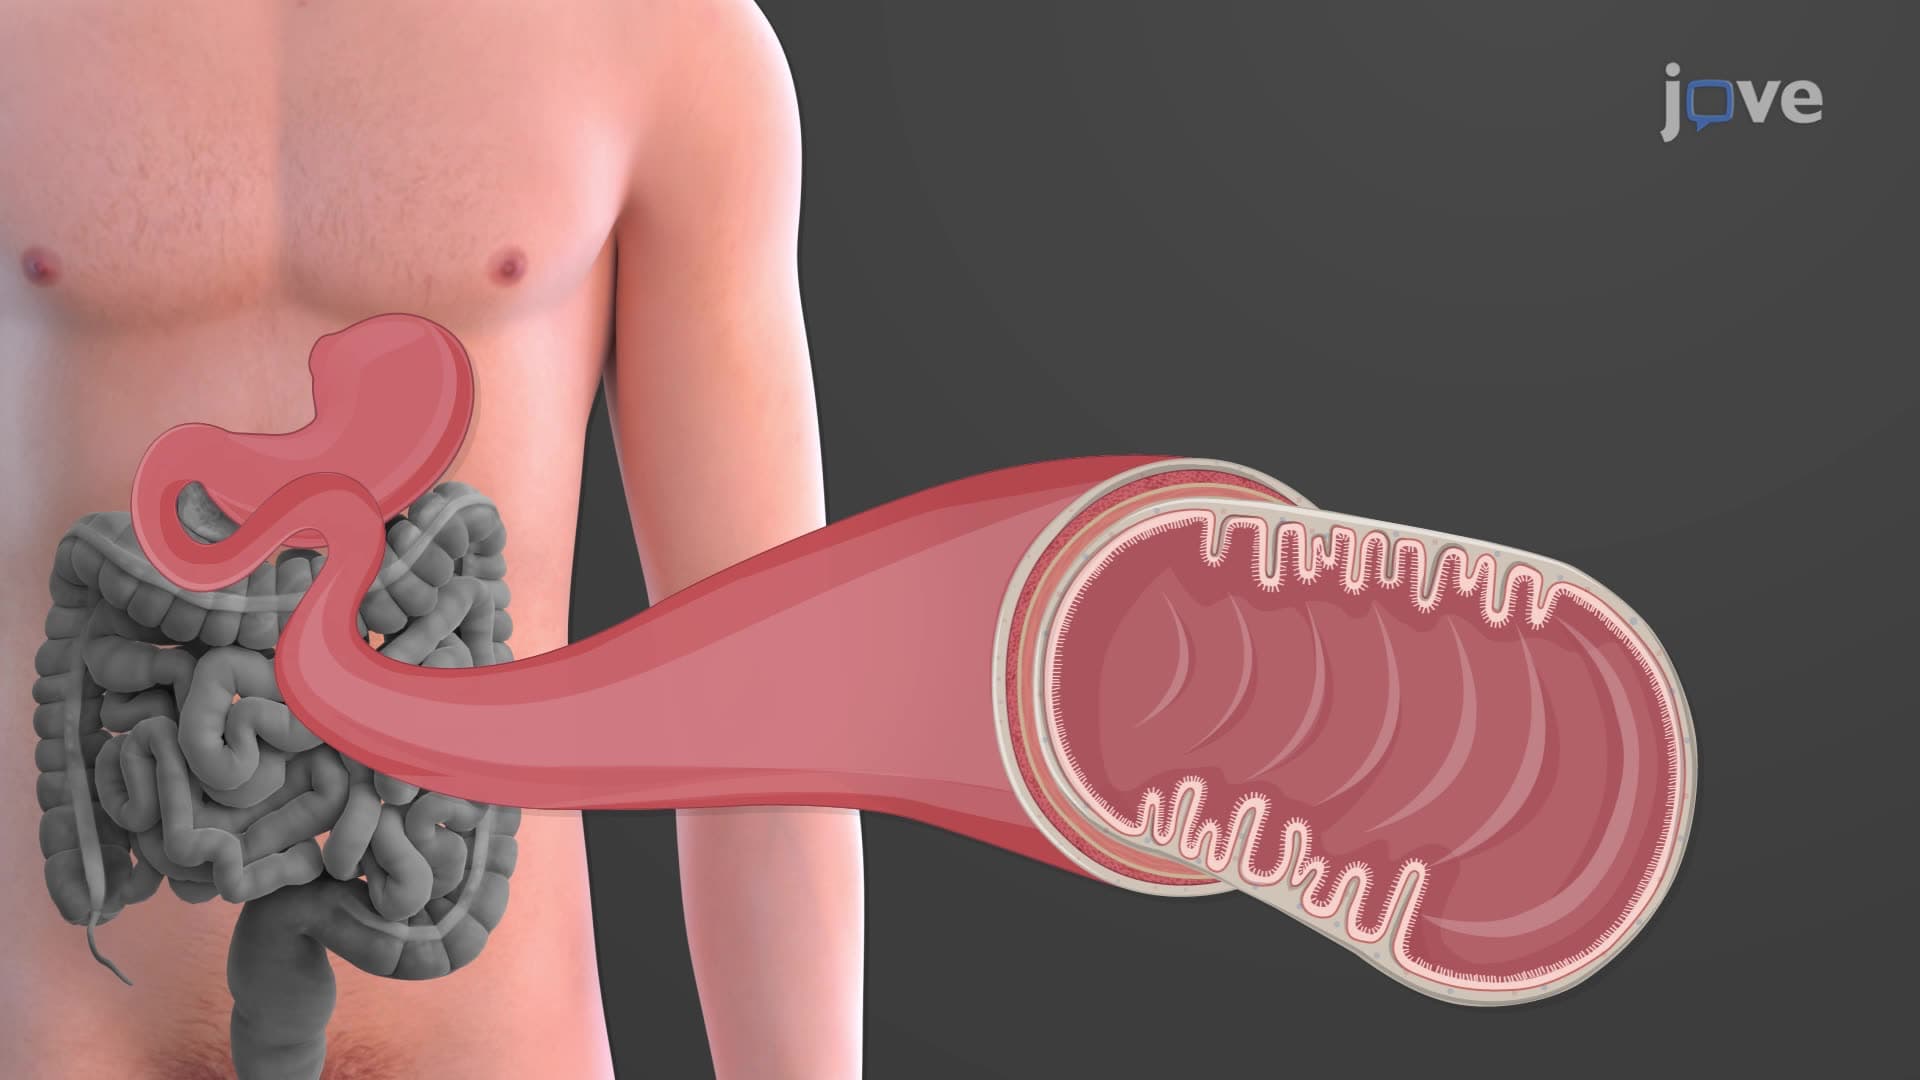
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...
 01:22
Immunocytochemistry and Immunohistochemistry
These...
 01:15
Small Intestine
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique...
 01:09
Large Intestine
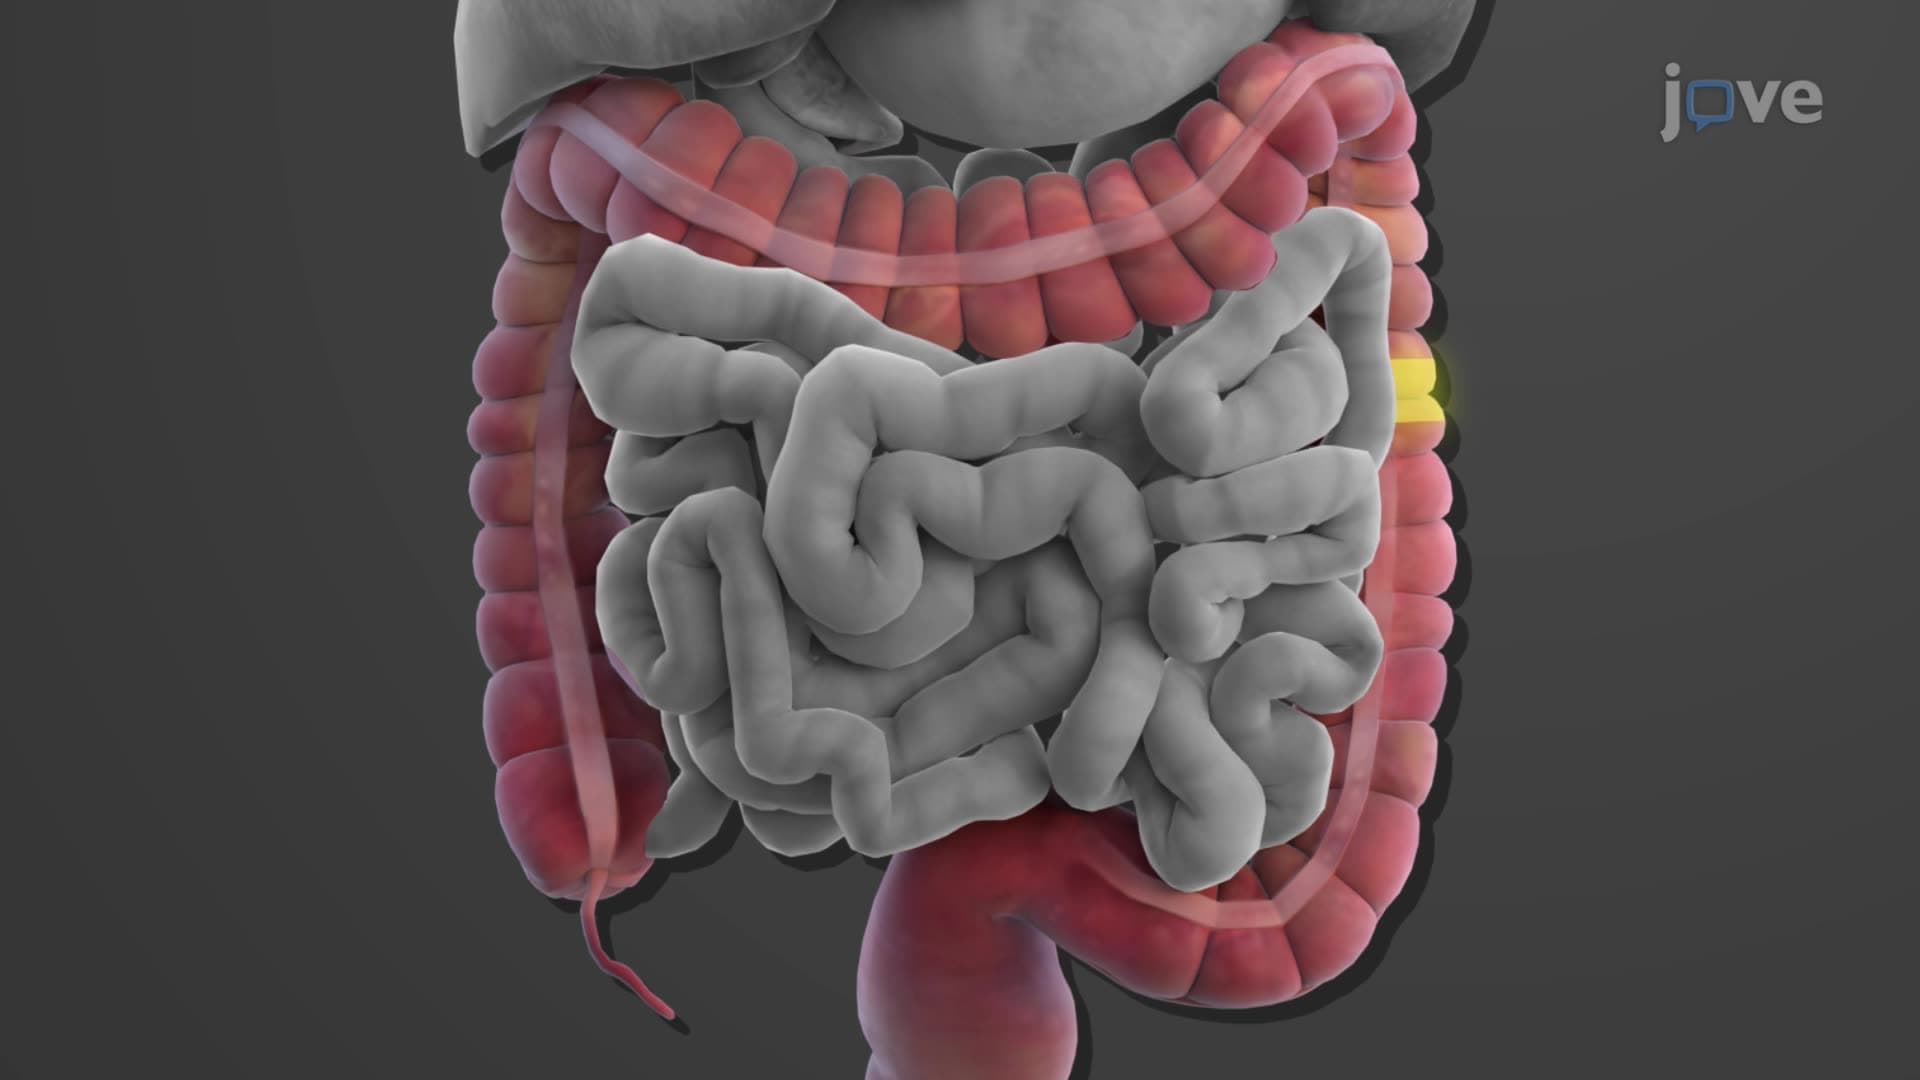
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:26
Histology of the Large Intestine
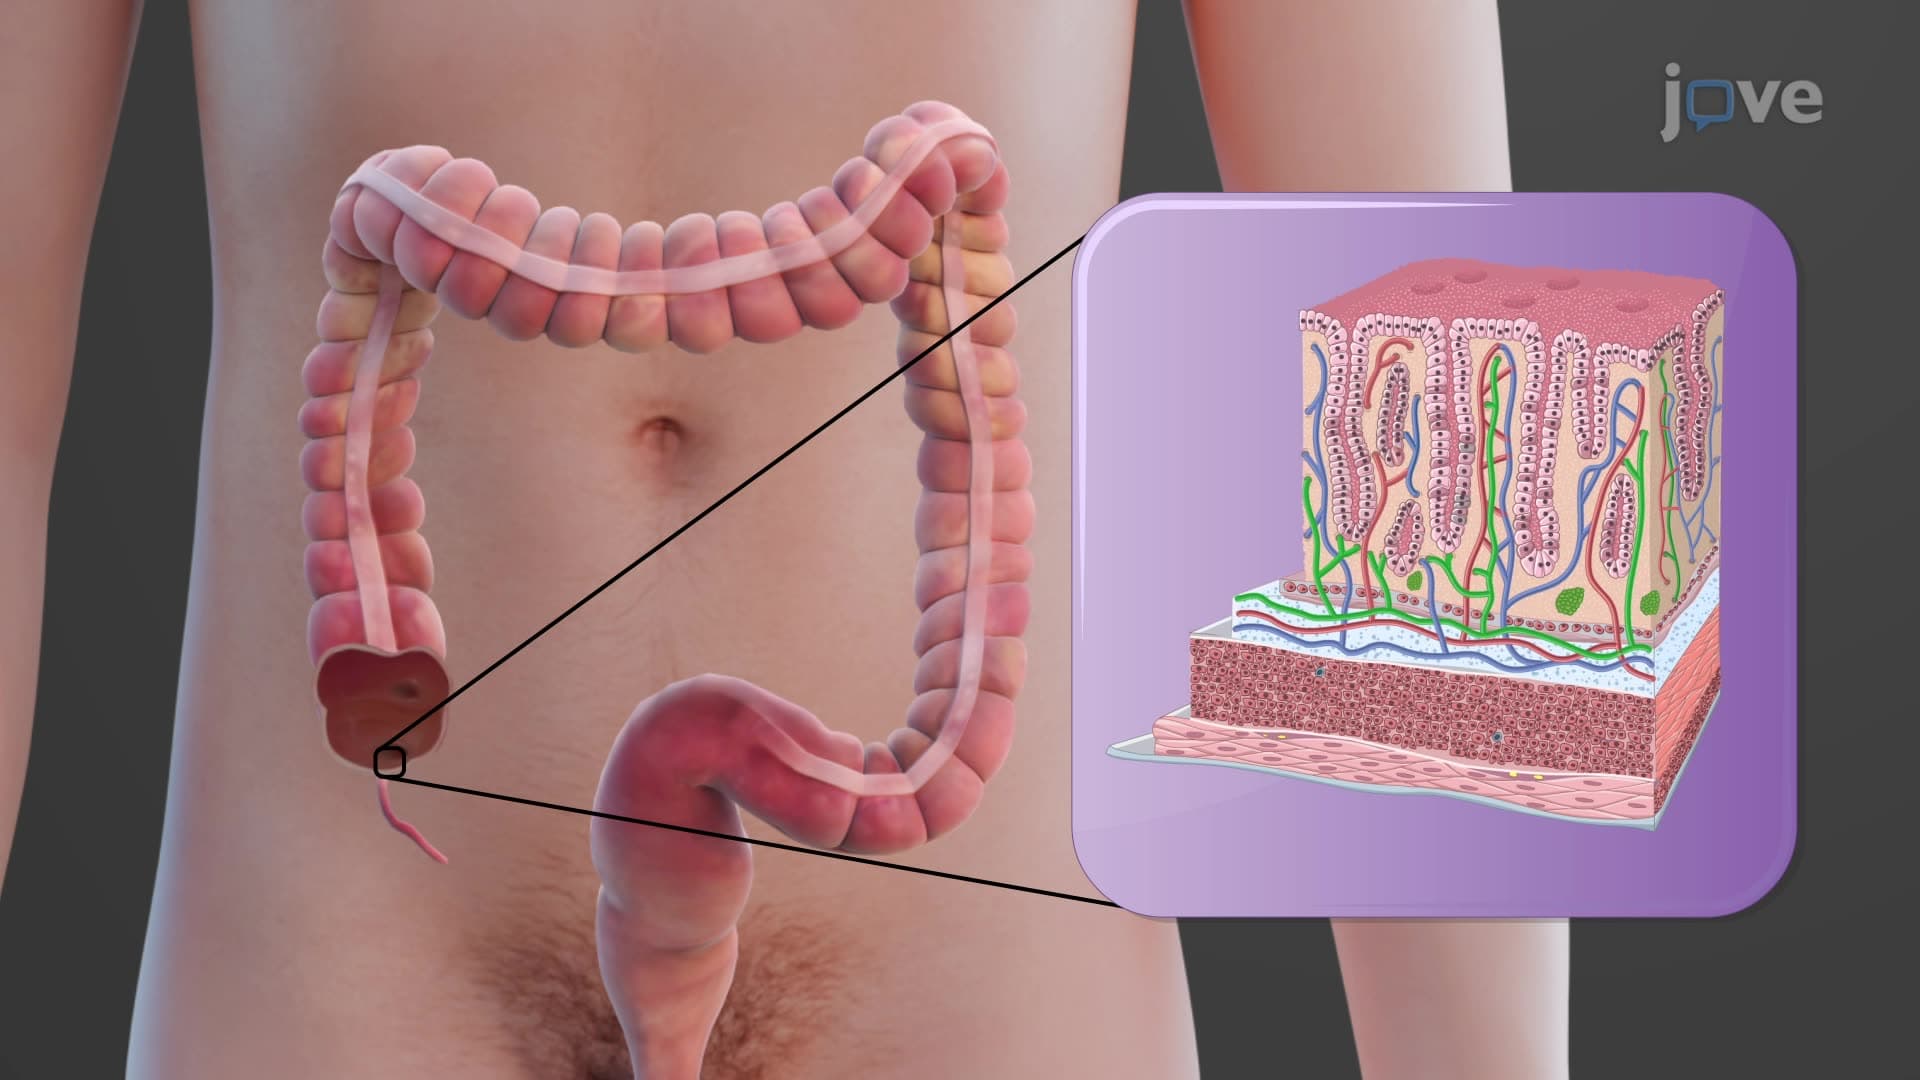
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:27
Histology of the Small Intestine
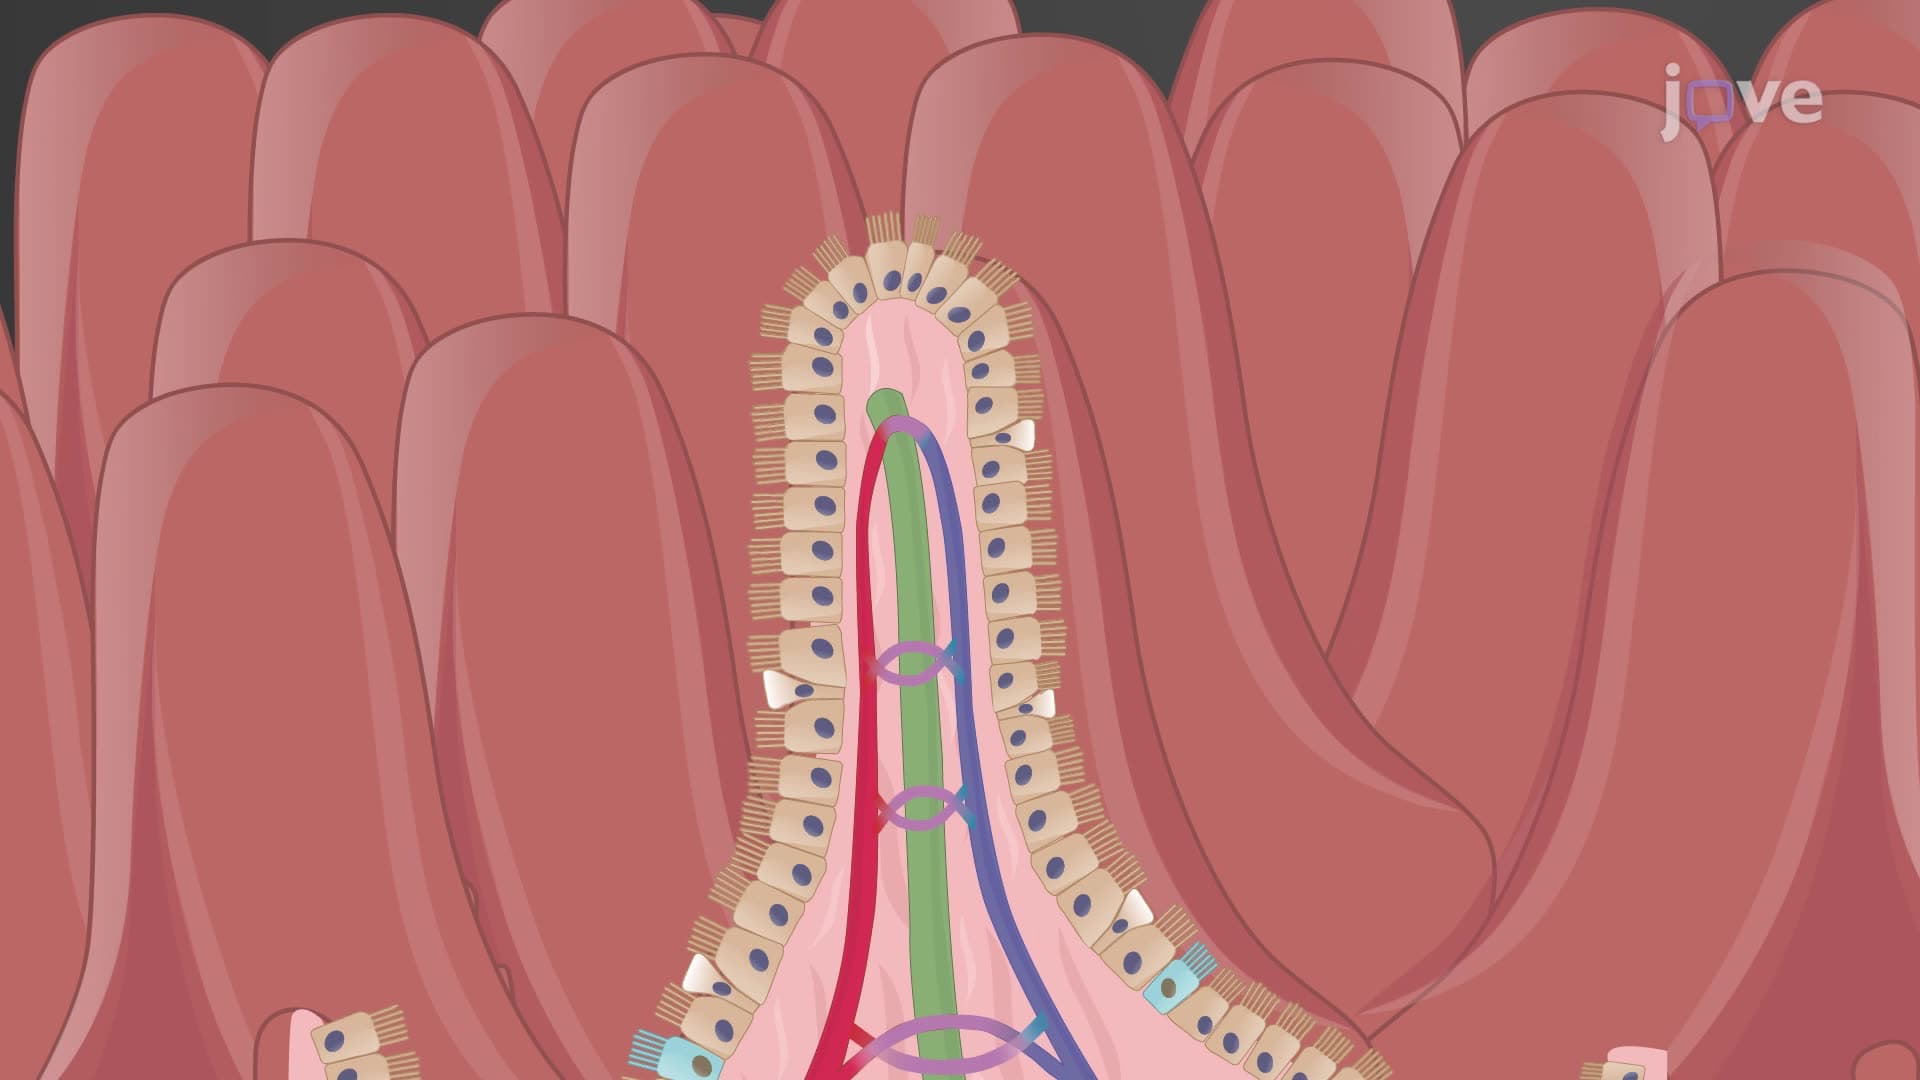
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...