Related Experiment Video
Updated: Feb 3, 2026
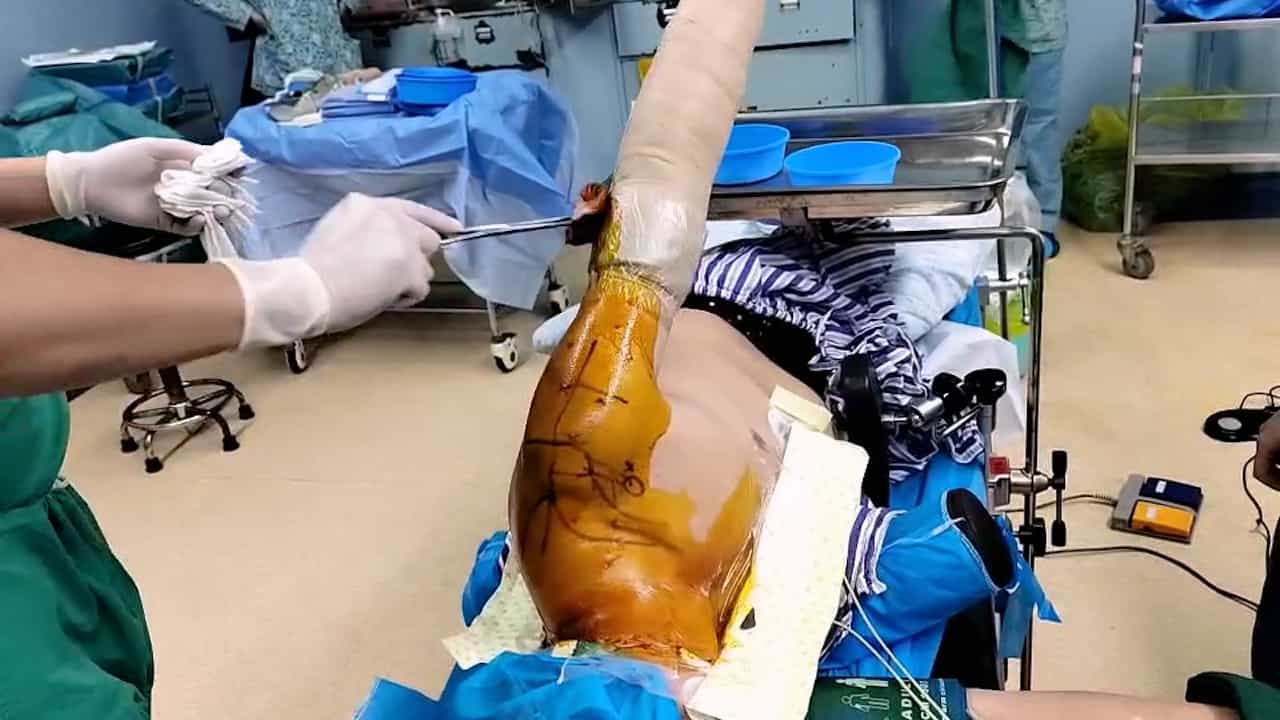

Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025
Does Distal Clavicle Resection Decrease Pain or Improve Shoulder Function in Patients With Acromioclavicular Joint
Jie Wang1, Jian-Xiong Ma, Shao-Wen Zhu
1J. Wang, S.-W. Zhu, H.-B. Jia, X.-L. Ma, Department of Orthopaedics, Tianjin Hospital, Tianjin, China J.-X. Ma, X.-L. Ma, Department of Orthopaedics Institute, Tianjin Hospital, Tianjin, China.

Background:
Acromioclavicular joint arthritis is a common, painful, and often missed diagnosis, and it often accompanies other shoulder conditions such as rotator cuff disease. Whether distal clavicle resection is important to perform in patients undergoing surgery for rotator cuff tears and concomitant acromioclavicular joint arthritis is controversial.
Questions/Purposes:
The purpose of this study was to perform a systematic review and meta-analysis of randomized controlled trials (RCTs) to evaluate the effect of distal clavicle resection on (1) outcome scores; (2) shoulder ROM, joint pain or tenderness, and joint instability; and (3) risk of reoperation among patients treated surgically for rotator cuff tears who had concomitant acromioclavicular joint arthritis.
Methods:
We systematically searched the PubMed, EMBASE, and Cochrane databases to find RCTs that met our eligibility criteria, which, in summary, (1) compared rotator cuff repair plus distal clavicle resection with isolated rotator cuff repair for patients who sustained a full- or partial-thickness rotator cuff tear and concomitant acromioclavicular joint arthritis; and (2) the followup period was at least 2 years. Two reviewers screened the studies, extracted the data and evaluated the methodological quality, and performed data analysis. Statistical heterogeneity among studies was quantitatively evaluated with the I index. No heterogeneity was detected (I = 0%; p = 0.75) in terms of acromioclavicular joint pain or tenderness, Constant score, forward flexion, external rotation, and risk of reoperation, so fixed-effect models were used in these endpoints. Heterogeneity was moderate for the American Shoulder and Elbow Surgeons (ASES) score (I = 53%; p = 0.12) and low for the visual analog scale (VAS) score (I = 35%; p = 0.22), so random-effect models were used in these endpoints. Subgroup analysis was stratified by the symptom of acromioclavicular joint arthritis. Three RCTs with 208 patients were included. We evaluated the risk of bias using the Cochrane risk-of-bias tool; in aggregate, the three RCTs included showed low to intermediate risk, although not all parameters of the Cochrane tool could be assessed for all studies.
Results:
There was no difference between the distal clavicle resection plus rotator cuff repair group and the isolated rotator cuff repair group in ASES score (mean difference =1.41; 95% confidence interval [CI], -3.37 to 6.18; p = 0.56) nor in terms of the VAS score and Constant score. Likewise, we found no difference in ROM of the shoulder (forward flexion, internal rotation, and external rotation) or acromioclavicular joint pain or tenderness between the groups (pooled results of acromioclavicular joint pain or tenderness: risk ratio [RR], 1.59; 95% CI, 0.67-3.78; p = 0.30). Acromioclavicular joint instability was only detected in the rotator cuff repair plus distal clavicle resection group. Finally, we found no difference in the proportion of patients undergoing repeat surgery between the study groups (pooled results of risk of reoperation for the rotator cuff repair plus distal clavicle resection and isolated rotator cuff repair: one of 52 versus two of 78; RR, 0.86; 95% CI, 0.11-6.48; p = 0.88).
Conclusions:
Distal clavicle resection in patients with rotator cuff tears did not result in better clinical outcome scores or shoulder ROM and was not associated with a lower risk of reoperation. Distal clavicle resection might cause acromioclavicular joint instability in patients with rotator cuff tears and concomitant asymptomatic acromioclavicular joint arthritis. Arthroscopic distal clavicle resection is not recommended in patients with rotator cuff tears and concomitant acromioclavicular joint arthritis. Additional well-designed RCTs with more participants, long-term followup, and data on patient-reported outcomes are needed.
Level Of Evidence:
Level I, therapeutic study.
Related Concept Videos
 01:27
Decreasing Function
 01:09
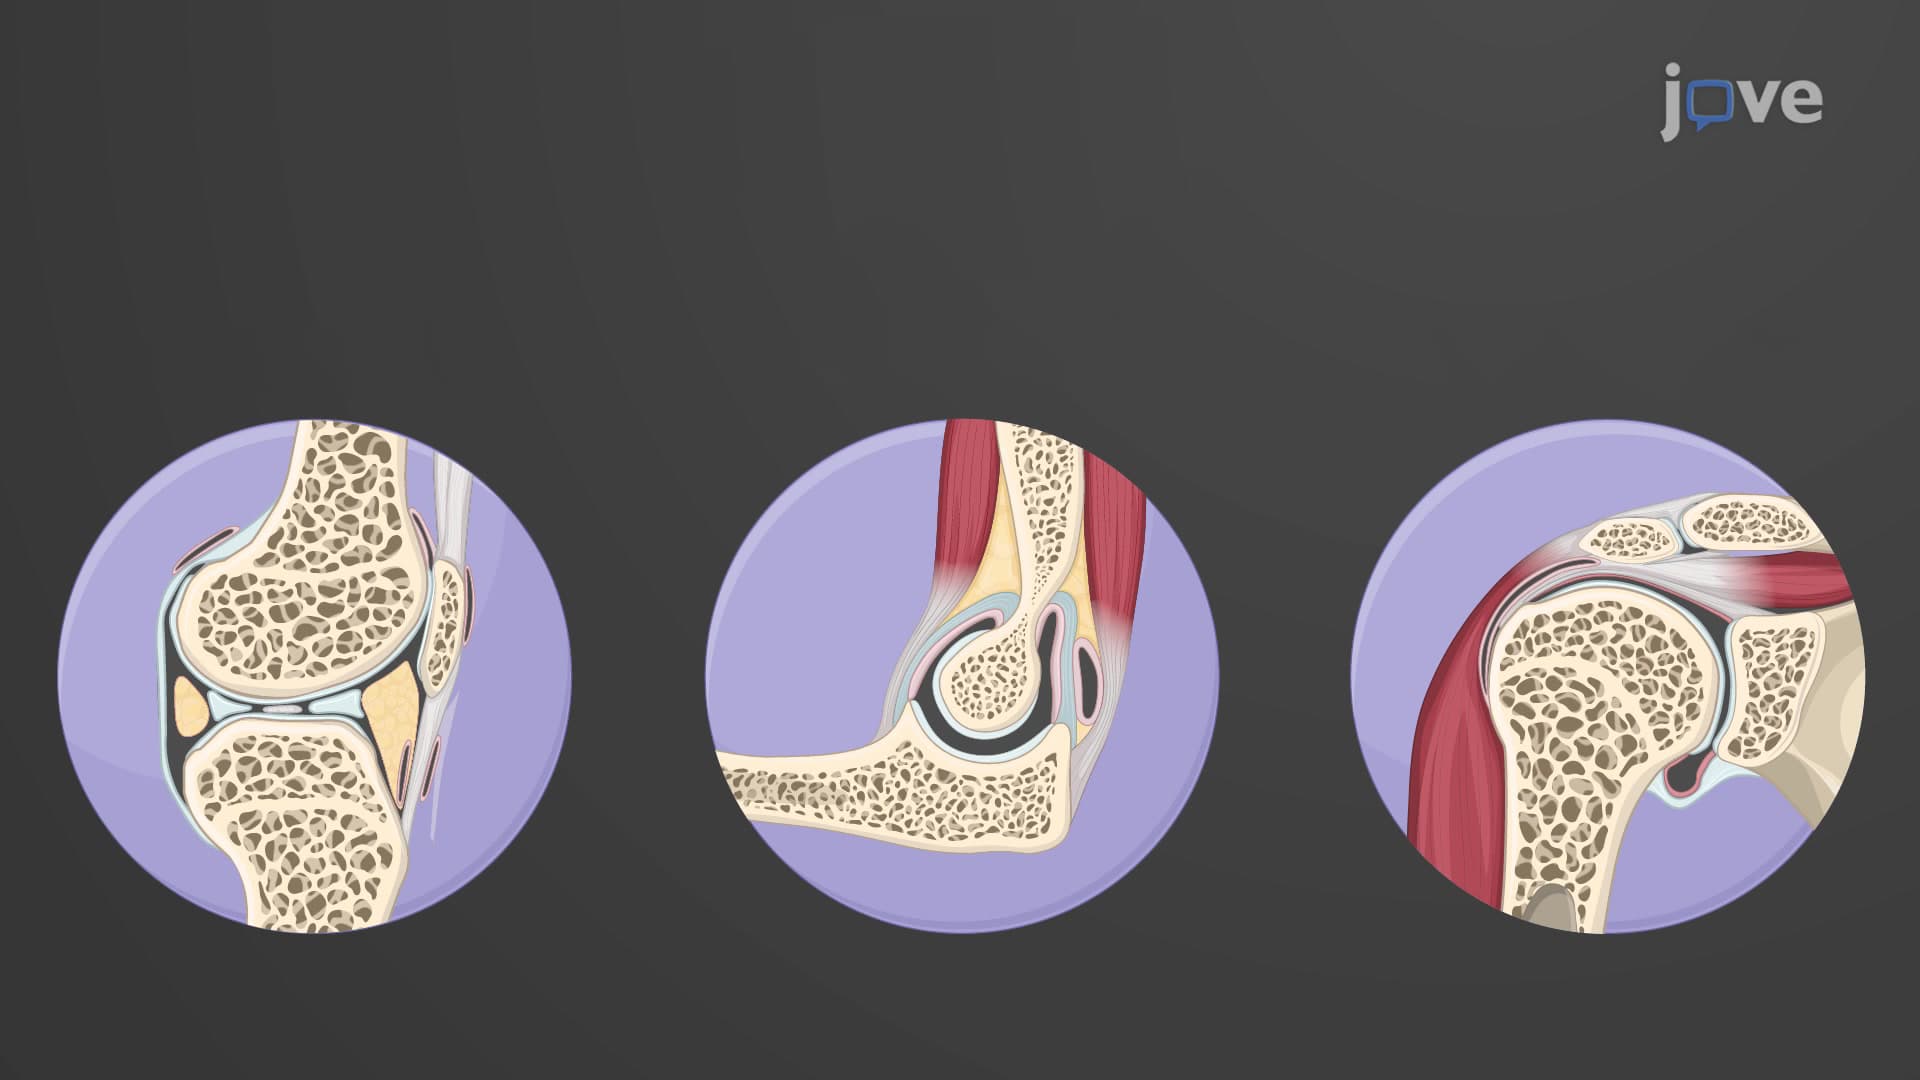
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:25
Relative Motion Analysis using Rotating Axes
However, to express the relative position of point B relative to point A, an additional frame of reference, denoted as x'y', is necessary. This additional frame not only translates but also rotates relative to the fixed frame, making it...
 01:22
Relative Motion Analysis using Rotating Axes - Acceleration
Time differentiation is...
 01:29
Decreased Body Temperature