Related Experiment Video
Updated: Feb 3, 2026


Measurement of the Hepatic Venous Pressure Gradient and Transjugular Liver Biopsy
Published on: June 18, 2020
Circulating PD-1hiCXCR5+CD4+ T cells are associated with a decrease in hepatitis B surface antigen levels in patients
1Department of Infectious Diseases, Institute for Viral Hepatitis, The Key Laboratory of Molecular Biology for Infectious Diseases, Chinese Ministry of Education, The Second Affiliated Hospital of Chongqing Medical University, Chongqing, China.

Given the B helper function of follicular T helper (Tfh) cells and peripheral T helper (Tph) cells, we researched the roles of circulating PD-1hiCXCR5+CD4+ T cells and PD-1hiCXCR5-CD4+ T cells in the decrease in hepatitis B surface antigen (HBsAg) levels and hepatitis B virus (HBV) clearance in patients with chronic hepatitis B (CHB). In the present study, the frequencies of PD-1hiCXCR5+CD4+ T cells and PD-1hiCXCR5-CD4+ T cells measured by flow cytometry were significantly higher in patients with CHB than that in healthy controls (HCs). Our longitudinal study did not reveal significant differences in the frequencies of both cell populations before and after 48 weeks of peginterferon-α (PEG-IFN-α) therapy. However, repeated measurements of serum HBsAg levels revealed significantly lower HBsAg levels over time in patients who exhibited an increase in the frequency of PD-1hiCXCR5+CD4+ T cells after PEG-IFN-α treatment. In addition, the increase in the frequency of PD-1hiCXCR5+CD4+ T cells exerted a significant positive effect on the HBsAg level, which decreased to ≤2 Log10 IU/mL and ≤3 Log10 IU/mL at the end of treatment. However, no significant difference in HBsAg levels was observed over time, regardless of whether the frequency of circulating PD-1hiCXCR5-CD4+ T cells was elevated. Repeated measurements of the HBV DNA concentration did not show significant differences between patients exhibiting changes in the frequencies of these two cell subsets and HBV DNA clearance. Overall, circulating PD-1hiCXCR5+CD4+ T cells and PD-1hiCXCR5-CD4+ T cells may be involved in the immune landscape of patients with a chronic HBV infection. Moreover, PD-1hiCXCR5+CD4+ T cells are associated with decreased HBsAg levels in patients with CHB who are receiving peginterferon-α therapy.
Given the B helper function of follicular T helper (Tfh) cells and peripheral T helper (Tph) cells, we researched the roles of circulating PD-1hiCXCR5+CD4+ T cells and PD-1hiCXCR5-CD4+ T cells in the decrease in hepatitis B surface antigen (HBsAg) levels and hepatitis B virus (HBV) clearance in patients with chronic hepatitis B (CHB). In the present study, the frequencies of PD-1hiCXCR5+CD4+ T cells and PD-1hiCXCR5-CD4+ T cells measured by flow cytometry were significantly higher in patients with CHB than that in healthy controls (HCs). Our longitudinal study did not reveal significant differences in the frequencies of both cell populations before and after 48 weeks of peginterferon-α (PEG-IFN-α) therapy. However, repeated measurements of serum HBsAg levels revealed significantly lower HBsAg levels over time in patients who exhibited an increase in the frequency of PD-1hiCXCR5+CD4+ T cells after PEG-IFN-α treatment. In addition, the increase in the frequency of PD-1hiCXCR5+CD4+ T cells exerted a significant positive effect on the HBsAg level, which decreased to ≤2 Log10 IU/mL and ≤3 Log10 IU/mL at the end of treatment. However, no significant difference in HBsAg levels was observed over time, regardless of whether the frequency of circulating PD-1hiCXCR5-CD4+ T cells was elevated. Repeated measurements of the HBV DNA concentration did not show significant differences between patients exhibiting changes in the frequencies of these two cell subsets and HBV DNA clearance. Overall, circulating PD-1hiCXCR5+CD4+ T cells and PD-1hiCXCR5-CD4+ T cells may be involved in the immune landscape of patients with a chronic HBV infection. Moreover, PD-1hiCXCR5+CD4+ T cells are associated with decreased HBsAg levels in patients with CHB who are receiving peginterferon-α therapy.
More Related Videos


Related Concept Videos
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:21
Hepatic Portal System
At its core, the hepatic portal vein is the result of a confluence of the superior and inferior mesenteric veins along with the splenic vein. Each of these veins has a unique role. The superior mesenteric vein is...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:16
Hepatic Drug Excretion: Influencing Factors
 01:14
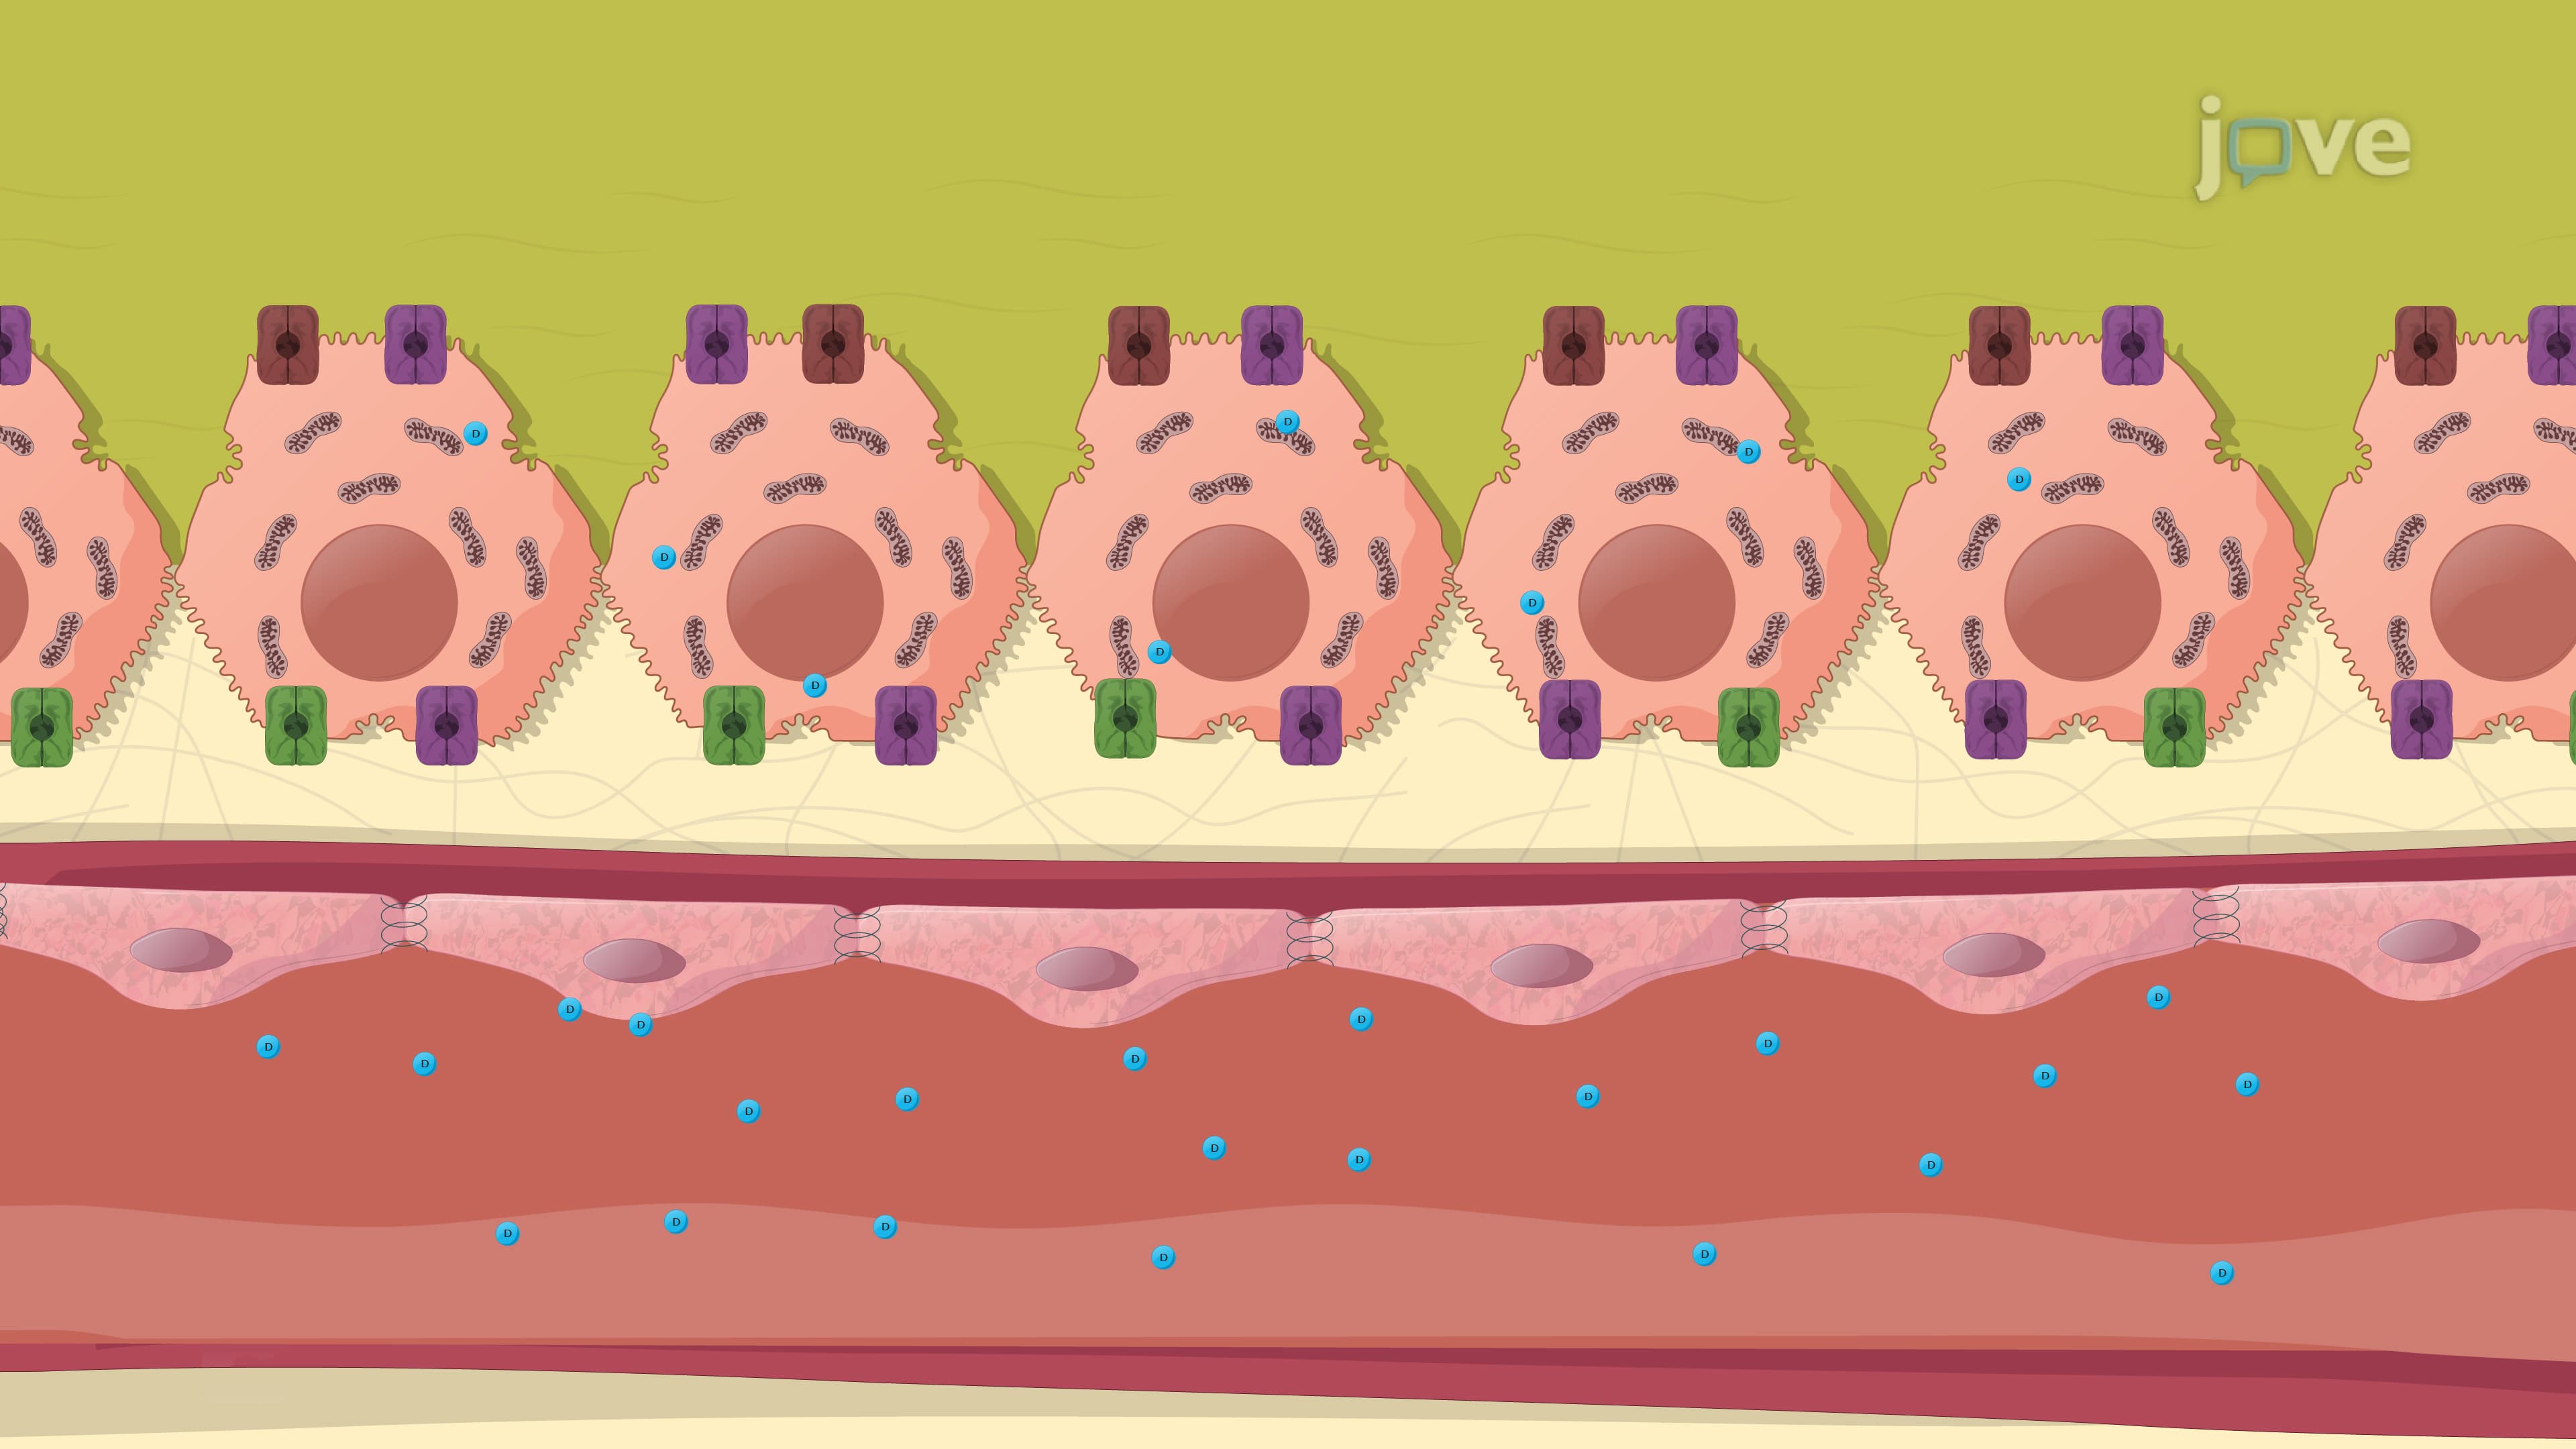
Hepatic Drug Clearance: Role of Transporters
 01:17
Hepatic Drug Excretion: Enterohepatic Cycling
Post-release drugs and metabolites can be reabsorbed into the body from the intestine. For conjugated metabolites like glucuronides, reabsorption requires enzymatic hydrolysis by intestinal microflora. This...