Update on extended treatment for venous thromboembolism
Related Experiment Video
Updated: Feb 3, 2026
Porcine Liver Transplantation Without Veno-Venous Bypass As an Extended Criteria Donor Model
Published on: August 17, 2022
Eduardo Peñaloza-Martínez1, Pablo Demelo-Rodríguez1,2,3, Marco Proietti4,5,6
1a Venous Thromboembolism Unit, Internal Medicine Department , Hospital General Universitario Gregorio Marañón , Madrid , Spain.

The importance of assessing the probability of venous thromboembolism recurrence, a condition that includes deep vein thrombosis and pulmonary embolism, lies in the fact that it is the most important factor in deciding the duration of anticoagulant treatment. Risk of recurrence depends mostly on the presence of a risk factor for developing venous thromboembolism, with patients with unprovoked events being at the higher risk of recurrence. The risk of recurrence needs to be balanced with the risk of bleeding and the potential severity of these thrombotic and hemorrhagic events. In patients with an unprovoked venous thromboembolism who complete treatment for the acute (first 10 days) and post-acute phase of the disease (from day 10 to 3-6 months), the decision has to be made regarding prolonged antithrombotic therapy to prevent recurrences. The main goal of extended treatment is preventing recurrences with a safety profile in terms of bleeding risk. Many therapeutic options are now available for these patients, including antiplatelet therapy with aspirin or direct oral anticoagulants. Moreover, apixaban and rivaroxaban at prophylactic doses have demonstrated efficacy in preventing recurrences with a low risk of bleeding. Key messages Extending treatment (longer than 3-6 months) is challenging in patients with venous thromboembolism (VTE) and depend on the risk of venous thromboembolism recurrence, the bleeding risk and patient and physician preferences. Anticoagulation treatment should be stopped in patients with provoked VTE and in those with unprovoked VTE and a high bleeding risk after an initial period of 3-6 months. There are some therapeutic alternatives (including Aspirin and low dose of some NOACs) to reduce venous thromboembolism recurrence risk in patients with unprovoked VTE and a low bleeding risk for extended treatment of VTE (after an initial period of 3-6 months).
The importance of assessing the probability of venous thromboembolism recurrence, a condition that includes deep vein thrombosis and pulmonary embolism, lies in the fact that it is the most important factor in deciding the duration of anticoagulant treatment. Risk of recurrence depends mostly on the presence of a risk factor for developing venous thromboembolism, with patients with unprovoked events being at the higher risk of recurrence. The risk of recurrence needs to be balanced with the risk of bleeding and the potential severity of these thrombotic and hemorrhagic events. In patients with an unprovoked venous thromboembolism who complete treatment for the acute (first 10 days) and post-acute phase of the disease (from day 10 to 3-6 months), the decision has to be made regarding prolonged antithrombotic therapy to prevent recurrences. The main goal of extended treatment is preventing recurrences with a safety profile in terms of bleeding risk. Many therapeutic options are now available for these patients, including antiplatelet therapy with aspirin or direct oral anticoagulants. Moreover, apixaban and rivaroxaban at prophylactic doses have demonstrated efficacy in preventing recurrences with a low risk of bleeding. Key messages Extending treatment (longer than 3-6 months) is challenging in patients with venous thromboembolism (VTE) and depend on the risk of venous thromboembolism recurrence, the bleeding risk and patient and physician preferences. Anticoagulation treatment should be stopped in patients with provoked VTE and in those with unprovoked VTE and a high bleeding risk after an initial period of 3-6 months. There are some therapeutic alternatives (including Aspirin and low dose of some NOACs) to reduce venous thromboembolism recurrence risk in patients with unprovoked VTE and a low bleeding risk for extended treatment of VTE (after an initial period of 3-6 months).
Related Concept Videos
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...
 01:30
Venous Thrombosis I: Introduction
 01:07
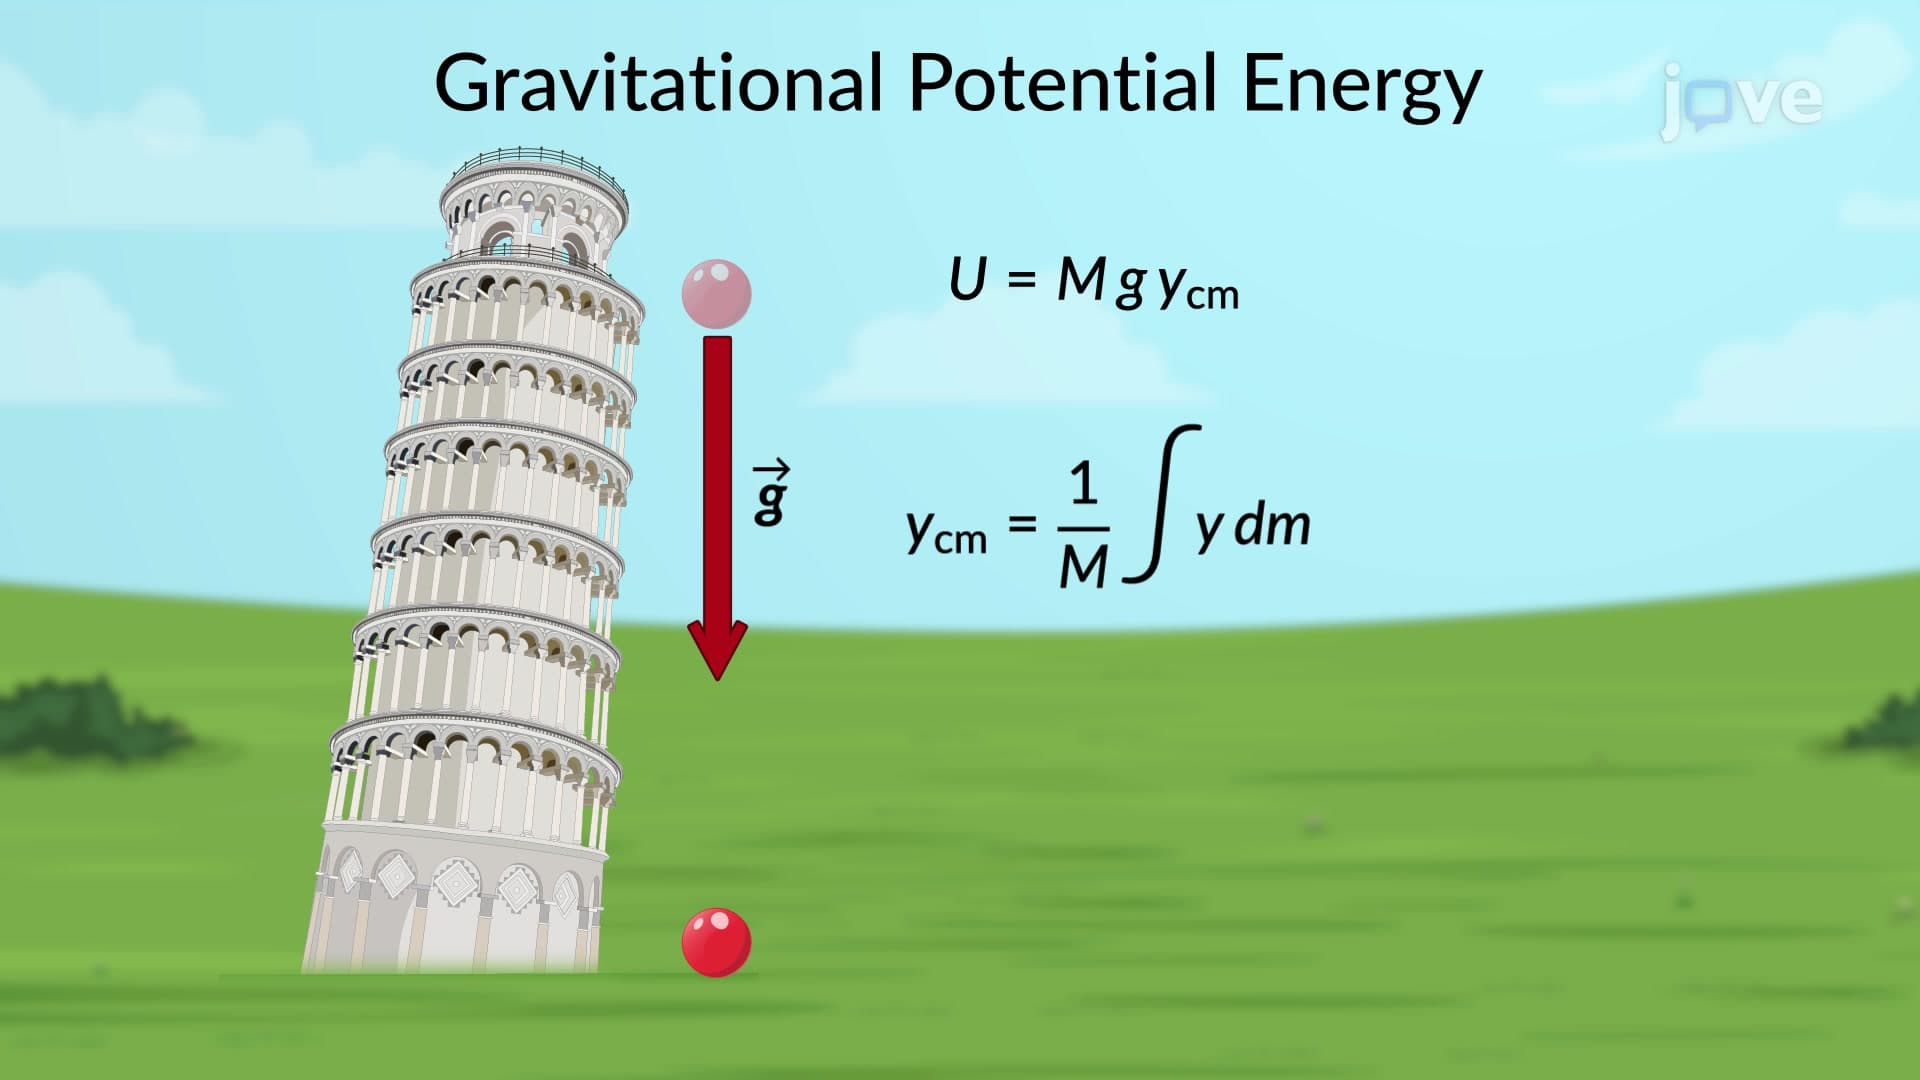
Gravitational Potential Energy for Extended Objects
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies