Related Experiment Video
Updated: Feb 3, 2026

Author Spotlight: Assessing the Reliability of Doppler Ultrasound in Measuring Leg Blood Flow
Published on: December 15, 2023
Exercise-induced leg pain in athletes: diagnostic, assessment, and management strategies
Heinz Lohrer1, Nikolaos Malliaropoulos2, Vasileios Korakakis3
1a European SportsCare Network (ESN) - Zentrum für Sportorthopädie , Wiesbaden-Nordenstadt , Germany.

Abstract:
The purpose of this review is to describe and critically evaluate current knowledge regarding diagnosis, assessment, and management of chronic overload leg injuries which are often non-specific and misleadingly referred to as 'shin splints'. We aimed to review clinical entities that come under the umbrella term 'Exercise-induced leg pain' (EILP) based on current literature and systematically searched the literature. Specifically, systematic reviews were included. Our analyses demonstrated that current knowledge on EILP is based on a low level of evidence. EILP has to be subdivided into those with pain from bone stress injuries, pain of osteo-fascial origin, pain of muscular origin, pain due to nerve compression and pain due to a temporary vascular compromise. The history is most important. Questions include the onset of symptoms, whether worse with activity, at rest or at night? What exacerbates it and what relieves it? Is the sleep disturbed? Investigations merely confirm the clinical diagnosis and/or differential diagnosis; they should not be solely relied upon. The mainstay of diagnosing bone stress injury is MRI scan. Treatment is based on unloading strategies. A standard for confirming chronic exertional compartment syndrome (CECS) is the dynamic intra-compartmental pressure study performed with specific exercises that provoke the symptoms. Surgery provides the best outcome. Medial tibial stress syndrome (MTSS) presents a challenge in both diagnosis and treatment especially where there is a substantial overlap of symptoms with deep posterior CECS. Conservative therapy should initially aim to correct functional, gait, and biomechanical overload factors. Surgery should be considered in recalcitrant cases. MRI and MR angiography are the primary investigative tools for functional popliteal artery entrapment syndrome and when confirmed, surgery provides the most satisfactory outcome. Nerve compression is induced by various factors, e.g., localized fascial entrapment, unstable proximal tibiofibular joint (intrinsic) or secondary by external compromise of the nerve, e.g., tight hosiery (extrinsic). Conservative is the treatment of choice. The localized fasciotomy is reserved for recalcitrant cases.

Related Concept Videos
 01:25
Analgesia and Pain Management
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:11
Assessing Blood pressure in the Leg
Preparation:
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:23
Muscles that Move the Leg
Anterior Compartment
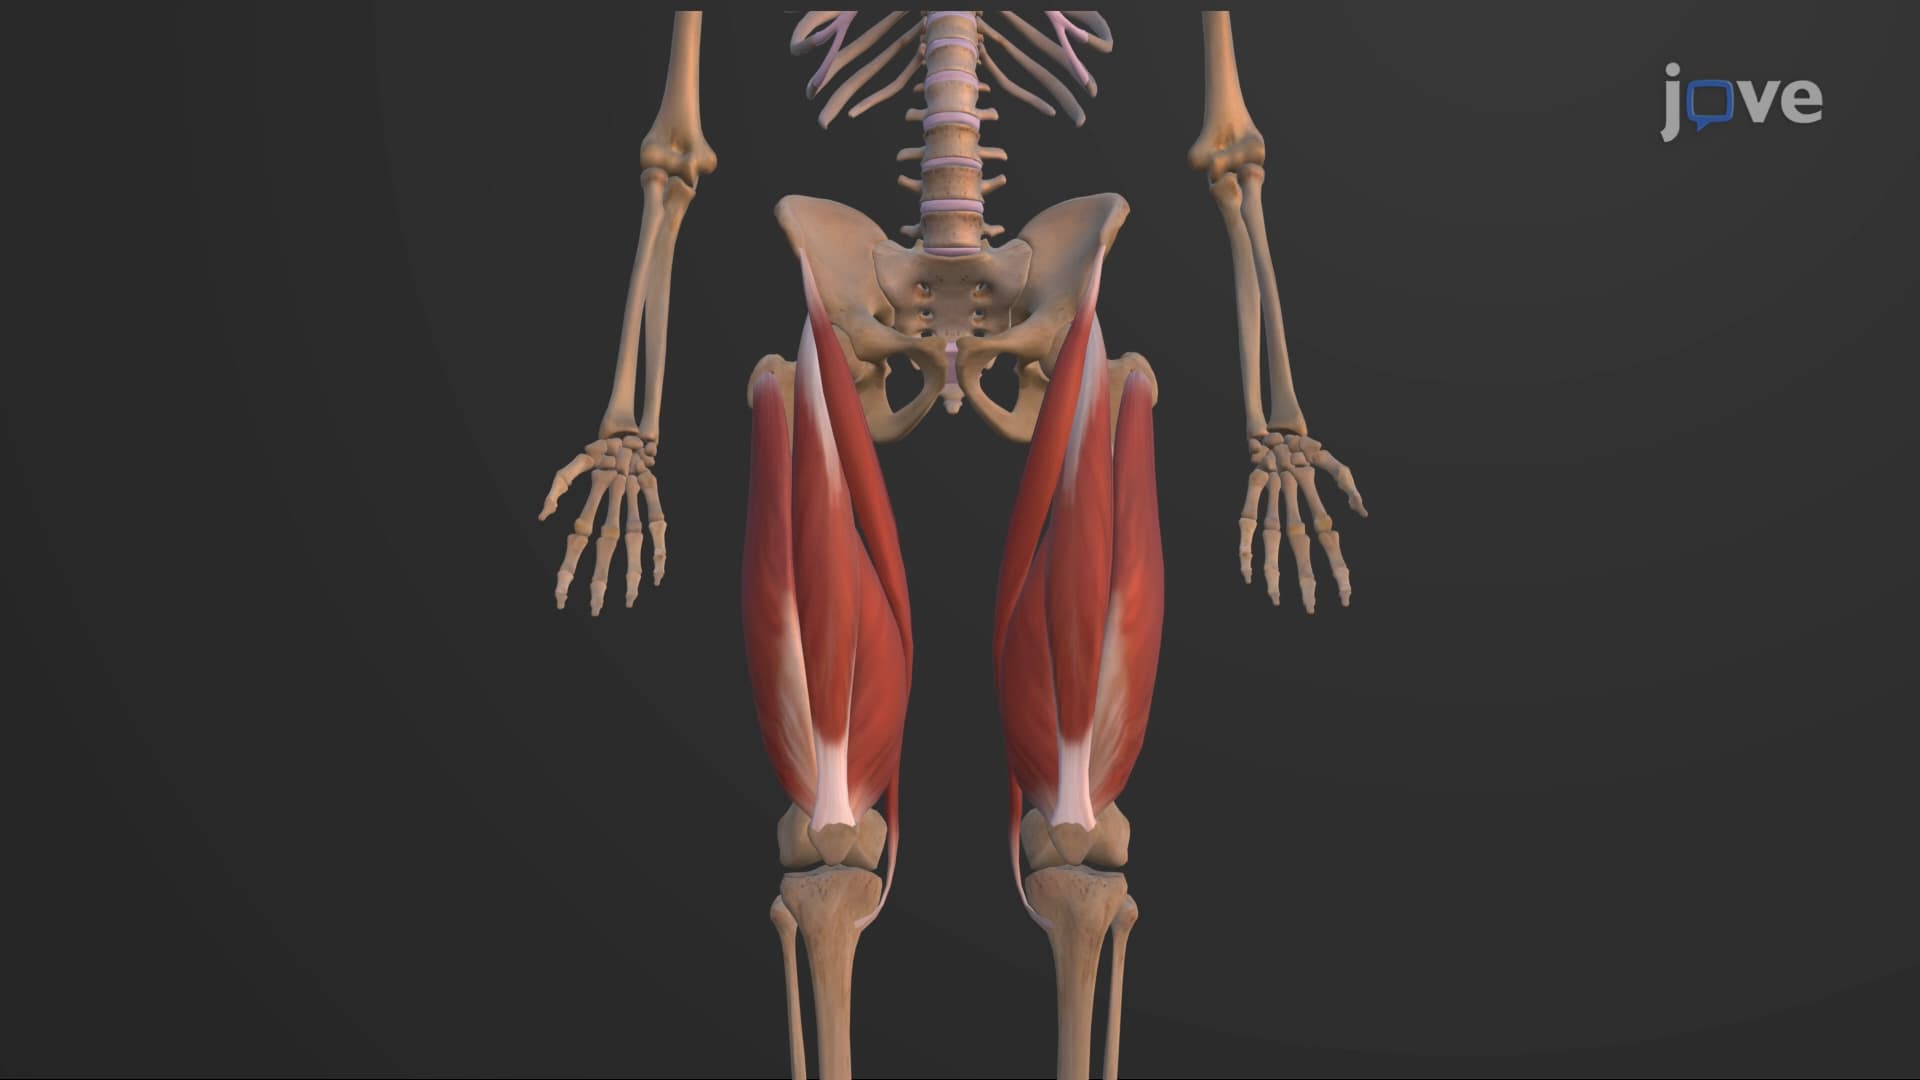
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed...