Related Experiment Video
Updated: Feb 3, 2026
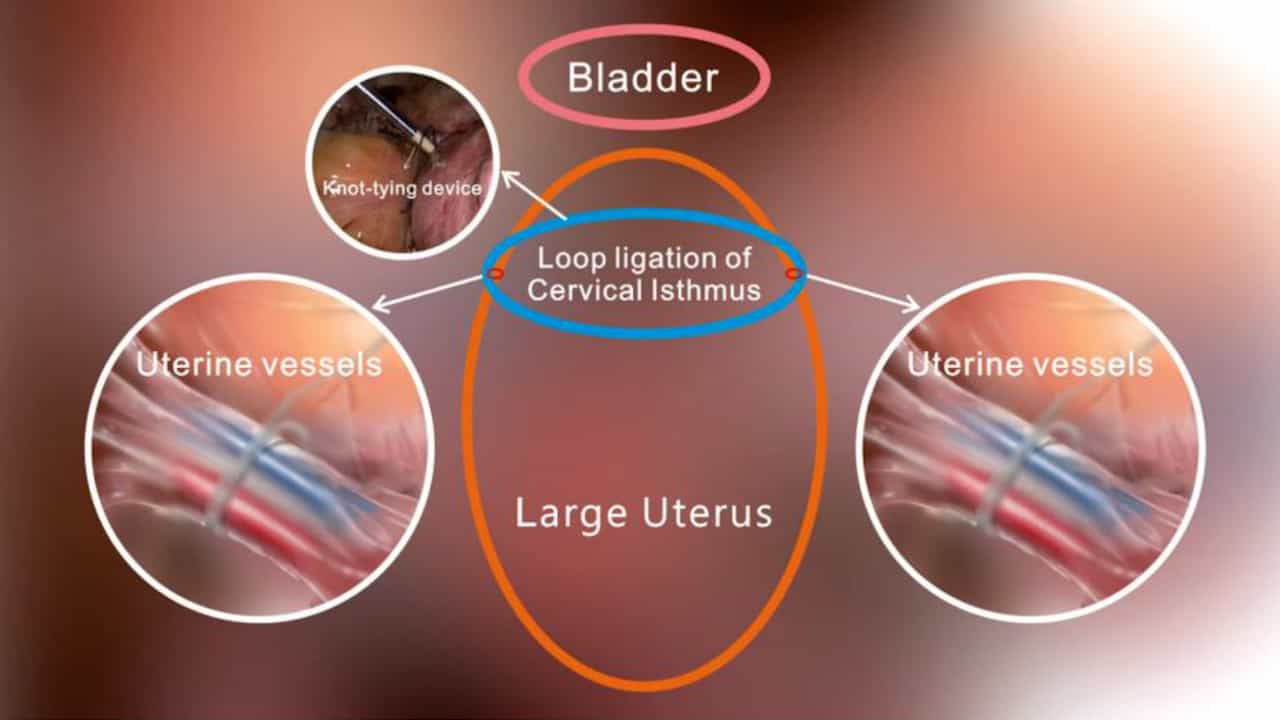
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
A laparovaginal strategy to avoid bladder injury during laparoscopic-assisted vaginal hysterectomy in cases with
Ramkrishna Purohit1, Jay Gopal Sharma1, Devajani Meher1
1Department of Obstetrics and Gynecology, Purohit General Hospital, Bargarh, Orissa, India, ramkrishnapurohit@hotmail.com.

Background:
Laparoscopic hysterectomy for benign indications in cases with ventrofixed uterus following previous cesarean section (CS) increases the surgeon's concern of bladder injury. The present study describes a laparovaginal strategy to avoid bladder injury during laparoscopic-assisted vaginal hysterectomy (LAVH) in cases with ventrofixed uterus following previous CS.
Methods:
In a retrospective study conducted in our private general hospital, we included consecutive cases of laparoscopically confirmed ventrofixed uterus associated with previous CS. These were from the cases who underwent LAVH for benign indications. Cases with uterus size >16 weeks of gestation were excluded. Patients' clinical, intraoperative and postoperative characteristics were studied to evaluate the feasibility of the described laparovaginal strategy to prevent bladder injury during LAVH in cases with ventrofixed uterus.
Results:
A total of 35 cases with ventrofixed uterus underwent LAVH during the study. Six (17.14%) cases had a history of one CS, while 29 (82.86%) cases had a history of previous two or more CSs. A supravesical loose fatty tissue plane (supravesical space) indicating reach to the bladder wall during laparoscopic lysis of the uterus from the anterior abdominal wall was successfully demonstrated in all the cases. The bladder flap preparation was avoided. Uterovesical adhesions were dissected by posteroanterior approach during vaginal phase of LAVH in all the cases. LAVH was successfully performed in all the cases. None of the cases had bladder injury, laparotomic conversion or other major complications. Mean operating time for LAVH was 149.71±38.36 minutes (70-200 minutes). Mean uterine specimen weight was 162.85±92.57 g (60-500 g). Mean postoperative hospital stay was 2.42±0.73 days (2-5 days).
Conclusion:
In spite of severe adhesions in cases with a ventrofixed uterus following previous CS, bladder injury can be avoided during LAVH by the described laparovaginal approach in the present study.
Short Synopsis:
The described laparovaginal approach may avoid bladder injury during laparoscopic-assisted vaginal hysterectomy in cases with a ventrofixed uterus following previous cesarean section.
Related Concept Videos
 01:14
Frustration and Conflict: Avoidance-Avoidance, Double-Approach Avoidance
 01:18
Uterus and Cervix
The uterus is securely anchored within the pelvic cavity by paired broad ligaments on either side. It is further stabilized by three pairs...
 01:19
Histology of the Uterus
The endometrium is the...
 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:26
Personality Disorders: Narcissistic and Avoidant
Characteristics of Narcissistic Personality Disorder
Narcissistic individuals exhibit an inflated sense of self-importance and an excessive need for admiration. They are often...
 01:14
Avoidance Learning and Learned Helplessness
Avoidance learning occurs when an organism learns that a specific behavior can prevent an unpleasant outcome. For example, a student who receives a bad grade may start studying harder to avoid future poor grades. This behavior persists even when the negative outcome is no longer present. Avoidance learning is powerful because it maintains behavior in the absence of the...