Related Experiment Video
Updated: Feb 3, 2026
Identification and Protection of the Recurrent Laryngeal Nerve during Transoral Robotic Thyroidectomy
Published on: October 24, 2025
A Critical Reappraisal of Primary and Recurrent Advanced Laryngeal Cancer Staging
Luca Giovanni Locatello1, Michele Pietragalla2, Cecilia Taverna3
11 Division of Otorhinolaryngology, Department of Surgery and Translational Medicine, University of Florence, Florence, Italy.

Objectives::
Laryngeal squamous cell carcinoma (LSCC) can involve different anatomic subunits with peculiar surgical and prognostic implications. Despite conflicting outcomes for the same stage of disease, the current staging system considers different lesions in a single cluster. The aim of this study was to critically discuss clinical and pathologic staging of primary and recurrent advanced LSCC in order to define current staging pitfalls that impede a precise and tailored treatment strategy.
Methods::
Thirty patients who underwent total laryngectomy in the past 3 years for primary and recurrent advanced squamous cell LSCC were analyzed, comparing endoscopic, imaging, and pathologic findings. Involvement of the different laryngeal subunits, vocal-fold motility, and spreading pattern of the tumor were blindly analyzed. The diagnostic accuracy and differences between clinicoradiologic and pathologic findings were studied with standard statistical analysis.
Results::
Discordant staging was performed in 10% of patients, and thyroid and arytenoid cartilage were the major diagnostic pitfalls. Microscopic arytenoid involvement was significantly more present in case of vocal-fold fixation ( P = .028). Upstaging was influenced by paraglottic and pre-epiglottic space cancer involvement, posterior commissure, subglottic region, arytenoid cartilage, and penetration of thyroid cartilage; on the contrary, involvement of the inner cortex or extralaryngeal spread tended to be down-staged. Radiation-failed tumors less frequently involved the posterior third of the paraglottic space ( P = .022) and showed a significantly worse pattern of invasion ( P < .001).
Conclusions::
Even with the most recent technologies, 1 in 10 patients with advanced LSCC in this case series was differently staged on clinical examination, with cartilage involvement representing the main diagnostic pitfall.
More Related Videos
 06:36
Nerve Stimulator-guided Injection of Autologous Stem Cells Near the Equine Left Recurrent Laryngeal Nerve
Published on: September 26, 2018
 04:04
Endobronchial Ultrasound-guided Intratumoral Injection of Cisplatin for the Treatment of Isolated Mediastinal Recurrence of Lung Cancer
Published on: February 12, 2017
Related Concept Videos
 01:33
Cancer-Critical Genes I: Proto-oncogenes
When the function of certain critical genes, especially those involved in cell cycle regulation and cell growth signaling cascades, gets disrupted, it upsets the cell cycle progression. Such cells with unchecked cell cycles start proliferating uncontrollably and eventually develop into tumors.
Such genes that act...
 01:05
Cancer-Critical Genes II: Tumor Suppressor Genes
When the function of certain critical genes, especially those involved in cell cycle regulation and cell growth signaling cascades, gets disrupted, it upsets the cell cycle progression. Such cells with unchecked cell cycles start proliferating uncontrollably and eventually develop into tumors.
Such genes that act...
 01:16
Critical Region, Critical Values and Significance Level
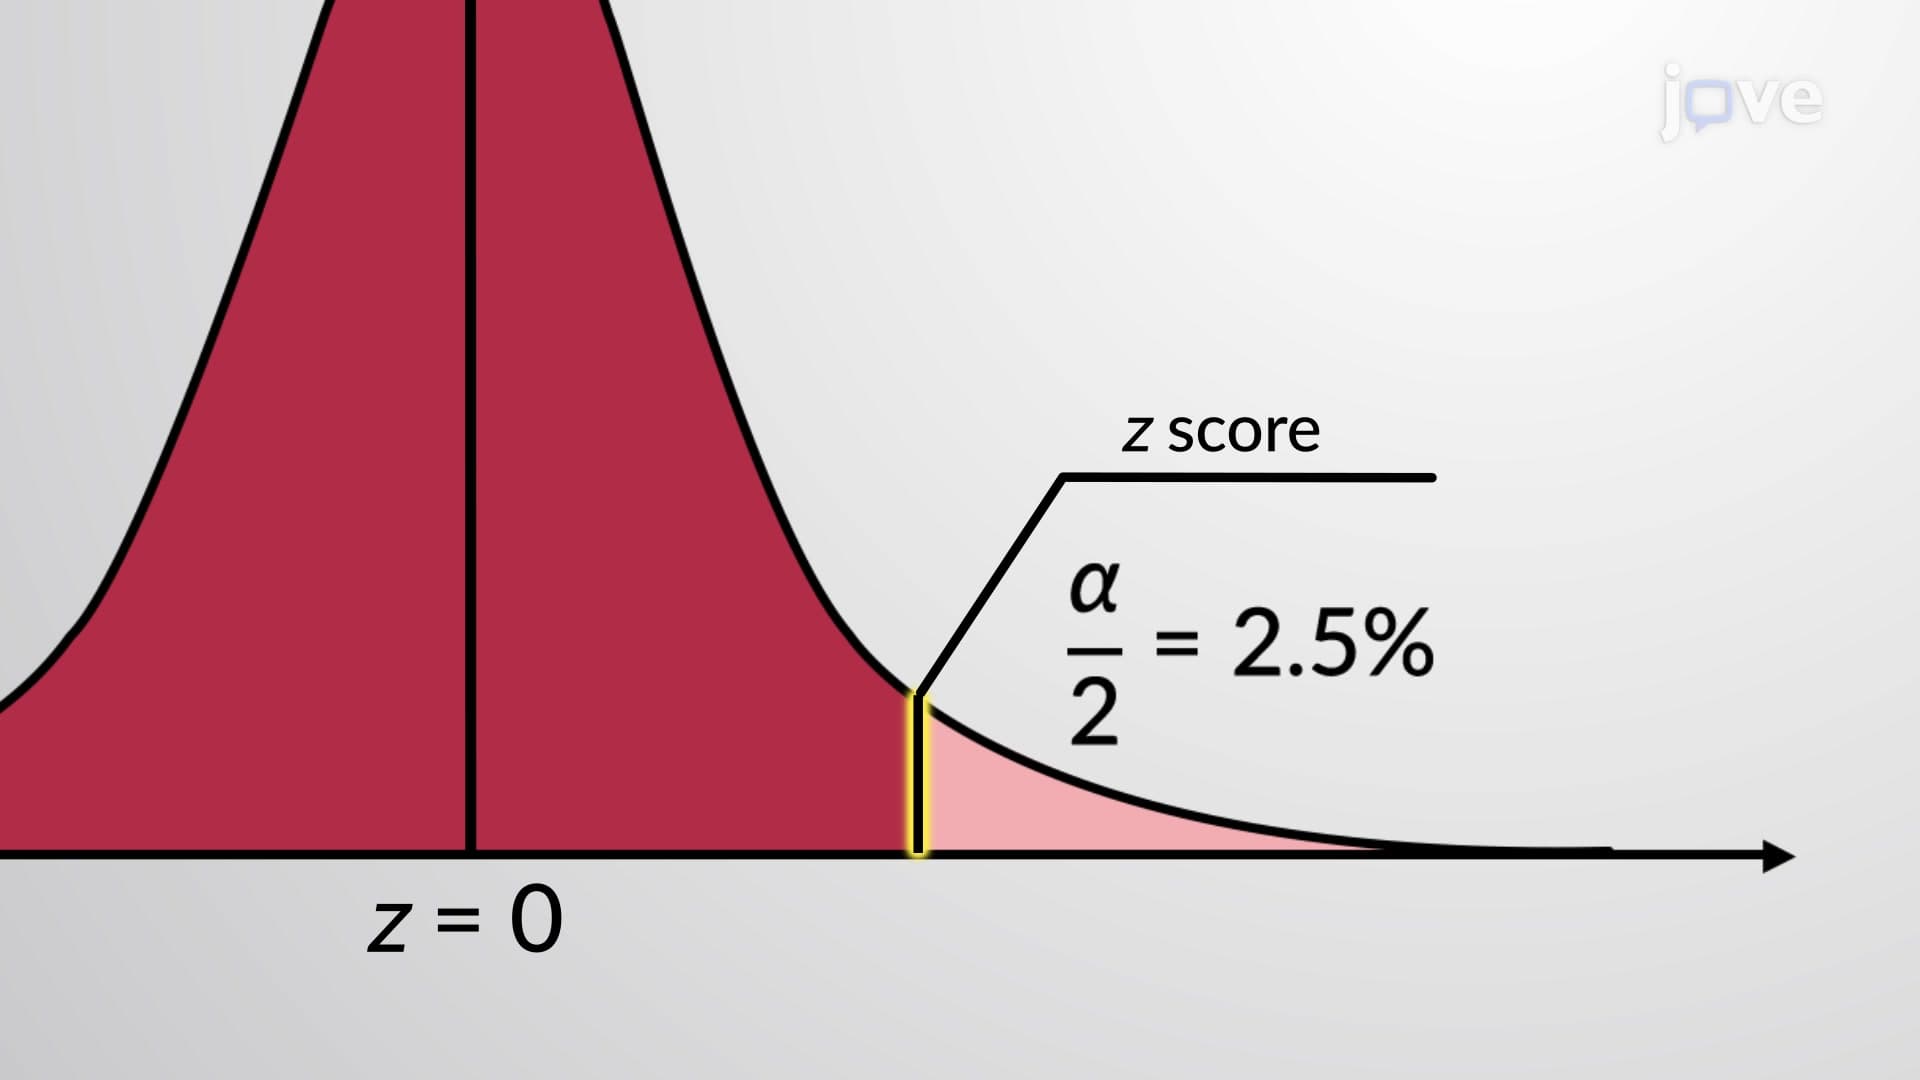
In hypothesis testing, a sample statistic is converted to a test statistic using z, t, or chi-square distribution. A critical region is an area under the curve in probability distributions demarcated by the critical value. When the test statistic falls in this region, it suggests that the null hypothesis must be rejected. As this region contains all those values of the...
 01:31
Critical Values
 01:24
Critical Thinking I
 01:25
Critical Thinking II